
Last updated: 13 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Urinary Tract Reconstruction in India is typically planned at $6,000–$16,000 per operation, with 5–12 nights as the stored hospital-stay guide. The range usually covers the named surgeon, anaesthesia, theatre time, standard consumables, quoted ward nights and routine pathology; imaging before arrival, upgraded devices, extra nights and treatment after departure are commonly separate. $25,000–$70,000 is the comparison reference.
A short lower-ureteric re-implant is a different operation from a long ileal ureter or bilateral repair. Robotic reconstruction is common in specialised centres and adds platform fees.
- India cost range
- $6,000–$16,000
- Typical starting point
- $6,000
- Typical hospital stay
- 5–12 nights
- Procedure time
- Commonly about 2–5 hours of theatre time depending on the segment and technique
- Recovery
- Incision discomfort and stent symptoms are expected for several weeks, and fistula repairs need a prolonged catheter.
Major cost factors: length and location of the defect, open, laparoscopic or robotic approach, prior radiation or multiple operations, preliminary drainage. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed operative scope; complications and re-intervention; premium devices and consumables; later treatment; travel and living.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
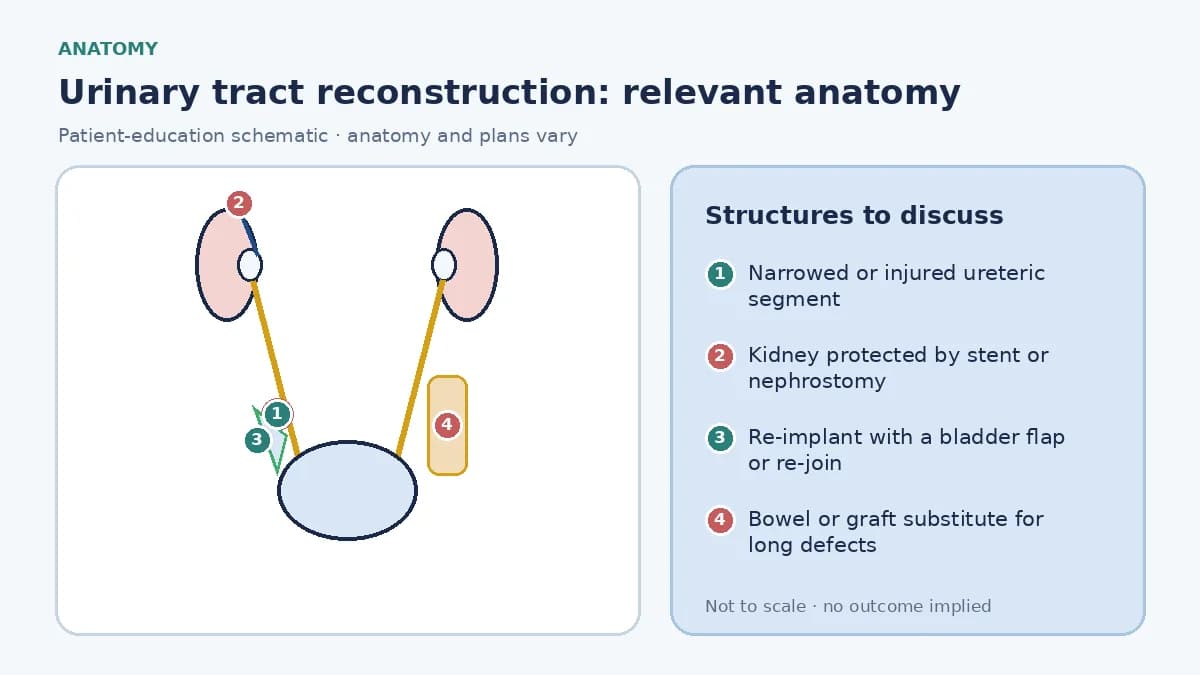
The ureters are thin tubes with a delicate blood supply, easily injured during pelvic or abdominal surgery, damaged by radiation, stones or instrumentation, or compressed by scar tissue. A narrowed or leaking ureter causes flank pain, infection, urine leakage and silent loss of kidney function. Reconstruction restores a wide, well-vascularised channel using the patient's own tissue.
This is not pyeloplasty, urethroplasty, bladder reconstruction or urinary diversion, which are separate slugs. The stored range is a single-operation band; a preliminary nephrostomy or stent placed elsewhere, staged procedures, stent removal after departure and treatment of recurrent narrowing are not presumed inside it.
This guide compares quotations; it cannot diagnose, choose an approach or decide timing. A urologist must connect symptoms, imaging and laboratory findings and explain individual uncertainty.
What Is Urinary Tract Reconstruction?
Urinary tract reconstruction covers open, laparoscopic or robotic operations that repair damaged or obstructed ureters and related structures — ureteric strictures, injuries after surgery or radiation, fistulas between the urinary tract and vagina or bowel, and retroperitoneal fibrosis — by re-joining, re-implanting, replacing or bypassing the affected segment so urine drains freely from kidney to bladder.
When Might Urinary Tract Reconstruction Be Considered?
Urinary tract reconstruction may be considered for ureteric strictures that fail or are unsuitable for stenting or balloon dilatation, ureteric injury recognised after pelvic surgery, vesicovaginal or ureterovaginal fistula, radiation-induced ureteric damage with preserved kidney function, and retroperitoneal fibrosis or ureteric obstruction after failed endoscopic treatment.
How the operation is performed, recovery and variations →
Urinary Tract Reconstruction cost in India
$6,000–$16,000 is the stored India planning range for urinary tract reconstruction, per operation, and $25,000–$70,000 the stored self-pay comparison. Neither is a guaranteed package; a changed approach, extra imaging, a longer stay or a second stage alters the final amount.
A usable estimate names the surgeon, campus, approach, ureteric or fistula reconstruction, stent and drain, anaesthesia, ward nights, pathology and follow-up, with professional, facility, device, imaging and pharmacy lines separated so two hospitals can be compared line by line.
Budget separately for flights, visa, insurance, transfers, companion, lodging, meals, extra nights and local follow-up unless expressly included.
Planning Range ≠ Final Hospital Quotation. Examination, current imaging, urine culture and anaesthesia review by a named reconstructive urologist come before candidacy, approach, risks and a final offer are meaningful.
Planning range or quotation?
The $6,000–$16,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Urinary Tract Reconstruction package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Named urology consultation
Consultation with the operating urologist, records review and examination when explicitly listed.
Usually included
Pre-anaesthetic assessment
Stated blood tests, ECG, urine culture and anaesthesia review; unlisted cardiac or pulmonary work-up is extra.
Usually included
Theatre and anaesthesia
Operating time, anaesthetist, standard consumables and recovery-room care within the written scope.
Usually included
Ward stay as quoted
Stated nights in the named room category, nursing, routine medicines and standard catheter or wound care.
Usually included
Routine imaging and pathology
Listed fluoroscopy, ultrasound or histopathology only; unlisted CT, PET or special stains are separate.
Usually included
Ureteric or fistula reconstruction, stent and drain
The stated re-implantation, ureteroureterostomy, substitution or fistula repair, the ureteric stent, catheter and drain when itemized.
May be charged separately
May be separate
Changed operative scope
Conversion to open surgery, a second stage or a different operation found after arrival.
May be separate
Complications and re-intervention
Unplanned ICU, transfusion, re-operation, prolonged drainage, readmission or extra imaging unless expressly covered.
May be separate
Premium devices and consumables
Upgraded stents, catheters, laser fibres, implants or single-use scopes beyond the written specification.
May be separate
Later treatment
Device removal after departure, adjuvant therapy, repeat procedures and long-term medicines unless itemized.
May be separate
Travel and living
Flights, visa, insurance, transfers, companion, lodging, meals, extra nights and care after returning home.
May be separate
Preliminary drainage, staged repairs and late imaging
A prior nephrostomy or stent, a second-stage procedure, stent removal after departure and follow-up nuclear scans are separate unless written.
Catalog inclusions listed for this pathway: urology consultation and records review; named surgeon on camera before travel; theatre, laser or transplant stay as quoted; stent, histology, graft or device follow-up as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Length and location of the defect
- A short lower-ureteric re-implant is a different operation from a long ileal ureter or bilateral repair.
- Open, laparoscopic or robotic approach
- Robotic reconstruction is common in specialised centres and adds platform fees.
- Prior radiation or multiple operations
- Irradiated, scarred tissue limits options, raises leak risk and can require bowel or graft substitution.
- Preliminary drainage
- A nephrostomy or stent to protect the kidney before definitive repair is a separate episode.
- Bowel use and ICU
- Ileal ureter or complex fistula repair adds bowel recovery time and sometimes ICU.
- Stents, catheter studies and imaging
- Stent removal, contrast studies and follow-up renal scans are often separate lines.
- Diagnostics before and after
- CT urography, MRI, cystoscopy, urodynamics or biopsy each add lines when not bundled.
- Anaesthesia and fitness
- Age, heart or lung disease, diabetes and anticoagulation change work-up, monitoring and ICU probability.
- Hospital category and room
- Campus tier, room class and city all shift nursing, facility and consumable pricing.
- Length of stay and recovery
- Extra nights for drainage, fever, bleeding or slow bladder recovery are billed daily unless capped.
Urinary Tract Reconstruction: approaches and where they differ
The approach is selected for the examined patient, not from a quality ladder. Each option carries its own consumables, theatre time, stay and follow-up, so a quotation must name it.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Ureteric re-implantation with psoas hitch or Boari flap | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | For lower-ureteric strictures or injuries: the bladder is mobilised or a flap created to reach healthy ureter. |
| Ureteroureterostomy | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | Excision of a short mid-ureteric segment and end-to-end repair over a stent. |
| Ileal ureter or buccal graft ureteroplasty | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | For long defects: a bowel segment replaces the ureter, or a cheek graft widens a long stricture, increasingly done robotically. |
| Fistula repair (vesicovaginal or ureterovaginal) | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | Transvaginal or abdominal closure with tissue interposition; timing after injury or radiation matters. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
Reconstructive urology: the subspecialty behind Urinary Tract Reconstruction
Reconstructive urology repairs strictures, fistulas, injuries and congenital or acquired defects of the urethra, ureter and bladder, often with grafts or bowel segments. Staging, tissue quality and previous operations determine the plan.
Timing: immediate drainage, delayed repair
When a ureteric injury or fistula is recognised, the first step is usually to protect the kidney with a stent or nephrostomy and let inflammation settle. Definitive repair is often planned weeks to months later, when tissue planes have recovered and imaging has defined the defect. Radiation-related damage may need an even longer interval.
International patients frequently arrive with a nephrostomy or stent already in place. Send those records and dates; the team plans the definitive reconstruction around the existing drainage and the kidney's measured function.
Vesicovaginal and ureterovaginal fistula
A fistula is an abnormal connection between the urinary tract and the vagina, most often after hysterectomy, obstructed labour or radiation, causing continuous urine leakage. Small early fistulas occasionally close with catheter drainage; most need surgery, either through the vagina or the abdomen, with healthy tissue placed between the closed layers.
Success depends on healthy tissue, tension-free closure and uninterrupted catheter drainage afterwards, typically two to three weeks, and a contrast study before the catheter is removed. Radiation fistulas are the most challenging and sometimes lead to diversion instead.
Risks and side effects of Urinary Tract Reconstruction
Risks include urine leak, bleeding, infection, injury to bowel or vessels, recurrent stricture, reflux into the kidney after re-implantation, bowel-related complications and metabolic changes when an ileal ureter is used, fistula recurrence, loss of kidney function if drainage fails, and the possibility that intra-operative findings require a different reconstruction than planned.
Ask before travel who pays for re-intervention, transfusion, ICU, prolonged drainage, readmission or a second stage.
Urinary Tract Reconstruction cost: India vs other medical tourism destinations
India and United States values use stored GAF planning ranges; the other countries require direct quotations. Compare the same diagnosis, approach, devices, anaesthesia, ward category, pathology and complication terms for urinary tract reconstruction; a lower headline with a different approach is not like-for-like.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $6,000–$16,000 | Baseline | GAF catalog planning range. The stored figure is a national planning range for the operation, hospital stay and standard consumables as written. It does not fix the approach, device, pathology scope or a final quotation. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Compare surgeon, endoscopic or robotic approach, laser or implant, stent and catheter management, pathology and complication terms rather than a headline package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. International coordination does not establish stone-free confirmation, catheter follow-up or continuity of oncology or transplant care after return. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Professional, theatre, device, imaging, pharmacy and follow-up charges are often billed separately and require written confirmation. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Request an estimate tied to the imaged anatomy, chosen approach, named device or laser and the expected number of admissions. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Private billing varies. Eligibility, professional billing, implant scope and postoperative urology follow-up require direct provider confirmation. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, quotation boundaries, urgent access and handover to a local urologist before travelling. |
| United States | $25,000–$70,000 | ≈4.3× India | Stored self-pay reference. Surgeon, anaesthesia, facility, device and pathology charges may be separate; $25,000–$70,000 is a comparison range, not a bundled quotation. |
International comparisons are indicative. Currency, changed findings, a different device or approach and length of stay can change the final amount.
Why do international patients consider India for urinary tract reconstruction?
Some patients consider India for urinary tract reconstruction because named urologists, endoscopic and laser platforms, robotic systems, transplant programmes and a national self-pay range are visible in one place. Price alone is not a clinical reason to travel, and listing does not establish acceptance.
Evaluate surgeon, licensure, campus, device traceability, ICU and dialysis backup where relevant, pathology quality, urgent access and home handover. No provider is ranked and no outcome is promised; unstable disease, insufficient records or suitable local care can make travel inappropriate.
Hospitals and urology centres for Urinary Tract Reconstruction in India
Cards follow exact live entity relationships for Urinary Tract Reconstruction. A general urology or accreditation label does not establish current acceptance, device stock or outcomes.
Indraprastha Apollo Hospital
 JCI Accredited
 NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
3 listed doctors for this pathway
Languages listed: English, Hindi
Apollo Hospital, Jubilee Hills, Hyderabad
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Telugu, Hindi
BLK-Max Super Speciality Hospital
- JCI Accredited
- NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi
Gleneagles HealthCity Chennai
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Tamil, Hindi
Max Super Speciality Hospital, Saket
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
2 listed doctors for this pathway
Languages listed: English, Hindi
Medanta - The Medicity
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
3 listed doctors for this pathway
Languages listed: English, Hindi
Yashoda Hospitals, Hi-Tech City
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Telugu, Hindi
Yashoda Hospitals, Secunderabad
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Telugu, Hindi
Urinary Tract Reconstruction hospitals in India · Talk to a treatment coordinator
Urinary Tract Reconstruction specialists in India
Profiles appear only when Urinary Tract Reconstruction is an exact current CMS procedure relationship. Verify subspecialty scope, availability and campus; placement is not a ranking or outcome claim.

Dr. Anant Kumar
Urology
40+ years Experience
Kidney Transplant Surgery (Living Donor,… · Living Donor Kidney Transplant · Deceased Donor Kidney Transplant
English, Hindi
Dr. Duraisamy S
Urology
38+ years Experience
Kidney Stone Surgery · Kidney Transplant Surgery · Living Donor Kidney Transplant
English, Tamil, Hindi
Dr. G. Madhusudhan Reddy
Urology
11+ years Experience
Kidney Transplant Surgery · Living Donor Kidney Transplant · Deceased Donor Kidney Transplant
English, Telugu, Hindi
Dr. Nirmit Agrawal
Urology
10+ years Experience
Kidney Stone Surgery · Percutaneous Nephrolithotomy · Ureteroscopy (URS)
English, Hindi, Marathi
Dr. Gagan Gautam
Urology
20+ years Experience
Radical Prostatectomy · Prostate Cancer Surgery · Kidney Cancer Surgery
English, Hindi
Dr. Muruganandham K
Urology
19+ years Experience
Kidney Transplant Surgery · Kidney Stone Surgery · Ureteroscopy (URS)
English, Tamil, Hindi
Dr. Gutta Srinivas
Urology
25+ years Experience
Kidney Transplant Surgery · ABO-Incompatible Kidney Transplant · Living Donor Kidney Transplant
English, Telugu, Hindi
Dr. Shafiq Ahmed
Urology
20+ years Experience
Kidney Transplant Surgery · Living Donor Kidney Transplant · Deceased Donor Kidney Transplant
English, Hindi
Urinary Tract Reconstruction doctors in India (19 listed) · Get a personalized cost estimate
Urinary Tract Reconstruction cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad use $6,000–$16,000 because no verified city tariff is stored. Their overlays add campus geography, transfers, lodging, climate and follow-up logistics without inventing local prices. Doctor and hospital cards resolve only from CMS entities carrying an exact current Urinary Tract Reconstruction relationship.
Swipe to compare Indian cities →
Delhi NCR
$6,000–$16,000
India planning band — not a city quote
Typical stay 5–12 nights
No verified Delhi NCR-only tariff for urinary tract reconstruction is stored. Use $6,000–$16,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
5 hospitals · 11 doctors
Mumbai
$6,000–$16,000
India planning band — not a city quote
Typical stay 5–12 nights
No verified Mumbai-only tariff for urinary tract reconstruction is stored. Use $6,000–$16,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 1 doctor
Bengaluru
$6,000–$16,000
India planning band — not a city quote
Typical stay 5–12 nights
No verified Bengaluru-only tariff for urinary tract reconstruction is stored. Use $6,000–$16,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Chennai
$6,000–$16,000
India planning band — not a city quote
Typical stay 5–12 nights
No verified Chennai-only tariff for urinary tract reconstruction is stored. Use $6,000–$16,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
2 hospitals · 2 doctors
Hyderabad
$6,000–$16,000
India planning band — not a city quote
Typical stay 5–12 nights
No verified Hyderabad-only tariff for urinary tract reconstruction is stored. Use $6,000–$16,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
5 hospitals · 5 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for urinary tract reconstruction
What should international patients budget beyond the urology procedure?
International planning starts with records and a named clinical question. A remote opinion is provisional until in-person examination, current imaging and anaesthesia review confirm the plan.
- Send records
- Provide ct or mr urogram and any retrograde or antegrade pyelogram showing the stricture, leak or fistula and kidney-function results.
- Remote triage
- A named reconstructive urologist reviews whether urinary tract reconstruction is a reasonable question.
- Treatment plan
- A written plan names approach, devices, stay and what could change it.
- Itemize quotation
- Surgeon, campus, anaesthesia, ward nights, pathology and exclusions.
- Plan travel
- Flexible flights, lodging near the campus and a companion.
- Arrive and examine
- Examination, urine culture, repeat imaging and anaesthesia review.
- Confirm consent
- Approach, risks, catheter or stent plan and possible changes.
- Complete procedure
- The consented urinary tract reconstruction with the stated monitoring.
- Early recovery
- Urine output, bleeding, pain, fever and drain or catheter function.
- Review results
- Imaging, pathology or function results and any second stage.
- Clear travel
- Written travel fitness, medicines and the removal plan for any device.
- Handover home
- Operative note, pathology and follow-up schedule for a local urologist.
- Treatment episode$6,000–$16,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay5–12 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for urinary tract reconstruction in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Define the problem
Symptoms, imaging and previous treatment.
Collect records
Imaging, laboratories and operative history.
Identify clinician
Named reconstructive urologist and campus.
Assess candidacy
Anatomy, function, infection and anaesthesia fitness.
Choose approach
Options for your findings, not a brochure default.
Compare quotes
Same approach, devices, nights and follow-up.
Plan travel
Flexible travel, lodging and a companion.
Confirm consent
Findings, risks and what could change.
Complete treatment
Procedure and monitored recovery.
Manage devices
Catheter, stent or drain instructions.
Attend review
Imaging, pathology or function checks.
Handover home
Operative record and follow-up schedule.
Documents to prepare
- CT or MR urogram and any retrograde or antegrade pyelogram showing the stricture, leak or fistula
- Nuclear renal scan with split kidney function
- Operative notes from the surgery or radiation that caused the injury
- Current nephrostomy or stent details and dates
- Recent kidney-function tests (creatinine, eGFR, electrolytes)
- Urine analysis and culture with antibiotic sensitivities
- Current medicines, allergies and anticoagulant or antiplatelet details
- Past operative reports, discharge summaries and anaesthesia records
Clinical detail
How the procedure is performed
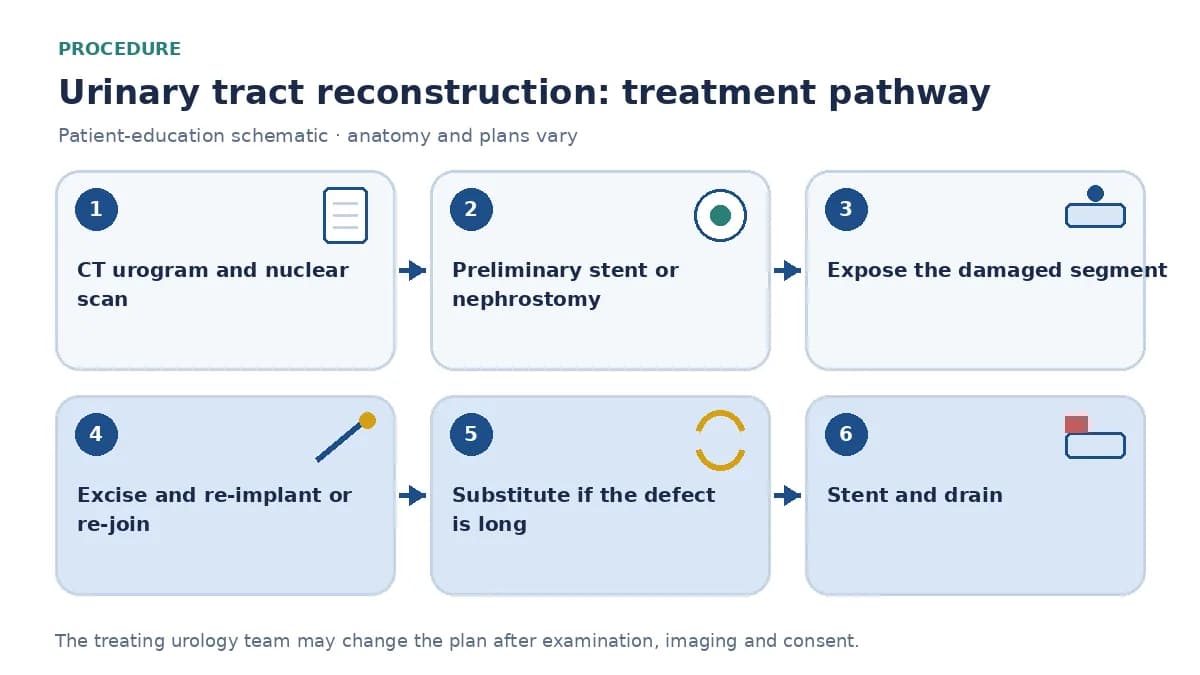
Under general anaesthesia, open, laparoscopic or robotic, the damaged segment is exposed and the approach depends on its location. Lower ureteric strictures are commonly re-implanted into the bladder, with a psoas hitch or Boari flap of bladder to bridge a gap. Mid-ureteric defects are excised and rejoined (ureteroureterostomy). Long defects may need a bowel segment (ileal ureter), a buccal graft onlay or, rarely, autotransplantation. Fistulas are separated, closed in layers and interposed with tissue. A stent and drain are left.
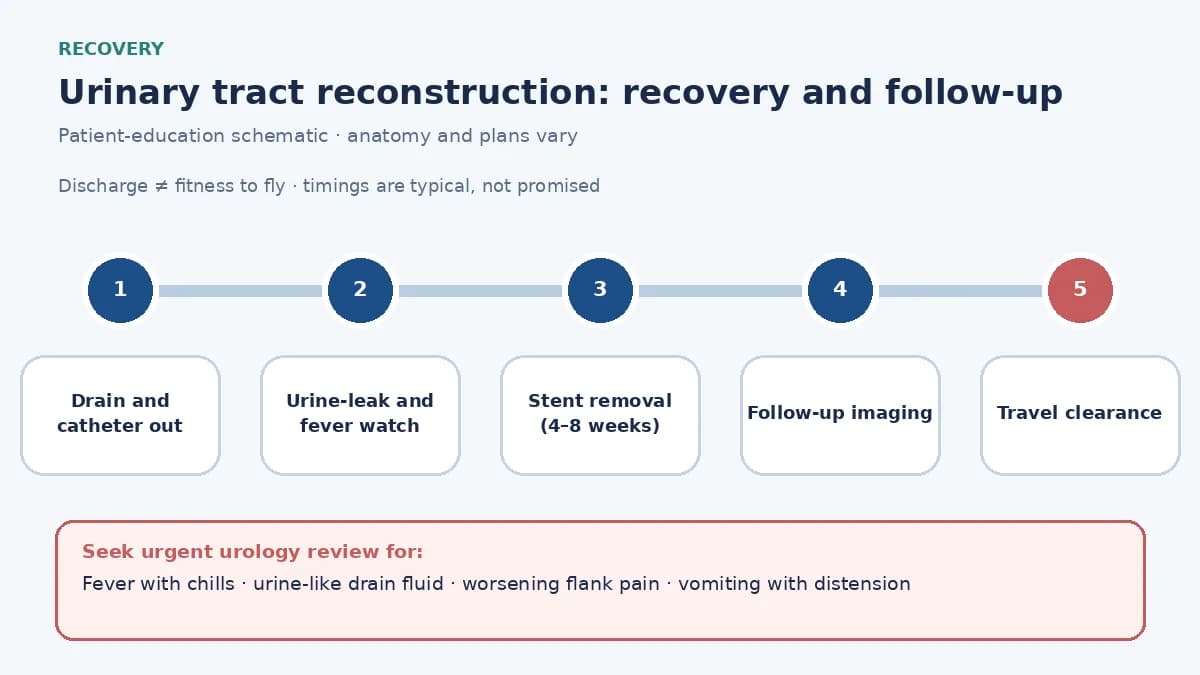
Monitoring covers drain output for urine leak, fever, bowel recovery when bowel is used, kidney function and stent position. The catheter and drain come out within days, the stent at four to eight weeks, and imaging months later confirms drainage without narrowing.
Main variations
- Ureteric re-implantation with psoas hitch or Boari flap
- For lower-ureteric strictures or injuries: the bladder is mobilised or a flap created to reach healthy ureter.
- Ureteroureterostomy
- Excision of a short mid-ureteric segment and end-to-end repair over a stent.
- Ileal ureter or buccal graft ureteroplasty
- For long defects: a bowel segment replaces the ureter, or a cheek graft widens a long stricture, increasingly done robotically.
- Fistula repair (vesicovaginal or ureterovaginal)
- Transvaginal or abdominal closure with tissue interposition; timing after injury or radiation matters.
Preparation
Assessment includes CT or MR urography and often a retrograde or antegrade pyelogram to define the length and site of the stricture or leak, a nuclear renal scan to confirm the kidney is worth saving, cystoscopy and vaginal examination for fistula, kidney-function tests, urine culture, and a review of previous operations and radiation, which determine which tissue is available for repair.
Clinicians direct anticoagulants, antiplatelets, diabetes medicines, fasting and hygiene. A positive urine culture is usually treated first and can postpone surgery.
Hospital stay and recovery
Most patients stay four to eight nights; the stored 5–12 nights reflects that. Bowel-based repairs and fistula surgery sit at the longer end. Incision discomfort and stent symptoms are expected for several weeks, and fistula repairs need a prolonged catheter. Flying is usually discussed after the drain is out with no leak, there is no fever and a stent-removal date or catheter study is fixed, often two to four weeks after surgery.
Keep catheter, stent or wound care clean. Seek urgent urology help for fever with chills, drain fluid that looks like urine, worsening flank or abdominal pain, vomiting with distension, or continued leakage from the vagina after fistula repair.
How to compare Urinary Tract Reconstruction quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Who is the operating reconstructive urologist, and at which exact campus?
- Why does urinary tract reconstruction fit my findings better than the alternatives?
- Which approach is planned, and what would make you change it on the day?
- Is the quotation for one operation, one stage or a complete pathway?
- What happens to the schedule if my urine culture is positive?
- Which devices, stents, catheters or implants are assumed, by name?
- How many ward nights are quoted, and in which room category?
- Is ICU or high-dependency care included if needed?
- When will any catheter, stent or drain be removed, and is that included?
- What is charged if the operation is converted or a second stage is needed?
- Which symptoms require urgent review, and where would that happen?
- When may I lift, exercise, resume sexual activity, work and fly?
- Who coordinates follow-up with my urologist after I return home?
- Which reconstruction is planned, and what would make you change it during surgery?
- Will bowel or a graft be needed, and how does that change the stay and follow-up?
- How long will the stent stay, and who removes it?
- For fistula repair, how long will the catheter stay, and when is the repair tested?
Frequently asked questions
How much does Urinary Tract Reconstruction cost in India?
Urinary Tract Reconstruction is typically planned at $6,000–$16,000 per operation. This stored national range is not a quotation; approach, devices, ward nights, pathology and written terms determine the final amount.
What is Urinary Tract Reconstruction?
Urinary tract reconstruction covers open, laparoscopic or robotic operations that repair damaged or obstructed ureters and related structures — ureteric strictures, injuries after surgery or radiation, fistulas between the urinary tract and vagina or bowel, and retroperitoneal fibrosis — by re-joining, re-implanting, replacing or bypassing the affected segment so urine drains freely from kidney to bladder.
When is urinary tract reconstruction considered?
Urinary tract reconstruction may be considered for ureteric strictures that fail or are unsuitable for stenting or balloon dilatation, ureteric injury recognised after pelvic surgery, vesicovaginal or ureterovaginal fistula, radiation-induced ureteric damage with preserved kidney function, and retroperitoneal fibrosis or ureteric obstruction after failed endoscopic treatment.
Is urinary tract reconstruction in India automatically cheaper than at home?
It may cost less than some self-pay markets, but quotations are not automatically comparable. Compare approach, surgeon, devices, ward category, pathology and complication terms; $25,000–$70,000 is the stored comparison reference.
What assessment is needed before urinary tract reconstruction?
Assessment includes CT or MR urography and often a retrograde or antegrade pyelogram to define the length and site of the stricture or leak, a nuclear renal scan to confirm the kidney is worth saving, cystoscopy and vaginal examination for fistula, kidney-function tests, urine culture, and a review of previous operations and radiation, which determine which tissue is available for repair.
How long is the hospital stay after urinary tract reconstruction?
Most patients stay four to eight nights; the stored 5–12 nights reflects that. Bowel-based repairs and fistula surgery sit at the longer end. Discharge is based on clinical criteria, not a package calendar.
What are the important risks of urinary tract reconstruction?
Risks include urine leak, bleeding, infection, injury to bowel or vessels, recurrent stricture, reflux into the kidney after re-implantation, bowel-related complications and metabolic changes when an ileal ureter is used, fistula recurrence, loss of kidney function if drainage fails, and the possibility that intra-operative findings require a different reconstruction than planned.
When can an international patient fly home after urinary tract reconstruction?
There is no fixed flight day. Flying is usually discussed after the drain is out with no leak, there is no fever and a stent-removal date or catheter study is fixed, often two to four weeks after surgery. The treating team must document travel fitness.
Can a ureteric stricture be treated without open surgery?
Short, recent strictures sometimes respond to balloon dilatation or endoscopic incision with a stent, and long-term stenting is an option for patients unfit for surgery. Durable relief for longer or recurrent strictures usually requires reconstruction.
Will my kidney recover after reconstruction?
Reconstruction aims to protect the function that remains and relieve obstruction. Function already lost may not return, which is why a nuclear scan is done first; a kidney with very poor function may be better removed than reconstructed.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Pyeloplasty cost in India
$4,500–$10,000 · stay 3–6 nights
Bladder Reconstruction cost in India
$10,000–$24,000 · stay 7–14 nights
Urinary Diversion cost in India
$9,000–$22,000 · stay 7–14 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 13 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Urinary Tract Reconstruction cost sheet · All treatment costs in India · Urology costs



