
Last updated: 13 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Bladder Reconstruction in India is typically planned at $10,000–$24,000 per operation, with 7–14 nights as the stored hospital-stay guide. The range usually covers the named surgeon, anaesthesia, theatre time, standard consumables, quoted ward nights and routine pathology; imaging before arrival, upgraded devices, extra nights and treatment after departure are commonly separate. $40,000–$90,000 is the comparison reference.
An augmentation patch, a neobladder and a continent pouch differ substantially in operative time, stents and stay. When the bladder is removed at the same sitting, the oncology operation is a separate scope on the shared sheet.
- India cost range
- $10,000–$24,000
- Typical starting point
- $10,000
- Typical hospital stay
- 7–14 nights
- Procedure time
- Commonly about 4–7 hours of theatre time depending on the type of reconstruction
- Recovery
- Fatigue, incision discomfort and mucus in the urine persist for weeks, and continence with a neobladder improves over months.
Major cost factors: type of reconstruction, combined cystectomy, open versus robotic approach, previous surgery, radiation or tuberculosis. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed operative scope; complications and re-intervention; premium devices and consumables; later treatment; travel and living.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
A healthy bladder stretches to store urine at low pressure and empties completely on command. Neurological disease, radiation, tuberculosis, interstitial cystitis or congenital defects can make it small, stiff and high-pressure, threatening the kidneys and causing incontinence; bladder cancer may require its removal altogether. Bowel tissue is compliant and can be detubularised and reshaped into a low-pressure reservoir.
This is not radical cystectomy itself, which follows the shared surgical-oncology sheet, and not incontinent urinary diversion (ileal conduit), which is a separate slug. The stored range is a single-operation band; staged procedures, later stone or stricture treatment and long-term self-catheterisation supplies are separate.
This guide compares quotations; it cannot diagnose, choose an approach or decide timing. A urologist must connect symptoms, imaging and laboratory findings and explain individual uncertainty.
What Is Bladder Reconstruction?
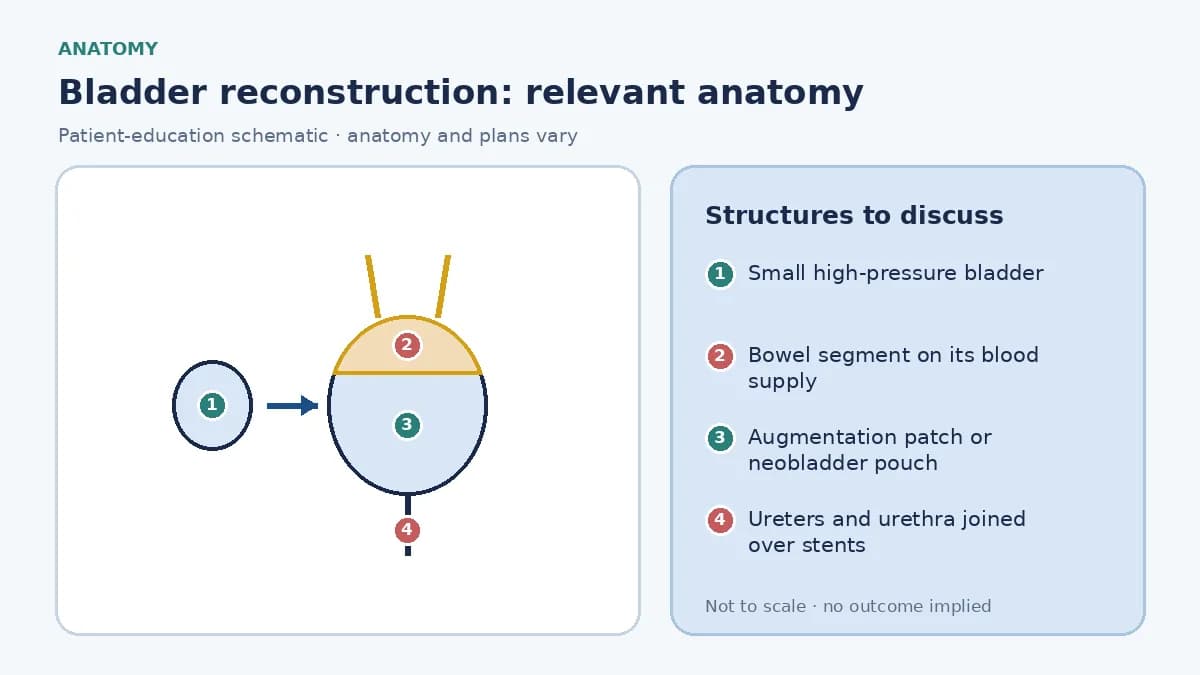
Bladder reconstruction is major surgery that rebuilds or enlarges the bladder — most often by augmenting it with a patch of bowel (augmentation cystoplasty) or by creating a new bladder from bowel after removal of the original (orthotopic neobladder) — so that urine can be stored at safe low pressure and passed through the urethra rather than into an external bag.
When Might Bladder Reconstruction Be Considered?
Bladder reconstruction may be considered for a small, high-pressure or non-compliant bladder that has failed medicines and botulinum toxin, for kidney-threatening pressures in neurogenic bladder, for contracted bladders after tuberculosis or radiation, and as an orthotopic neobladder after cystectomy when the urethra is cancer-free and the patient can self-catheterise if needed.
How the operation is performed, recovery and variations →
Bladder Reconstruction cost in India
$10,000–$24,000 is the stored India planning range for bladder reconstruction, per operation, and $40,000–$90,000 the stored self-pay comparison. Neither is a guaranteed package; a changed approach, extra imaging, a longer stay or a second stage alters the final amount.
A usable estimate names the surgeon, campus, approach, bowel segment reconstruction, stents and catheters, anaesthesia, ward nights, pathology and follow-up, with professional, facility, device, imaging and pharmacy lines separated so two hospitals can be compared line by line.
Budget separately for flights, visa, insurance, transfers, companion, lodging, meals, extra nights and local follow-up unless expressly included.
Planning Range ≠ Final Hospital Quotation. Examination, current imaging, urine culture and anaesthesia review by a named reconstructive urologist come before candidacy, approach, risks and a final offer are meaningful.
Planning range or quotation?
The $10,000–$24,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Bladder Reconstruction package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Named urology consultation
Consultation with the operating urologist, records review and examination when explicitly listed.
Usually included
Pre-anaesthetic assessment
Stated blood tests, ECG, urine culture and anaesthesia review; unlisted cardiac or pulmonary work-up is extra.
Usually included
Theatre and anaesthesia
Operating time, anaesthetist, standard consumables and recovery-room care within the written scope.
Usually included
Ward stay as quoted
Stated nights in the named room category, nursing, routine medicines and standard catheter or wound care.
Usually included
Routine imaging and pathology
Listed fluoroscopy, ultrasound or histopathology only; unlisted CT, PET or special stains are separate.
Usually included
Bowel segment reconstruction, stents and catheters
The stated augmentation, neobladder or pouch construction, ureteric stents, catheters, drain and the contrast study before catheter removal.
May be charged separately
May be separate
Changed operative scope
Conversion to open surgery, a second stage or a different operation found after arrival.
May be separate
Complications and re-intervention
Unplanned ICU, transfusion, re-operation, prolonged drainage, readmission or extra imaging unless expressly covered.
May be separate
Premium devices and consumables
Upgraded stents, catheters, laser fibres, implants or single-use scopes beyond the written specification.
May be separate
Later treatment
Device removal after departure, adjuvant therapy, repeat procedures and long-term medicines unless itemized.
May be separate
Travel and living
Flights, visa, insurance, transfers, companion, lodging, meals, extra nights and care after returning home.
May be separate
Cystectomy, staged procedures and long-term supplies
The cancer operation, later stone or stricture treatment, self-catheterisation supplies and vitamin supplementation are separate unless written.
Catalog inclusions listed for this pathway: urology consultation and records review; named surgeon on camera before travel; theatre, laser or transplant stay as quoted; stent, histology, graft or device follow-up as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Type of reconstruction
- An augmentation patch, a neobladder and a continent pouch differ substantially in operative time, stents and stay.
- Combined cystectomy
- When the bladder is removed at the same sitting, the oncology operation is a separate scope on the shared sheet.
- Open versus robotic approach
- Robotic intracorporeal reconstruction adds platform fees but may shorten recovery for some patients.
- Previous surgery, radiation or tuberculosis
- Scarred tissue and short ureters complicate dissection and anastomoses.
- ICU and bowel recovery
- Prolonged ileus, nutrition support or an ICU stay add daily charges.
- Catheters, stents and training
- Ureteric stents, suprapubic and urethral catheters and self-catheterisation teaching are itemized differently across centres.
- Diagnostics before and after
- CT urography, MRI, cystoscopy, urodynamics or biopsy each add lines when not bundled.
- Anaesthesia and fitness
- Age, heart or lung disease, diabetes and anticoagulation change work-up, monitoring and ICU probability.
- Hospital category and room
- Campus tier, room class and city all shift nursing, facility and consumable pricing.
- Length of stay and recovery
- Extra nights for drainage, fever, bleeding or slow bladder recovery are billed daily unless capped.
Bladder Reconstruction: approaches and where they differ
The approach is selected for the examined patient, not from a quality ladder. Each option carries its own consumables, theatre time, stay and follow-up, so a quotation must name it.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Augmentation cystoplasty (ileocystoplasty) | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | A patch of small bowel enlarges the existing bladder. Most patients self-catheterise afterwards. |
| Orthotopic neobladder (e.g. Studer, Hautmann) | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | A complete bowel reservoir joined to the urethra after cystectomy. Requires a cancer-free urethra and motivated patient. |
| Continent cutaneous pouch (e.g. Indiana pouch) | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | A bowel reservoir emptied by catheterising a small abdominal stoma when the urethra cannot be used. |
| Open versus robot-assisted reconstruction | Individual assessment determines suitability | No separate GAF sheetRelative complexity only | Robotic intracorporeal reconstruction is offered at some centres; platform charges are higher and operative time longer. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
Reconstructive urology: the subspecialty behind Bladder Reconstruction
Reconstructive urology repairs strictures, fistulas, injuries and congenital or acquired defects of the urethra, ureter and bladder, often with grafts or bowel segments. Staging, tissue quality and previous operations determine the plan.
Neobladder or ileal conduit: choosing after cystectomy
A neobladder restores voiding through the urethra without an external bag but requires a longer operation, a cancer-free urethra, regular timed voiding, acceptance of some night-time leakage and the ability to self-catheterise if emptying is incomplete. An ileal conduit is simpler and more predictable but means a permanent stoma and appliance.
Age, kidney function, bowel health, hand function, motivation and tumour location all influence the recommendation. Both are legitimate choices; the decision should be made with a stoma nurse and the surgeon before travel, because it changes the operation, the stay and the follow-up.
Living with a bowel-based bladder
Bowel tissue keeps producing mucus, so the reservoir must be flushed or emptied fully to avoid retention and stones, and fluids should be generous. Bowel also absorbs urinary salts, so periodic blood tests check for acidosis and, after years, vitamin B12 deficiency. Many patients with an augmented bladder empty by clean intermittent self-catheterisation several times a day.
Continence with a neobladder improves over the first year with timed voiding and pelvic-floor exercises; night-time leakage is common. Lifelong urology follow-up, including kidney imaging, is part of the commitment.
Risks and side effects of Bladder Reconstruction
Risks include bleeding, infection, bowel leak or obstruction, urine leak from the reconstruction, blood clots, metabolic acidosis and vitamin B12 deficiency from bowel absorption, mucus retention and stones in the reservoir, reservoir perforation, night-time incontinence or failure to empty requiring self-catheterisation, ureteric stricture and, over decades, a small risk of malignancy in the bowel segment.
Ask before travel who pays for re-intervention, transfusion, ICU, prolonged drainage, readmission or a second stage.
Bladder Reconstruction cost: India vs other medical tourism destinations
India and United States values use stored GAF planning ranges; the other countries require direct quotations. Compare the same diagnosis, approach, devices, anaesthesia, ward category, pathology and complication terms for bladder reconstruction; a lower headline with a different approach is not like-for-like.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $10,000–$24,000 | Baseline | GAF catalog planning range. The stored figure is a national planning range for the operation, hospital stay and standard consumables as written. It does not fix the approach, device, pathology scope or a final quotation. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Compare surgeon, endoscopic or robotic approach, laser or implant, stent and catheter management, pathology and complication terms rather than a headline package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. International coordination does not establish stone-free confirmation, catheter follow-up or continuity of oncology or transplant care after return. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Professional, theatre, device, imaging, pharmacy and follow-up charges are often billed separately and require written confirmation. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Request an estimate tied to the imaged anatomy, chosen approach, named device or laser and the expected number of admissions. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Private billing varies. Eligibility, professional billing, implant scope and postoperative urology follow-up require direct provider confirmation. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, quotation boundaries, urgent access and handover to a local urologist before travelling. |
| United States | $40,000–$90,000 | ≈3.8× India | Stored self-pay reference. Surgeon, anaesthesia, facility, device and pathology charges may be separate; $40,000–$90,000 is a comparison range, not a bundled quotation. |
International comparisons are indicative. Currency, changed findings, a different device or approach and length of stay can change the final amount.
Why do international patients consider India for bladder reconstruction?
Some patients consider India for bladder reconstruction because named urologists, endoscopic and laser platforms, robotic systems, transplant programmes and a national self-pay range are visible in one place. Price alone is not a clinical reason to travel, and listing does not establish acceptance.
Evaluate surgeon, licensure, campus, device traceability, ICU and dialysis backup where relevant, pathology quality, urgent access and home handover. No provider is ranked and no outcome is promised; unstable disease, insufficient records or suitable local care can make travel inappropriate.
Hospitals and urology centres for Bladder Reconstruction in India
Cards follow exact live entity relationships for Bladder Reconstruction. A general urology or accreditation label does not establish current acceptance, device stock or outcomes.
Campuses for this pathway are being confirmed. Ask the desk which houses currently quote it.
Bladder Reconstruction specialists in India
Profiles appear only when Bladder Reconstruction is an exact current CMS procedure relationship. Verify subspecialty scope, availability and campus; placement is not a ranking or outcome claim.
Named consultants for this pathway are being matched. Request a dossier and we will advise which campuses can quote it.
Bladder Reconstruction cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad use $10,000–$24,000 because no verified city tariff is stored. Their overlays add campus geography, transfers, lodging, climate and follow-up logistics without inventing local prices. Doctor and hospital cards resolve only from CMS entities carrying an exact current Bladder Reconstruction relationship.
Swipe to compare Indian cities →
Delhi NCR
$10,000–$24,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Delhi NCR-only tariff for bladder reconstruction is stored. Use $10,000–$24,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Mumbai
$10,000–$24,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Mumbai-only tariff for bladder reconstruction is stored. Use $10,000–$24,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Bengaluru
$10,000–$24,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Bengaluru-only tariff for bladder reconstruction is stored. Use $10,000–$24,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Chennai
$10,000–$24,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Chennai-only tariff for bladder reconstruction is stored. Use $10,000–$24,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Hyderabad
$10,000–$24,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Hyderabad-only tariff for bladder reconstruction is stored. Use $10,000–$24,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for bladder reconstruction
What should international patients budget beyond the urology procedure?
International planning starts with records and a named clinical question. A remote opinion is provisional until in-person examination, current imaging and anaesthesia review confirm the plan.
- Send records
- Provide video-urodynamic study with capacity, pressures and compliance and kidney-function results.
- Remote triage
- A named reconstructive urologist reviews whether bladder reconstruction is a reasonable question.
- Treatment plan
- A written plan names approach, devices, stay and what could change it.
- Itemize quotation
- Surgeon, campus, anaesthesia, ward nights, pathology and exclusions.
- Plan travel
- Flexible flights, lodging near the campus and a companion.
- Arrive and examine
- Examination, urine culture, repeat imaging and anaesthesia review.
- Confirm consent
- Approach, risks, catheter or stent plan and possible changes.
- Complete procedure
- The consented bladder reconstruction with the stated monitoring.
- Early recovery
- Urine output, bleeding, pain, fever and drain or catheter function.
- Review results
- Imaging, pathology or function results and any second stage.
- Clear travel
- Written travel fitness, medicines and the removal plan for any device.
- Handover home
- Operative note, pathology and follow-up schedule for a local urologist.
- Treatment episode$10,000–$24,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay7–14 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for bladder reconstruction in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Define the problem
Symptoms, imaging and previous treatment.
Collect records
Imaging, laboratories and operative history.
Identify clinician
Named reconstructive urologist and campus.
Assess candidacy
Anatomy, function, infection and anaesthesia fitness.
Choose approach
Options for your findings, not a brochure default.
Compare quotes
Same approach, devices, nights and follow-up.
Plan travel
Flexible travel, lodging and a companion.
Confirm consent
Findings, risks and what could change.
Complete treatment
Procedure and monitored recovery.
Manage devices
Catheter, stent or drain instructions.
Attend review
Imaging, pathology or function checks.
Handover home
Operative record and follow-up schedule.

Documents to prepare
- Video-urodynamic study with capacity, pressures and compliance
- Cystoscopy report and any bladder biopsy or cancer histopathology with urethral margin status
- Imaging of kidneys and ureters (ultrasound, CT or MR urogram)
- Neurological diagnosis, bowel history and previous pelvic surgery or radiation records
- Recent kidney-function tests (creatinine, eGFR, electrolytes)
- Urine analysis and culture with antibiotic sensitivities
- Current medicines, allergies and anticoagulant or antiplatelet details
- Past operative reports, discharge summaries and anaesthesia records
Clinical detail
How the procedure is performed
Under general anaesthesia through an open lower-abdominal incision or robotically, a segment of small bowel (or occasionally colon) is isolated on its blood supply and the bowel is rejoined. The segment is opened along its length and folded into a patch or a pouch. In augmentation the patch is sewn onto the opened bladder; in a neobladder the pouch is joined to the ureters and the urethra. Catheters and stents drain the reconstruction while it heals.
Monitoring covers bowel recovery, drain output, electrolytes and acid-base balance, urine leak, infection and mucus in the catheter, which needs regular flushing. The catheter typically stays two to three weeks and a contrast study confirms the pouch is watertight before it is removed and voiding or self-catheterisation training begins.

Main variations
- Augmentation cystoplasty (ileocystoplasty)
- A patch of small bowel enlarges the existing bladder.
- Orthotopic neobladder (e.g. Studer, Hautmann)
- A complete bowel reservoir joined to the urethra after cystectomy.
- Continent cutaneous pouch (e.g. Indiana pouch)
- A bowel reservoir emptied by catheterising a small abdominal stoma when the urethra cannot be used.
- Open versus robot-assisted reconstruction
- Robotic intracorporeal reconstruction is offered at some centres; platform charges are higher and operative time longer.
Preparation
Assessment includes video-urodynamics to measure bladder capacity, pressure and compliance, cystoscopy, imaging of the kidneys and ureters, kidney-function tests and electrolytes, an assessment of hand function and willingness to self-catheterise, bowel history, nutritional status and, in cancer cases, confirmation that the urethral margin is clear.
Clinicians direct anticoagulants, antiplatelets, diabetes medicines, fasting and hygiene. A positive urine culture is usually treated first and can postpone surgery.
Hospital stay and recovery
Most patients stay seven to fourteen nights; the stored 7–14 nights reflects that. An ICU or high-dependency night is common, and bowel recovery sets the pace of discharge. Fatigue, incision discomfort and mucus in the urine persist for weeks, and continence with a neobladder improves over months. Flying is usually discussed after the catheter has been removed following a watertight contrast study, electrolytes are stable and emptying or self-catheterisation is reliable, often three to five weeks after surgery.
Keep catheter, stent or wound care clean. Seek urgent urology help for fever with chills, severe abdominal pain or distension, vomiting, no urine or catheter output, or sudden heavy bleeding.
How to compare Bladder Reconstruction quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Who is the operating reconstructive urologist, and at which exact campus?
- Why does bladder reconstruction fit my findings better than the alternatives?
- Which approach is planned, and what would make you change it on the day?
- Is the quotation for one operation, one stage or a complete pathway?
- What happens to the schedule if my urine culture is positive?
- Which devices, stents, catheters or implants are assumed, by name?
- How many ward nights are quoted, and in which room category?
- Is ICU or high-dependency care included if needed?
- When will any catheter, stent or drain be removed, and is that included?
- What is charged if the operation is converted or a second stage is needed?
- Which symptoms require urgent review, and where would that happen?
- When may I lift, exercise, resume sexual activity, work and fly?
- Who coordinates follow-up with my urologist after I return home?
- Which type of reconstruction is planned, and why for my bladder and urethra?
- Will I need to self-catheterise, and is teaching included?
- How long will the catheter and stents stay, and is the contrast study included?
- How are electrolytes and vitamin B12 monitored after I return home?
Frequently asked questions
How much does Bladder Reconstruction cost in India?
Bladder Reconstruction is typically planned at $10,000–$24,000 per operation. This stored national range is not a quotation; approach, devices, ward nights, pathology and written terms determine the final amount.
What is Bladder Reconstruction?
Bladder reconstruction is major surgery that rebuilds or enlarges the bladder — most often by augmenting it with a patch of bowel (augmentation cystoplasty) or by creating a new bladder from bowel after removal of the original (orthotopic neobladder) — so that urine can be stored at safe low pressure and passed through the urethra rather than into an external bag.
When is bladder reconstruction considered?
Bladder reconstruction may be considered for a small, high-pressure or non-compliant bladder that has failed medicines and botulinum toxin, for kidney-threatening pressures in neurogenic bladder, for contracted bladders after tuberculosis or radiation, and as an orthotopic neobladder after cystectomy when the urethra is cancer-free and the patient can self-catheterise if needed.
Is bladder reconstruction in India automatically cheaper than at home?
It may cost less than some self-pay markets, but quotations are not automatically comparable. Compare approach, surgeon, devices, ward category, pathology and complication terms; $40,000–$90,000 is the stored comparison reference.
What assessment is needed before bladder reconstruction?
Assessment includes video-urodynamics to measure bladder capacity, pressure and compliance, cystoscopy, imaging of the kidneys and ureters, kidney-function tests and electrolytes, an assessment of hand function and willingness to self-catheterise, bowel history, nutritional status and, in cancer cases, confirmation that the urethral margin is clear.
How long is the hospital stay after bladder reconstruction?
Most patients stay seven to fourteen nights; the stored 7–14 nights reflects that. An ICU or high-dependency night is common, and bowel recovery sets the pace of discharge. Discharge is based on clinical criteria, not a package calendar.
What are the important risks of bladder reconstruction?
Risks include bleeding, infection, bowel leak or obstruction, urine leak from the reconstruction, blood clots, metabolic acidosis and vitamin B12 deficiency from bowel absorption, mucus retention and stones in the reservoir, reservoir perforation, night-time incontinence or failure to empty requiring self-catheterisation, ureteric stricture and, over decades, a small risk of malignancy in the bowel segment.
When can an international patient fly home after bladder reconstruction?
There is no fixed flight day. Flying is usually discussed after the catheter has been removed following a watertight contrast study, electrolytes are stable and emptying or self-catheterisation is reliable, often three to five weeks after surgery. The treating team must document travel fitness.
Will I be able to pass urine normally after a neobladder?
Most patients learn to void by relaxing the pelvic floor and gently straining at timed intervals. Daytime continence usually improves over months; night-time leakage is common, and some patients need intermittent self-catheterisation to empty fully.
Why is self-catheterisation part of the plan for augmentation cystoplasty?
The enlarged bladder often cannot contract strongly enough to empty on its own, especially in neurogenic bladder. Clean intermittent catheterisation several times a day empties it fully, protects the kidneys and reduces infection and stones. Willingness and hand function are checked before surgery.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Urinary Diversion cost in India
$9,000–$22,000 · stay 7–14 nights
Radical Cystectomy cost in India
$11,000–$26,000 · stay 7–14 nights
Urinary Tract Reconstruction cost in India
$6,000–$16,000 · stay 5–12 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 13 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Bladder Reconstruction cost sheet · All treatment costs in India · Urology costs



