
Last updated: 11 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
VSD Closure in India is typically planned at $4,500–$11,000. The stored international-family stay is 6–12 nights; parent stay expected, but urgency, preoperative stabilization, intensive care and discharge readiness can make an individual pathway shorter or longer.
Surgery generally uses cardiopulmonary bypass and a patch; selected anatomies may permit transcatheter device closure without sternotomy. Commonly discussed pathways include Surgical patch closure, Catheter device closure, Observation or staged management. A qualified pediatric congenital-heart team chooses among them; this page does not recommend an operation.
- India cost range
- $4,500–$11,000
- Typical starting point
- $4,500
- Typical hospital stay
- 6–12 nights; parent stay expected
- Procedure time
- often 3–5 hours for surgical closure; catheter pathways vary with anatomy
- Recovery
- Uncomplicated catheter recovery may be relatively short; sternotomy recovery usually requires several protected weeks, with feeding and weight gain followed closely.
Major cost factors: vsd type and relation to valves, shunt and pulmonary pressure, surgery versus device, associated repair. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: additional anatomy or physiology testing; associated or revised procedures; extended intensive care; later surveillance and medicines; travel and family living costs.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
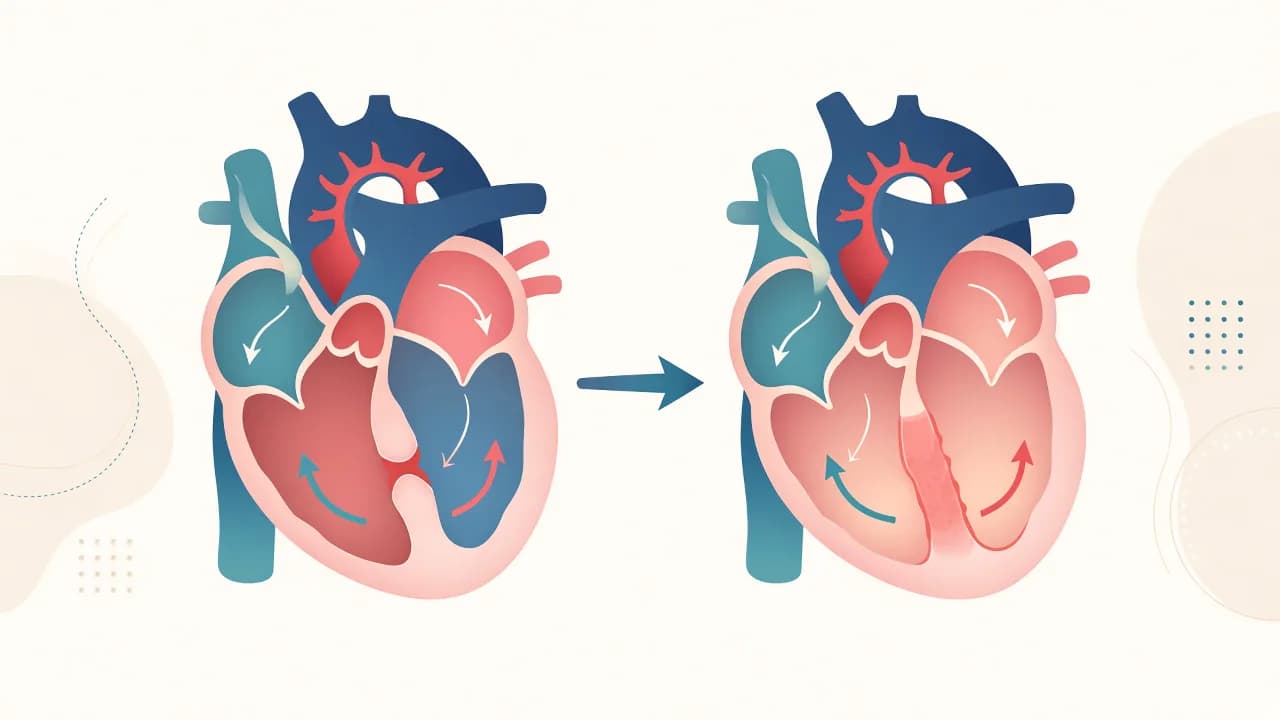
VSD closure seals an opening between the heart's pumping chambers to reduce an important left-to-right shunt or address another accepted indication. Closure may be considered for heart failure symptoms, poor growth, left-heart enlargement, significant shunting, aortic-valve involvement, prior endocarditis or associated lesions; small restrictive defects may only need surveillance.
Echocardiography should define muscular, perimembranous, inlet or outlet location, size, shunt effect, ventricular function, pulmonary pressure, aortic-valve relation and associated lesions; catheter pressure measurement is selective. The actual image files and physiological data matter more than a diagnosis written on a travel inquiry.
The catalog stores $4,500–$11,000 for India, $35,000–$90,000 for typical US self-pay and 6–12 nights; parent stay expected for planning. Those tokens keep the article synchronized with the cost registry. They are not quotations, outcome forecasts or evidence that a particular center can accept the case.
What Is VSD Closure?
VSD closure seals an opening between the heart's pumping chambers to reduce an important left-to-right shunt or address another accepted indication.
Surgery generally uses cardiopulmonary bypass and a patch; selected anatomies may permit transcatheter device closure without sternotomy.
When Is VSD Closure Recommended?
Closure may be considered for heart failure symptoms, poor growth, left-heart enlargement, significant shunting, aortic-valve involvement, prior endocarditis or associated lesions; small restrictive defects may only need surveillance.
Severe irreversible pulmonary vascular disease, a tiny clinically insignificant defect, active infection or anatomy requiring a broader repair may alter or preclude isolated closure.
How the operation is performed, recovery and variations →
VSD Closure (Ventricular Septal Defect) cost in India
The $4,500–$11,000 range is a national planning band for VSD closure as quoted. It may include the scheduled procedure, professional fees, operating room or catheter laboratory, anesthesia and a defined ICU and ward allowance. It does not establish what one hospital will charge.
Clinically important cost drivers include vsd type and relation to valves, shunt and pulmonary pressure, surgery versus device, associated repair, age, weight and nutrition. A change in physiology or planned work is not a cosmetic package upgrade; it may represent a materially different episode of care.
Do not infer separate Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad prices from the national range. Until a verified city figure exists, compare named teams and written inclusions while keeping family travel costs separate.
Surgical closure commonly requires pediatric cardiac ICU monitoring for rhythm, residual shunt, ventricular function, pulmonary pressure and bleeding. Uncomplicated catheter recovery may be relatively short; sternotomy recovery usually requires several protected weeks, with feeding and weight gain followed closely. Return flights and activity dates should remain flexible until the child is examined after treatment.
VSD Closure (Ventricular Septal Defect) cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a surgical estimate, not a dollar amount for each row.
- Congenital-heart review
- Pediatric cardiology and surgical review of imaging, physiology, previous procedures and the indication for VSD closure.
- Preoperative investigations
- The baseline work-up follows the case: Echocardiography should define muscular, perimembranous, inlet or outlet location, size, shunt effect, ventricular function, pulmonary pressure, aortic-valve relation and associated lesions; catheter pressure measurement is selective. Confirm which tests are included and which are conditional.
- Operating room, catheter laboratory and consumables
- The estimate should state the planned approach, bypass or catheter resources, implants or conduits where relevant, and what happens if the plan changes.
- Pediatric anesthesia and perfusion
- Ask whether anesthesia, invasive monitoring, cardiopulmonary bypass and perfusion are included where clinically applicable.
- Cardiac ICU and ward
- Surgical closure commonly requires pediatric cardiac ICU monitoring for rhythm, residual shunt, ventricular function, pulmonary pressure and bleeding. The quote should specify included ICU, ventilation and ward days rather than relying only on 6–12 nights; parent stay expected.
- Medicines, blood products and imaging
- Confirm routine versus high-cost medicines, blood components, laboratory monitoring, echocardiography and discharge prescriptions.
Planning range or quotation?
The $4,500–$11,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a VSD Closure package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Named specialist assessment
A consultation tied to the clinician expected to perform or lead the proposed intervention, where bundled.
Usually included
The written procedure and planned variations
The estimate should use the exact name VSD Closure (Ventricular Septal Defect) and identify associated work rather than say only “heart surgery.”
Usually included
Theater, anesthesia and perfusion
Professional and facility fees for the scheduled episode, with bypass and invasive monitoring stated where relevant.
Usually included
Quoted ICU and ward allowance
Room category and included ventilation, cardiac ICU and ward days; 6–12 nights; parent stay expected is a trip-planning token, not an inclusion promise.
Usually included
Routine inpatient monitoring
Laboratory tests, echocardiography, medicines, dressings and discharge documentation only to the extent written in the quote.
May be charged separately
May be separate
Additional anatomy or physiology testing
Repeat echo, CT, MRI, catheterization, genetic work-up or specialist consultations may be additional when indicated.
May be separate
Associated or revised procedures
Work beyond the documented operative plan, including an unplanned catheter or reoperation, is not automatically bundled.
May be separate
Extended intensive care
Extra ventilation, circulatory support, dialysis, infection care, blood products or additional ICU and ward days generally alter the bill.
May be separate
Later surveillance and medicines
Follow-up commonly assesses rhythm, residual flow, valve function, ventricular size, feeding and growth; device or surgical teams set the schedule. Confirm what occurs after the first postoperative visit and what can be transferred home.
May be separate
Travel and family living costs
Flights, visas, parent accommodation, meals, local transport and schedule changes are normally outside the hospital estimate.
Catalog inclusions listed for this pathway: paediatric cardiac surgery consultation and records review; named surgeon on camera before travel — parent present; theatre, anaesthesia, cardiopulmonary bypass and paediatric cardiac icu as quoted; device or prosthesis as indicated; discharge summary to your home paediatric cardiologist.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- VSD type and relation to valves
- Perimembranous, muscular, inlet and outlet defects require different access and protection of conduction tissue and valves.
- Shunt and pulmonary pressure
- Heart failure or elevated pulmonary vascular resistance can increase investigation and ICU needs.
- Surgery versus device
- Bypass and ICU use differ from catheter-lab, device and imaging resources.
- Associated repair
- Aortic valve, arch or additional septal work changes scope.
- Age, weight and nutrition
- Small size, respiratory illness and poor growth affect anesthesia and recovery.
Approaches related to VSD Closure
Surgery generally uses cardiopulmonary bypass and a patch; selected anatomies may permit transcatheter device closure without sternotomy. These are clinical pathways, not consumer upgrades.
The receiving team should explain why its proposed route fits the child's current anatomy and physiology, and what finding could change that route after arrival.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Surgical patch closure | Selected by anatomy, physiology and stage | No separate GAF sheetRelative complexity only | Common for significant perimembranous, inlet or outlet defects and when associated repair is needed. |
| Catheter device closure | Selected by anatomy, physiology and stage | No separate GAF sheetRelative complexity only | Considered for selected muscular or other suitable defects after careful assessment of valves and conduction tissue. |
| Observation or staged management | Selected by anatomy, physiology and stage | No separate GAF sheetRelative complexity only | Small defects may be watched; very small infants with complex physiology may need individualized timing or palliation. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
VSD Closure (Ventricular Septal Defect) cost: India vs other medical tourism destinations
India and United States values come from the stored GAF registry. Other rows are explicitly modelled from relative private-care levels and are not official tariffs or evidence of availability.
International comparisons are easily distorted when operative scope, stage, implants, ICU assumptions and follow-up differ. Obtain like-for-like written estimates after record review.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $4,500–$11,000 | Baseline | GAF catalog planning range. The stored India range is a comparison band; a named congenital-heart team must review the child's records before issuing a case-specific quotation. |
| Turkey | $8,500–$14,000Indicative planning estimate* | ≈1.4× India | Private international-care market. Confirm the exact pediatric program, procedure, ICU assumptions and whether implants or staged care are included. |
| Thailand | $10,000–$17,000Indicative planning estimate* | ≈1.8× India | Private international hospitals. International coordination may be available, but congenital anatomy and pediatric intensive-care support require written confirmation. |
| United Arab Emirates | $17,000–$28,000Indicative planning estimate* | ≈2.9× India | Regional premium private care. Travel may be shorter for Gulf families; specialist, facility and ICU charges may remain separate. |
| Singapore | $21,500–$37,000Indicative planning estimate* | ≈3.8× India | High-cost specialist private care. Ask for an international self-pay estimate tied to the exact congenital diagnosis rather than a general cardiac package. |
| Germany | $19,500–$35,000Indicative planning estimate* | ≈3.5× India | European congenital-heart care. International access, professional billing and post-discharge arrangements vary by center and should be established before travel. |
| United Kingdom | $17,000–$31,000Indicative planning estimate* | ≈3.1× India | Private self-pay for many visitors. Overseas families should verify eligibility, the treating unit and whether investigations and follow-up are separately charged. |
| United States | $35,000–$90,000 | ≈8.1× India | Stored self-pay reference. Facility, surgeon, anesthesia, imaging, ICU and follow-up may be billed by different entities; $35,000–$90,000 is a comparison range, not one bundled quote. |
*Figures other than India and the United States are modelled planning estimates scaled from the India catalog band, not hospital quotations. All figures are planning information. Currency, anatomy, urgency, clinical course, hospital terms and length of stay can change the final amount; no row predicts outcomes.
Why do international patients consider India for VSD closure?
Some international families evaluate India for access to a named pediatric congenital-heart team and a self-pay planning band below typical United States figures. Cost alone is not a reason to move a child.
The key questions are clinical acceptance, appropriate pediatric anesthesia and intensive care, the proposed team's relevance to the anatomy, and continuity after return. These require direct written confirmation.
No hospital or clinician is described as best. An unstable newborn or child may be unsafe to fly, and established funded care near home may be more appropriate.
Hospitals for VSD closure in India
Hospital cards should follow live entity relationships, not names embedded in editorial copy. Accreditation or a general cardiac label does not prove current pediatric congenital capability, ICU availability, case acceptance or outcomes.
Indraprastha Apollo Hospital
 JCI Accredited
 NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
3 listed doctors for this pathway
Languages listed: English, Hindi
Apollo Hospital, Jubilee Hills, Hyderabad
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Telugu, Hindi
Apollo Hospitals, Navi Mumbai
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi, Marathi
Artemis Hospital
- JCI Accredited
- NABH Accredited
- DHADHA
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi
Fortis Memorial Research Institute
- JCI Accredited
- NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi
Max Super Speciality Hospital, Saket
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
2 listed doctors for this pathway
Languages listed: English, Hindi
Medanta - The Medicity
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
2 listed doctors for this pathway
Languages listed: English, Hindi
MGM Healthcare, Chennai
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
3 listed doctors for this pathway
Languages listed: English, Tamil, Hindi
VSD Closure hospitals in India · Talk to a treatment coordinator
Doctors to consider for VSD closure in India
Profiles should be pulled dynamically only when VSD Closure (Ventricular Septal Defect) appears in the clinician's current procedure relationships. Verify role, case relevance, availability and campus. Placement is not a ranking, and this article adds no experience or outcome claim.

Dr. Ashutosh Marwah
Pediatric Cardiac Surgery
28+ years Experience
ASD Device Closure · VSD Device Closure · PDA Device Closure
English, Hindi
Dr. Anil Kumar D
Pediatric Cardiac Surgery
42+ years Experience
Arterial Switch Operation · ASD Device Closure · ASD Surgical Closure
English, Telugu, Hindi
Dr. Bhushan Chavan
Pediatric Cardiac Surgery
18+ years Experience
Congenital Heart Disease (CHD) Treatment… · Pediatric Echocardiography · ASD Device Closure
English, Hindi, Marathi
Dr. R K R Noveen Davidson
Pediatric Cardiac Surgery
21+ years Experience
Congenital Heart Disease (CHD) Treatment… · TOF Repair Surgery · Arterial Switch Operation
English, Tamil, Hindi
Dr. Krishna Subramony Iyer
Pediatric Cardiac Surgery
42+ years Experience
Pediatric Open Heart Surgery · Neonatal Cardiac Surgery · Congenital Heart Disease Management
English, Hindi
Dr. Gouthami V
Pediatric Cardiac Surgery
22+ years Experience
Pediatric Echocardiography · Congenital Heart Disease (CHD) Treatment… · Balloon Pulmonary Valvotomy
English, Telugu, Hindi
Dr. Rajesh Kumar R
Pediatric Cardiac Surgery
16+ years Experience
Congenital Heart Disease (CHD) Treatment… · ASD Surgical Closure · VSD Surgical Closure
English, Tamil, Hindi
Dr. Kulbhushan Singh Dagar
Pediatric Cardiac Surgery
33+ years Experience
ASD Closure (Atrial Septal Defect) · VSD Closure (Ventricular Septal Defect) · TOF Repair (Tetralogy of Fallot)
English, Hindi
VSD Closure doctors in India (25 listed) · Get a personalized cost estimate
VSD Closure cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad retain $4,500–$11,000 until verified city-level data is stored. Their overlays focus on genuinely different airport, geography and family-stay logistics.
Clinician and hospital cards must resolve dynamically from current data. This module names no provider, makes no capability assumption and offers no ranking.
Swipe to compare Indian cities →
Delhi NCR
$4,500–$11,000
India planning band — not a city quote
Typical stay 6–12 nights; parent stay expected
No verified Delhi NCR-only tariff is stored. Use $4,500–$11,000 as the national planning band until a named hospital supplies an itemized case estimate.
8 hospitals · 17 doctors
Mumbai
$4,500–$11,000
India planning band — not a city quote
Typical stay 6–12 nights; parent stay expected
No verified Mumbai-only tariff is stored. Use $4,500–$11,000 as the national planning band until a named hospital supplies an itemized case estimate.
1 hospital · 1 doctor
Bengaluru
$4,500–$11,000
India planning band — not a city quote
Typical stay 6–12 nights; parent stay expected
No verified Bengaluru-only tariff is stored. Use $4,500–$11,000 as the national planning band until a named hospital supplies an itemized case estimate.
0 hospitals · consultant match on request
Chennai
$4,500–$11,000
India planning band — not a city quote
Typical stay 6–12 nights; parent stay expected
No verified Chennai-only tariff is stored. Use $4,500–$11,000 as the national planning band until a named hospital supplies an itemized case estimate.
1 hospital · 3 doctors
Hyderabad
$4,500–$11,000
India planning band — not a city quote
Typical stay 6–12 nights; parent stay expected
No verified Hyderabad-only tariff is stored. Use $4,500–$11,000 as the national planning band until a named hospital supplies an itemized case estimate.
3 hospitals · 4 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for VSD closure
What should international patients budget beyond the surgery?
A complete VSD closure budget includes much more than the $4,500–$11,000 hospital planning band. Add remote review, tests not bundled, parent travel, lodging, local transport, medicines and contingency for extra nights.
Travel should follow a written clinical acceptance and itemized estimate. A visa letter or directory card is not medical clearance.
- Records and stability review
- Share imaging, current observations, symptoms, growth or feeding, medicines, prior procedures and the referring clinician's question.
- Multidisciplinary planning
- Pediatric cardiology, congenital surgery, anesthesia and intensive-care teams clarify indication, timing, approach and whether commercial travel is appropriate.
- Itemized estimate and logistics
- Match the exact procedure to included tests, implants, bypass, ICU and ward days, exclusions, escalation rates and parent accommodation.
- Arrival and reassessment
- Allow time for examination, repeat imaging, blood tests and anesthesia review; consent should include alternatives and child-specific uncertainty.
- Procedure and monitored recovery
- Surgery generally uses cardiopulmonary bypass and a patch; selected anatomies may permit transcatheter device closure without sternotomy. Surgical closure commonly requires pediatric cardiac ICU monitoring for rhythm, residual shunt, ventricular function, pulmonary pressure and bleeding.
- Discharge, nearby review and handover
- Uncomplicated catheter recovery may be relatively short; sternotomy recovery usually requires several protected weeks, with feeding and weight gain followed closely. Travel only after review and carry the operative note, imaging, medicine plan and follow-up schedule.
- Treatment episode$4,500–$11,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay6–12 nights; parent stay expected typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for VSD closure in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Send complete records
Provide actual imaging, reports, current clinical observations, medicines and all prior catheter or operative notes.
Confirm clinical acceptance
A named congenital-heart team reviews diagnosis, urgency, stage, travel safety and the likely intervention.
Hold a remote family discussion
Ask why treatment is indicated now, what alternatives exist, what remains uncertain and who will lead care.
Compare itemized quotations
Use the same operative scope and ICU assumptions; do not compare a partial estimate with a comprehensive episode.
Plan flexible travel
Obtain required documents, refundable flights and lodging near the exact campus, with contingency for a longer stay.
Repeat assessment after arrival
The child is examined and undergoes indicated imaging, laboratory and anesthesia review before final consent.
Treatment and pediatric cardiac ICU
Care follows the agreed approach, with escalation according to the child's condition rather than package limits.
Step down and prepare discharge
Parents learn medicine, feeding, wound, activity and warning-sign instructions and receive written records.
Complete local review
Remain nearby until the team reviews recovery and explicitly discusses fitness for travel.
Continue care at home
Transfer records to the child's local clinician. Follow-up commonly assesses rhythm, residual flow, valve function, ventricular size, feeding and growth; device or surgical teams set the schedule.

Documents to prepare
- Serial echocardiograms showing chamber size and pulmonary-pressure estimates
- Most recent echocardiogram report and complete image loops or DICOM files
- ECG and any rhythm-monitor, catheterization, CT or MRI records
- Current medication list, allergies, vaccination history and recent laboratory results
- Growth, feeding, oxygen-saturation and symptom history
- All prior cardiac operative notes, discharge summaries and implant details
- Passport and guardian documentation required for travel and consent
Clinical detail
How the operation is performed
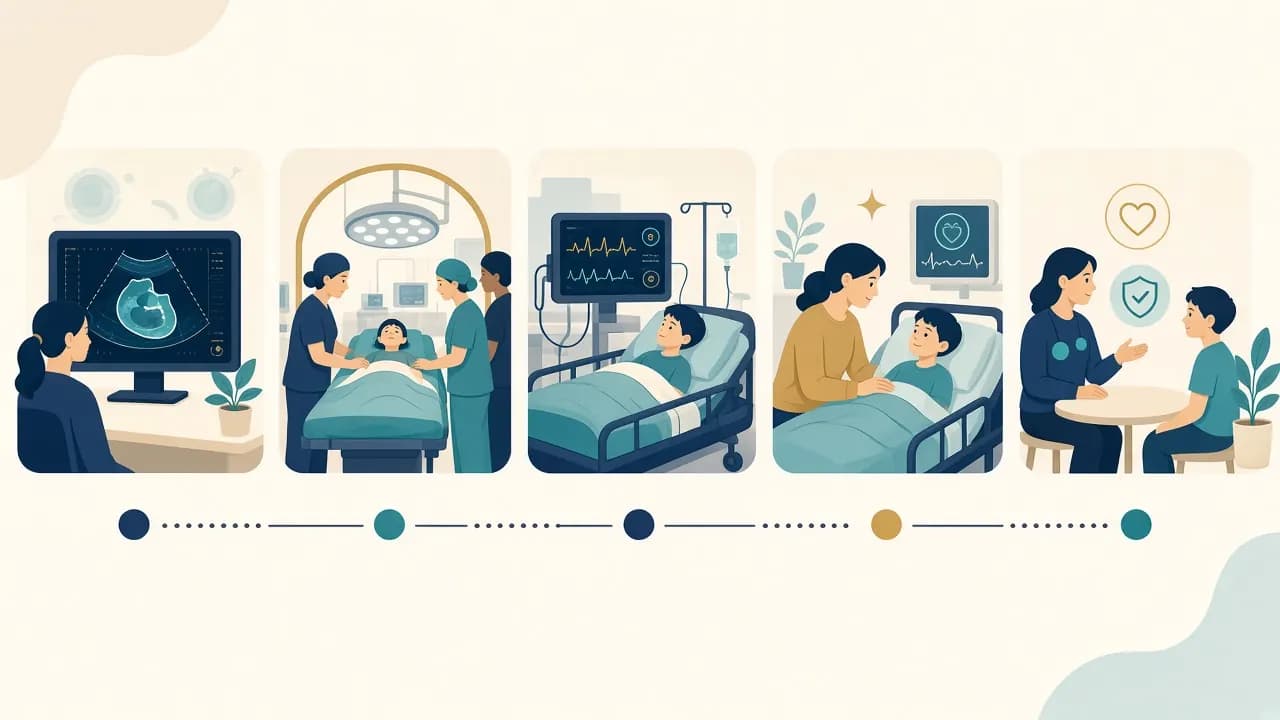
Surgery generally uses cardiopulmonary bypass and a patch; selected anatomies may permit transcatheter device closure without sternotomy.
The listed procedural forms are Surgical patch closure, Catheter device closure, Observation or staged management. The sequence, incision, bypass strategy, implants and associated repairs depend on the child's anatomy.
Surgical closure commonly requires pediatric cardiac ICU monitoring for rhythm, residual shunt, ventricular function, pulmonary pressure and bleeding. Monitoring commonly includes circulation, oxygenation, rhythm, urine output, bleeding, neurological status, feeding and imaging as relevant.
Main variations
- Surgical patch closure
- Common for significant perimembranous, inlet or outlet defects and when associated repair is needed.
- Catheter device closure
- Considered for selected muscular or other suitable defects after careful assessment of valves and conduction tissue.
- Observation or staged management
- Small defects may be watched; very small infants with complex physiology may need individualized timing or palliation.
Preparation
Echocardiography should define muscular, perimembranous, inlet or outlet location, size, shunt effect, ventricular function, pulmonary pressure, aortic-valve relation and associated lesions; catheter pressure measurement is selective. Send complete records rather than screenshots or a one-line report.
The receiving team sets fasting and medication instructions. Report fever, respiratory symptoms, infection, feeding deterioration or a change in oxygen saturation promptly; these may alter timing.
Hospital stay and recovery
Surgical closure commonly requires pediatric cardiac ICU monitoring for rhythm, residual shunt, ventricular function, pulmonary pressure and bleeding. Uncomplicated catheter recovery may be relatively short; sternotomy recovery usually requires several protected weeks, with feeding and weight gain followed closely.
The catalog's 6–12 nights; parent stay expected is for broad planning, not a discharge promise. Drainage, oxygen need, feeding, wound healing, rhythm and repeat imaging can affect the actual stay.
Discussion should include residual shunt, conduction block or pacemaker need, valve injury, pulmonary hypertensive events, ventricular dysfunction, bleeding and infection without assigning generic probabilities.
Follow-up commonly assesses rhythm, residual flow, valve function, ventricular size, feeding and growth; device or surgical teams set the schedule. Families need a written handover, emergency contacts and a local pediatric cardiology plan.
Seek urgent clinical help for breathing difficulty, blue or unusually pale color, fainting, persistent fever, wound concerns, poor feeding, marked lethargy, reduced urine, new swelling or any warning sign specified at discharge.
How to compare VSD Closure quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is VSD closure recommended now, and what alternatives were considered?
- Which anatomy, physiology or previous-stage finding drives the plan?
- Who will perform the procedure, and at which exact campus?
- Does the quotation use the exact treatment name and list associated work?
- Which investigations must be repeated after arrival, and are they included?
- Are pediatric anesthesia, perfusion and blood products included where relevant?
- How many ventilation, cardiac ICU and ward days are included?
- Which implants, patches, conduits, devices or special medicines are assumed?
- What finding could change the approach or require an additional procedure?
- How are extra ICU days, reintervention, infection care or other complications billed?
- What room category is quoted, and can a parent remain nearby?
- Which discharge imaging, medicines and first follow-up are included?
- What warning signs and local emergency plan should the family use?
- When will the team assess fitness to fly, and what follow-up is needed at home?
- If device closure is proposed, which device and imaging assumptions are included?
- How will conduction and aortic-valve function be monitored?
Frequently asked questions
How much does VSD closure cost in India?
VSD Closure is typically planned at $4,500–$11,000. This stored range is not a quote; anatomy, urgency, operative scope, ICU support and hospital terms determine the final amount.
What is VSD closure?
VSD closure seals an opening between the heart's pumping chambers to reduce an important left-to-right shunt or address another accepted indication.
When is VSD closure considered?
Closure may be considered for heart failure symptoms, poor growth, left-heart enlargement, significant shunting, aortic-valve involvement, prior endocarditis or associated lesions; small restrictive defects may only need surveillance.
Does every child with this diagnosis need the same procedure?
Severe irreversible pulmonary vascular disease, a tiny clinically insignificant defect, active infection or anatomy requiring a broader repair may alter or preclude isolated closure. Timing and approach require individualized congenital-heart review.
What tests are needed before treatment?
Echocardiography should define muscular, perimembranous, inlet or outlet location, size, shunt effect, ventricular function, pulmonary pressure, aortic-valve relation and associated lesions; catheter pressure measurement is selective.
What approaches may be discussed?
Surgery generally uses cardiopulmonary bypass and a patch; selected anatomies may permit transcatheter device closure without sternotomy. Relevant forms include Surgical patch closure, Catheter device closure, Observation or staged management; they are selected clinically, not by package price.
How long does VSD closure take?
often 3–5 hours for surgical closure; catheter pathways vary with anatomy This is an orientation only; associated work and the child's condition can extend the episode.
Will the child need pediatric cardiac intensive care?
Surgical closure commonly requires pediatric cardiac ICU monitoring for rhythm, residual shunt, ventricular function, pulmonary pressure and bleeding.
How long is recovery?
Uncomplicated catheter recovery may be relatively short; sternotomy recovery usually requires several protected weeks, with feeding and weight gain followed closely. The stored stay is 6–12 nights; parent stay expected, but discharge and travel dates remain individualized.
What can make the quotation change?
Important drivers include vsd type and relation to valves, shunt and pulmonary pressure, surgery versus device, associated repair, age, weight and nutrition. Ask for each change in writing.
Are complications and extra ICU days included?
Only if the itemized estimate says so. Ask how ventilation, circulatory support, blood products, infection care, reintervention and days beyond the allowance are billed.
How should an international family choose a team?
Verify the proposed clinician's role, relevance to the child's anatomy and stage, exact campus, pediatric ICU and anesthesia support, communication and handover plan. Directory placement is not a ranking.
Can the child fly soon after treatment?
There is no universal safe date. The treating team must assess circulation, oxygenation, feeding, wounds, rhythm and imaging before clearing travel.
What follow-up is required?
Follow-up commonly assesses rhythm, residual flow, valve function, ventricular size, feeding and growth; device or surgical teams set the schedule.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
ASD Closure (Atrial Septal Defect) cost in India
$4,000–$9,500 · stay 5–10 nights; parent stay expected
PDA Closure (Patent Ductus Arteriosus) cost in India
$3,500–$8,500 · stay 3–8 nights; parent stay expected
AVSD Repair (Atrioventricular Septal Defect) cost in India
$8,000–$18,500 · stay 8–16 nights; parent stay expected
TOF Repair (Tetralogy of Fallot) cost in India
$6,500–$16,000 · stay 8–16 nights; parent stay expected
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 11 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
VSD Closure (Ventricular Septal Defect) cost sheet · All treatment costs in India · Pediatric Cardiac Surgery costs



