
Last updated: 12 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Biliary Reconstruction in India is typically planned at $8,000–$20,000. The cost may cover the named specialist, theatre time, stated imaging, routine medicines and the listed hospital stay, while extra reconstruction, staplers, ICU nights or another procedure depend on the written scope. The stored stay is 7–14 nights, but monitoring and travel timing are individualized.
Major price drivers are injury level or number of ducts, sepsis and preoperative drainage, timing of repair, prior open biliary surgery. Revision surgery, a different approach or an unexpected reconstruction can materially change the bill.
- India cost range
- $8,000–$20,000
- Typical starting point
- $8,000
- Typical hospital stay
- 7–14 nights
- Procedure time
- Often 3–6 hours depending on adhesions and duct number
- Recovery
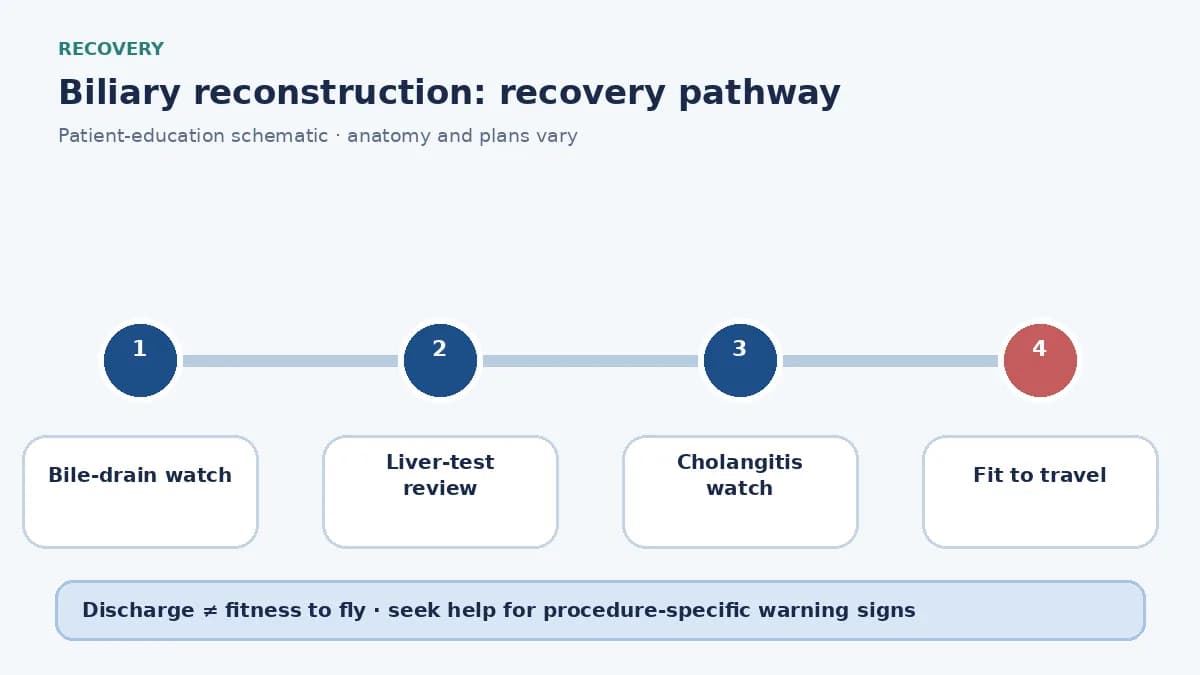
- Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis.
Major cost factors: injury level or number of ducts, sepsis and preoperative drainage, timing of repair, prior open biliary surgery. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed scope; complications; premium devices; extended aftercare; travel and living.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
Biliary reconstruction repairs or replaces a damaged, strictured or surgically divided bile duct, often with a hepaticojejunostomy that joins bile ducts to a Roux loop of jejunum. It may be considered after bile-duct injury, selected strictures, excision of a choledochal cyst or when a cancer resection leaves ducts that cannot be joined end to end.
Assessment includes MRCP or percutaneous cholangiography, liver function, sepsis control, injury classification if post-cholecystectomy, and whether a delayed repair after drainage is safer than an immediate join. This is not a routine cholecystectomy and not ERCP stenting. A percutaneous drain may still be needed first. Reconstruction does not restore a perfectly normal biliary tree.
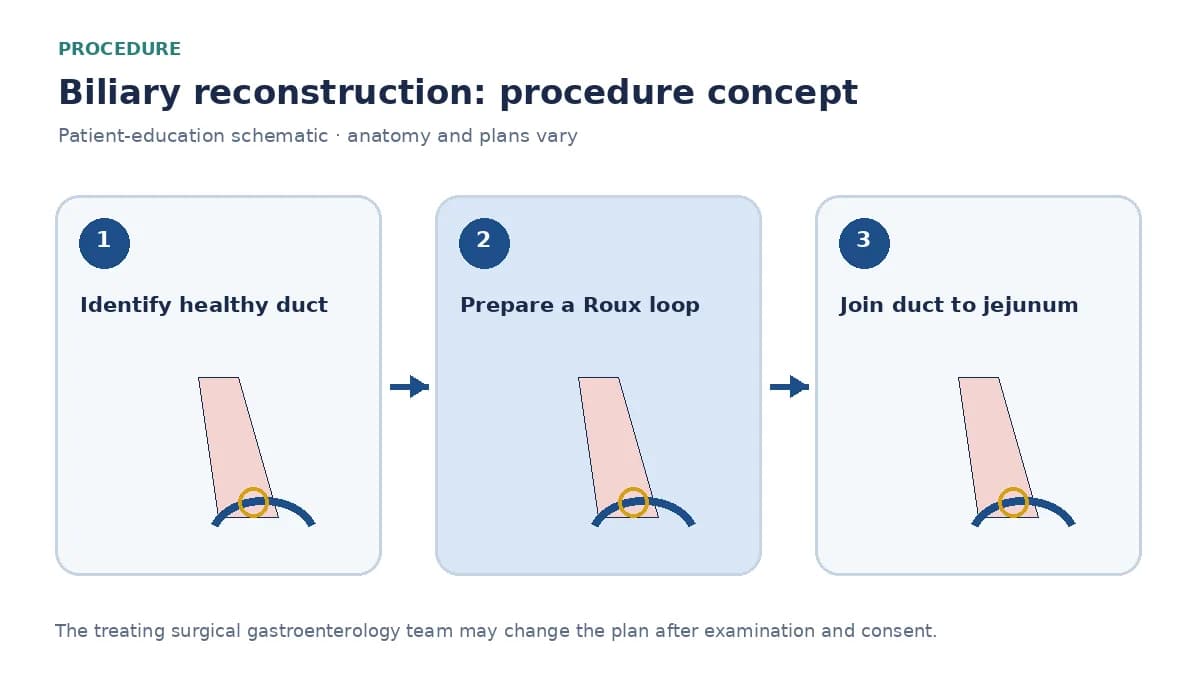
After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned. Selection among Hepaticojejunostomy after injury, Delayed reconstruction after drainage, Reconstruction after planned bile-duct resection depends on anatomy, disease extent and the treating team's assessment, not on a package label.
The catalog supplies $8,000–$20,000 for India, $35,000–$85,000 for a United States self-pay reference and 7–14 nights for broad planning. These values are not city tariffs, medical acceptance, outcome forecasts or final bills.
What Is Biliary Reconstruction?
Biliary reconstruction repairs or replaces a damaged, strictured or surgically divided bile duct, often with a hepaticojejunostomy that joins bile ducts to a Roux loop of jejunum.
After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned.
This is not a routine cholecystectomy and not ERCP stenting. A percutaneous drain may still be needed first. Reconstruction does not restore a perfectly normal biliary tree.

When Is Biliary Reconstruction Considered?
It may be considered after bile-duct injury, selected strictures, excision of a choledochal cyst or when a cancer resection leaves ducts that cannot be joined end to end.
Suitability depends on individual assessment by a qualified surgical gastroenterologist or GI surgeon and, where relevant, hepatology, oncology, interventional radiology or a multidisciplinary team. This page cannot diagnose a reader or recommend a personal operation.
How the operation is performed, recovery and variations →
Biliary Reconstruction cost in India
The $8,000–$20,000 value is GAF's stored national planning range for biliary reconstruction. It should be replaced by an itemized quotation tied to a named hepatobiliary surgeon, campus, reconstruction plan and ICU assumption.
Cost can change with injury level or number of ducts, sepsis and preoperative drainage, timing of repair, prior open biliary surgery, need for liver resection. A different approach, extra organ resection or a combined procedure describes a different episode.
Compare estimates line by line. Do not derive separate Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad prices from this national range, and keep flights, lodging, companion costs, long-term medicines and nutrition support visible.
Planning Range ≠ Final Hospital Quotation. A qualified surgical gastroenterology team must review records, anatomy and alternatives before an itemized offer is meaningful.
Biliary Reconstruction cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a surgical estimate, not a dollar amount for each row.
- Clinical assessment
- Named surgical gastroenterology consultation, records review and procedure-focused examination when explicitly listed.
- Surgical episode
- Specialist, theatre time, standard instruments and recovery-room or ICU care within the written scope.
- Imaging and tests
- Stated blood tests and listed CT, MRI, MRCP, endoscopy or ultrasound only; unlisted advanced imaging is extra.
- Routine aftercare
- Standard medicines, nutrition as listed, observation and stated early follow-up only when itemized.
- Documentation
- Discharge summary, operative report and pathology or immunosuppression details where applicable.
- Listed Roux biliary join
- Only the stated hepaticojejunostomy; extra ducts or stents may be extra.
Planning range or quotation?
The $8,000–$20,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Biliary Reconstruction package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Clinical assessment
Named surgical gastroenterology consultation, records review and procedure-focused examination when explicitly listed.
Usually included
Surgical episode
Specialist, theatre time, standard instruments and recovery-room or ICU care within the written scope.
Usually included
Imaging and tests
Stated blood tests and listed CT, MRI, MRCP, endoscopy or ultrasound only; unlisted advanced imaging is extra.
Usually included
Routine aftercare
Standard medicines, nutrition as listed, observation and stated early follow-up only when itemized.
Usually included
Documentation
Discharge summary, operative report and pathology or immunosuppression details where applicable.
Usually included
Listed Roux biliary join
Only the stated hepaticojejunostomy; extra ducts or stents may be extra.
May be charged separately
May be separate
Changed scope
Extra organ resection, a stoma, vein reconstruction or a different operation found after arrival.
May be separate
Complications
Unplanned tests, ICU extension, reoperation, prolonged stay or readmission unless expressly covered.
May be separate
Premium devices
Additional staplers, mesh, implants or energy devices beyond the written estimate.
May be separate
Extended aftercare
Long-term medicines, nutrition support, stoma supplies, remote review or follow-up beyond the included period.
May be separate
Travel and living
Flights, visa, local transport, lodging, meals, companion costs and personal expenses.
May be separate
Unplanned hepatectomy
A different CMS procedure if a lobe must come out.
Catalog inclusions listed for this pathway: hpb / gi surgery consultation and records review; named surgeon on camera before travel; theatre, icu and overnight stay as quoted; histology, drain or immunosuppression follow-up as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Injury level or number of ducts
- High hilar injuries are not a mid-duct join.
- Sepsis and preoperative drainage
- PTBD weeks change the episode before theatre.
- Timing of repair
- Immediate versus delayed reconstruction are different resource stories.
- Prior open biliary surgery
- A hostile porta hepatis extends theatre time.
- Need for liver resection
- Combined hepatectomy belongs on another sheet if that is the honest plan.
Approaches to Biliary Reconstruction
After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned. The options below are clinical strategies, not consumer upgrades.
A named hepatobiliary surgeon should explain which route fits the individual's anatomy and condition, and what finding could change or cancel it.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Hepaticojejunostomy after injury | Selected from anatomy, diagnosis, risk and follow-up needs | No separate GAF sheetRelative complexity only | The usual repair when the duct cannot be joined primarily. |
| Delayed reconstruction after drainage | Selected from anatomy, diagnosis, risk and follow-up needs | No separate GAF sheetRelative complexity only | Sepsis and inflammation may force weeks of PTBD first. |
| Reconstruction after planned bile-duct resection | Selected from anatomy, diagnosis, risk and follow-up needs | No separate GAF sheetRelative complexity only | Oncologic or choledochal-cyst excision with a planned Roux join. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
What Biliary Reconstruction can and cannot address
This is not a routine cholecystectomy and not ERCP stenting. A percutaneous drain may still be needed first. Reconstruction does not restore a perfectly normal biliary tree.
A consultation should separate the intended target — oesophagus, stomach, small bowel, colon, rectum, liver, bile duct, pancreas, abdominal wall or another named structure — from other disease that may still need medicines, endoscopy, chemotherapy, radiation or a different operation.
No page can promise complete disease clearance, cure, weight change, graft function or a complication-free course.
Risks and Considerations after Biliary Reconstruction
Risks include bile leak, cholangitis, anastomotic stricture, bleeding, liver dysfunction, need for percutaneous drainage and reoperation.
This is not an exhaustive consent list and assigns no probability. Risk depends on anatomy, prior surgery, nutrition, infection, emergency versus planned timing and the actual technique.
Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis. A lower price does not reduce the need for ICU access or structured follow-up.
Recovery and travel after Biliary Reconstruction
Ward with selective ICU; stored 7–14 nights assumes a controlled join, not uncontrolled biliary sepsis. Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis.
International patients should distinguish procedure time, hospital stay, recommended days in India and longer-term recovery at home. Discharge is not the same as fitness to fly.
Follow-up reviews liver tests, cholangitis symptoms and whether imaging of the join is needed. Flights should remain flexible until the team confirms diet, wound status, drain or stoma stability and travel fitness.
Biliary Reconstruction cost: India vs other medical tourism destinations
India and United States values use stored GAF catalog ranges. Other countries require quotations because comparable, procedure-specific packages are not reliably available in the catalog.
A meaningful comparison holds clinician, licensed facility, surgical approach, reconstruction, ICU, complication terms and follow-up constant.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $8,000–$20,000 | Baseline | GAF catalog planning range. The stored India figure is a national planning range. It does not establish candidacy, open versus laparoscopic versus robotic access, ICU nights, reconstruction or a final quotation. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Compare the exact GI operation, reconstruction, ICU assumption, pathology and follow-up rather than a headline package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Depends on procedure and hospital. International coordination does not establish HPB, transplant or colorectal capability, ICU backup or continuity after return. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Professional, facility, device, ICU, pharmacy and follow-up charges may be billed separately. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Request a self-pay estimate tied to the actual anatomy, reconstruction and ICU plan rather than a general GI-surgery package. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Eligibility, professional billing, device scope and post-travel GI-surgery follow-up require direct confirmation. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, quote boundaries, emergency access and who reviews pathology, immunosuppression or a stoma after return. |
| United States | $35,000–$85,000 | ≈4.3× India | Stored self-pay reference. Facility, specialist, device, ICU and follow-up charges may be billed separately; $35,000–$85,000 is a comparison range, not a bundled quotation. |
International comparisons are indicative and may not represent identical packages. Anatomy, reconstruction, ICU nights, complications, currency and length of stay can change the final amount.
Why do international patients consider India for biliary reconstruction?
Some international patients evaluate India for access to a named hepatobiliary surgeon, HPB or colorectal infrastructure and a national self-pay planning range below the stored United States reference. Price alone is not a clinical reason to travel.
The relevant questions are individualized acceptance, licensed facility, ICU and blood-bank backup, reconstruction or graft capability where relevant and continuity after return.
No provider is ranked and no outcome is promised. Unstable sepsis, untreated jaundice, inadequate records or safer established care near home may make travel inappropriate.
Hospitals and GI surgery centres for Biliary Reconstruction in India
Cards follow exact live entity relationships for Biliary Reconstruction. A general GI-surgery or accreditation label does not establish current case acceptance, ICU backup or outcomes.
Indraprastha Apollo Hospital
 JCI Accredited
 NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
2 listed doctors for this pathway
Languages listed: English, Hindi
Apollo Hospitals, Navi Mumbai
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi, Marathi
Fortis Hospital, Shalimar Bagh
- JCI Accredited
- NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi
Medanta - The Medicity
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
3 listed doctors for this pathway
Languages listed: English, Hindi
Biliary Reconstruction hospitals in India · Talk to a treatment coordinator
Biliary Reconstruction specialists in India
Profiles are drawn dynamically only when Biliary Reconstruction appears in an exact current CMS procedure relationship. Verify specialty scope, availability and campus; placement is not a ranking, volume or outcome claim.

Dr. Adarsh Chaudhary
Surgical Gastroenterology
15+ years Experience
Whipple Procedure · Pancreatic Cancer (surgical management) · Complex HPB Tumor Surgery
English, Hindi
Dr. Amruth Raj
Surgical Gastroenterology
7+ years Experience
Deceased Donor Liver Transplant · Liver Resection/Hepatectomy · Whipple Procedure
English, Hindi, Marathi
Dr. Arvinder Singh Soin
Surgical Gastroenterology
38+ years Experience
Deceased Donor Liver Transplant · Pediatric Liver Transplant · Liver Retransplantation
English, Hindi
Dr. Alok Kumar Pandey
Surgical Gastroenterology
13+ years Experience
Liver Resection/Hepatectomy · Deceased Donor Liver Transplant · Whipple Procedure
English, Hindi
Dr. Prashant Vilas Bhangui
Surgical Gastroenterology
20+ years Experience
Deceased Donor Liver Transplant · Liver Resection/Hepatectomy · Liver Tumors (Operable)
English, Hindi
Dr. Sourabh Jindal
Surgical Gastroenterology
5+ years Experience
Whipple Procedure · Liver Resection/Hepatectomy · Biliary Reconstruction
English, Hindi
Dr. V Arun Kumar
Surgical Gastroenterology
13+ years Experience
Liver Transplant Surgery · Deceased Donor Liver Transplant · Liver Resection/Hepatectomy
English, Hindi
Biliary Reconstruction doctors in India (7 listed) · Get a personalized cost estimate
Biliary Reconstruction cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad retain $8,000–$20,000 because no verified city tariffs are stored. Their pages address distinct airport, geography, climate, lodging and follow-up logistics without inventing local prices.
Doctor and hospital cards resolve only from CMS entities carrying the exact Biliary Reconstruction relationship. Missing mappings leave cards empty rather than borrowing generic GI-surgery entities.
Swipe to compare Indian cities →
Delhi NCR
$8,000–$20,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Delhi NCR-only tariff is stored for biliary reconstruction. Use $8,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
3 hospitals · 6 doctors
Mumbai
$8,000–$20,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Mumbai-only tariff is stored for biliary reconstruction. Use $8,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 1 doctor
Bengaluru
$8,000–$20,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Bengaluru-only tariff is stored for biliary reconstruction. Use $8,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Chennai
$8,000–$20,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Chennai-only tariff is stored for biliary reconstruction. Use $8,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Hyderabad
$8,000–$20,000
India planning band — not a city quote
Typical stay 7–14 nights
No verified Hyderabad-only tariff is stored for biliary reconstruction. Use $8,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for biliary reconstruction
What should international patients budget beyond the surgery?
A complete biliary reconstruction trip budget extends beyond $8,000–$20,000. Include remote review, tests outside the estimate, companion travel, nearby lodging, medicines, nutrition support and a complication contingency.
Travel should follow written clinical acceptance and an itemized estimate. A visa invitation or directory profile is not medical clearance.
- Records review
- Assessment includes MRCP or percutaneous cholangiography, liver function, sepsis control, injury classification if post-cholecystectomy, and whether a delayed repair after drainage is safer than an immediate join.
- Specialist assessment
- It may be considered after bile-duct injury, selected strictures, excision of a choledochal cyst or when a cancer resection leaves ducts that cannot be joined end to end. This is not a routine cholecystectomy and not ERCP stenting. A percutaneous drain may still be needed first. Reconstruction does not restore a perfectly normal biliary tree.
- Procedure and alternatives
- Discuss Hepaticojejunostomy after injury, Delayed reconstruction after drainage, Reconstruction after planned bile-duct resection, medicines and what could alter the plan.
- Itemized estimate
- Match clinician, campus, approach, reconstruction, ICU, imaging, monitoring, exclusions and emergency terms.
- Arrival reassessment
- Repeat examination, blood tests, imaging or endoscopy only when clinically indicated before final consent.
- Surgery and monitored recovery
- After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned. Ward with selective ICU; stored 7–14 nights assumes a controlled join, not uncontrolled biliary sepsis.
- Discharge and nearby review
- Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis. Confirm medicines, warning signs and emergency contacts.
- Handover home
- Follow-up reviews liver tests, cholangitis symptoms and whether imaging of the join is needed. Carry the operative report, pathology and device or immunosuppression details where relevant.
- Treatment episode$8,000–$20,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay7–14 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for biliary reconstruction in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Submit relevant records
MRCP or percutaneous cholangiogram; Injury or operative notes; Liver-function trend; Drain or ERCP history.
Obtain specialist review
A named hepatobiliary surgeon assesses indication, anatomy, alternatives and travel suitability.
Clarify goals and uncertainty
Discuss symptoms, prior treatment and what this operation cannot promise.
Confirm individualized candidacy
It may be considered after bile-duct injury, selected strictures, excision of a choledochal cyst or when a cancer resection leaves ducts that cannot be joined end to end.
Compare itemized estimates
Hold procedure, reconstruction, ICU, imaging, monitoring and emergency terms constant.
Plan flexible travel
Arrange documents, refundable travel, a capable companion and lodging near the exact campus.
Repeat assessment after arrival
Assessment includes MRCP or percutaneous cholangiography, liver function, sepsis control, injury classification if post-cholecystectomy, and whether a delayed repair after drainage is safer than an immediate join.
Complete informed consent
Review alternatives, risks include bile leak, cholangitis, anastomotic stricture, bleeding, liver dysfunction, need for percutaneous drainage and reoperation. and the possibility that the plan changes.
Undergo the planned operation
After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned.
Complete monitored recovery
Ward with selective ICU; stored 7–14 nights assumes a controlled join, not uncontrolled biliary sepsis. Establish safe oral intake, drain or stoma care and activity limits.
Attend nearby follow-up
Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis. Obtain explicit fitness-to-fly advice.
Transfer care home
Follow-up reviews liver tests, cholangitis symptoms and whether imaging of the join is needed. Share the report and emergency plan with the local clinician.
Documents to prepare
- MRCP or percutaneous cholangiogram
- Injury or operative notes
- Liver-function trend
- Drain or ERCP history
- Current medicines, allergies and recent blood tests where relevant
- Surgical gastroenterology notes and any available endoscopy, colonoscopy, CT, MRI, MRCP, PET-CT or ultrasound reports
- Previous operative notes, pathology, chemotherapy or radiation records where relevant
- Passport and companion information needed for travel and consent
Clinical detail
How the procedure is performed
After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned.
Relevant options include Hepaticojejunostomy after injury, Delayed reconstruction after drainage, Reconstruction after planned bile-duct resection; they are not interchangeable package names.
Ward with selective ICU; stored 7–14 nights assumes a controlled join, not uncontrolled biliary sepsis. Often 3–6 hours depending on adhesions and duct number.
Main variations
- Hepaticojejunostomy after injury
- The usual repair when the duct cannot be joined primarily.
- Delayed reconstruction after drainage
- Sepsis and inflammation may force weeks of PTBD first.
- Reconstruction after planned bile-duct resection
- Oncologic or choledochal-cyst excision with a planned Roux join.
Preparation
Assessment includes MRCP or percutaneous cholangiography, liver function, sepsis control, injury classification if post-cholecystectomy, and whether a delayed repair after drainage is safer than an immediate join.
The receiving team should reconcile anticoagulants, nutrition, infection, previous abdominal surgery and any bowel-prep or fasting plan before a date is fixed.
Follow fasting and medicine-hold instructions from the treating team. Report fever, jaundice, bleeding, severe pain or another material change before travel.
Hospital stay and recovery
Ward with selective ICU; stored 7–14 nights assumes a controlled join, not uncontrolled biliary sepsis. Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis.
Diet, wound care, drain or stoma instructions and activity limits are stated. Written instructions take priority over generic travel advice.
Risks include bile leak, cholangitis, anastomotic stricture, bleeding, liver dysfunction, need for percutaneous drainage and reoperation.
Follow-up reviews liver tests, cholangitis symptoms and whether imaging of the join is needed. Seek urgent help for fever with jaundice, bile flooding the drain, abdominal pain or shaking chills; use the treating team's emergency thresholds.
How to compare Biliary Reconstruction quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is biliary reconstruction being considered, and what medical, endoscopic or surgical options were discussed?
- How were my imaging, endoscopy, pathology and previous operations assessed?
- Who is the named hepatobiliary surgeon, and at which exact campus will the operation occur?
- Does the quotation use the exact name Biliary Reconstruction?
- Which consultations, blood tests, imaging and endoscopy are included?
- Are specialist, theatre, anaesthesia and recovery-room fees included?
- Is this an open, laparoscopic or robotic plan, and what finding would change it?
- Are staplers, mesh, drains or other devices assumed, and are manufacturer details provided?
- Would extra organ resection, a stoma, vein reconstruction or a different procedure change the quotation?
- How many ward or ICU nights and which room category are included?
- How are extra nights, leak, bleed, reoperation or a complication billed?
- Which discharge medicines, nutrition support and stoma supplies are included?
- Is pathology charging included if tissue is taken?
- When can I fly, eat, work or resume other activity?
- Which follow-up visits, drain reviews or immunosuppression reviews are included?
- How are complications handled after I leave India?
- When and by whom will fitness to fly be assessed?
- What operative report, images and emergency contacts will I receive?
- Which costs are explicitly excluded?
- Who will coordinate care with my clinician after I return home?
- Is delayed repair after PTBD assumed?
- How many duct orifices are being joined?
- Is a percutaneous drain included?
Frequently asked questions
How much does biliary reconstruction cost in India?
Biliary Reconstruction is typically planned at $8,000–$20,000. This stored national range is not a quotation; anatomy, reconstruction, ICU, devices, monitoring and written terms determine the final amount.
What is biliary reconstruction?
Biliary reconstruction repairs or replaces a damaged, strictured or surgically divided bile duct, often with a hepaticojejunostomy that joins bile ducts to a Roux loop of jejunum.
When is biliary reconstruction considered?
It may be considered after bile-duct injury, selected strictures, excision of a choledochal cyst or when a cancer resection leaves ducts that cannot be joined end to end.
Is GI surgery in India automatically cheaper?
It may cost less than some self-pay markets, but quotations are not automatically comparable. Compare exact scope, clinician, facility, reconstruction, ICU and follow-up.
What assessment is needed before surgery?
Assessment includes MRCP or percutaneous cholangiography, liver function, sepsis control, injury classification if post-cholecystectomy, and whether a delayed repair after drainage is safer than an immediate join.
What happens during the operation?
After adhesions are cleared and healthy duct mucosa is identified, a Roux-en-Y jejunal loop is usually brought up for hepaticojejunostomy. Drains and, sometimes, anastomotic stents are placed as planned.
How long does biliary reconstruction take?
Often 3–6 hours depending on adhesions and duct number. Actual timing depends on anatomy, findings during the case and the clinical course.
How long is the hospital stay?
Ward with selective ICU; stored 7–14 nights assumes a controlled join, not uncontrolled biliary sepsis. Discharge is based on clinical criteria, not a package calendar.
What are the important risks?
Risks include bile leak, cholangitis, anastomotic stricture, bleeding, liver dysfunction, need for percutaneous drainage and reoperation.
When can an international patient fly home?
There is no fixed flight day. Recovery watches bile in the drain, liver tests and oral intake. Flying waits on drain plan and absence of uncontrolled leak or cholangitis. The treating team must document travel fitness.
Which Indian cities offer this procedure?
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad have relevant surgical gastroenterology ecosystems, but actual availability requires an exact clinician and campus confirmation.
What follow-up is needed after returning home?
Follow-up reviews liver tests, cholangitis symptoms and whether imaging of the join is needed. The plan should name who reviews pathology, drains, stoma care or immunosuppression.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Bile Duct Cancer Surgery cost in India
$10,000–$26,000 · stay 8–16 nights
Gallbladder Cancer Surgery cost in India
$7,000–$18,000 · stay 6–12 nights
Whipple Procedure (Pancreaticoduodenectomy) cost in India
$14,000–$32,000 · stay 10–18 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 12 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Biliary Reconstruction cost sheet · All treatment costs in India · Surgical Gastroenterology costs



