
Last updated: 13 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Rigid Bronchoscopy in Chennai is planned against $1,200–$3,500 per theatre procedure, with 1–3 nights used for broad trip planning. Neither is a local tariff, recommendation or acceptance promise.
Confirm the named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy, campus, approach, rigid ventilating barrel and stated intervention, pathology or microbiology, oxygen plan and where urgent respiratory review would happen.
- India cost range
- $1,200–$3,500
- Typical starting point
- $1,200
- Typical hospital stay
- 1–3 nights
- Procedure time
- Often 45 minutes to several hours, depending on obstruction complexity, ventilation, devices and bleeding control
- Recovery
- Throat or jaw soreness, hoarseness, cough and fatigue are expected possibilities after general anaesthesia.
Major cost factors: airway urgency and obstruction severity, general anaesthesia and ventilation mode, therapeutic instruments, stent or implant. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed procedural scope; complications and escalation; premium devices and consumables; advanced diagnostics; travel and ongoing care.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
Rigid Bronchoscopy in Chennai
Rigid bronchoscopy may be considered for critical central-airway obstruction, a large or sharp foreign body, major airway bleeding, silicone-stent placement or removal, mechanical tumour coring, dilation, or when a secure large-bore corridor is needed. CT anatomy, urgency, anaesthetic risk and availability of safer alternatives guide selection. Planning includes thin-section CT with airway diameter and obstruction length, distal-airway patency, vascular proximity, neck mobility and dentition, oxygen and ventilation status, blood count and coagulation, anticoagulants, cross-match when bleeding is plausible and formal anaesthesia review. Rescue plans may include ICU, thoracic surgery, embolization or extracorporeal support in exceptional high-risk obstruction.
Some hospital corridors have direct airport access, but imaging, bronchoscopy, pathology and transplant follow-up may occur in different buildings. Confirm the complete pathway. Sedation, breathlessness, oxygen and a chest drain can limit independent travel, so arrange a companion.
Use air-conditioned, flexible lodging near the respiratory campus with reliable electricity for any oxygen concentrator or PAP device. Heat and humidity increase fluid loss and fatigue; patients using oxygen should follow their prescribed flow and equipment-safety plan rather than changing it themselves.
Doctor and hospital cards in Chennai resolve only from exact live CMS relationships for Rigid Bronchoscopy. If that exact relationship is absent, cards must remain empty; a generic Pulmonology or hospital label cannot verify current acceptance. This is a catalog gap, not an availability or quality claim.
Send records before non-refundable travel. A remote opinion can change after examination, image review, oxygen assessment and anaesthesia review in person.
What rigid bronchoscopy typically costs in Chennai
Near-complete obstruction requires larger teams, rapid theatre access and intensive respiratory rescue planning. Complex jet or controlled ventilation and prolonged theatre time alter anaesthesia resources.
Ask for clinician, technique, anaesthesia, devices, suite, ward nights, pathology, follow-up and complication terms in writing.
Budget separately for travel through Chennai International Airport, nearby lodging, companion support, medicines, oxygen equipment and extra nights if pathology or respiratory monitoring delays departure.
What moves the quote in Chennai
- Airway urgency and obstruction severity
- Near-complete obstruction requires larger teams, rapid theatre access and intensive respiratory rescue planning.
- General anaesthesia and ventilation mode
- Complex jet or controlled ventilation and prolonged theatre time alter anaesthesia resources.
- Therapeutic instruments
- Forceps, balloons, suction catheters, laser fibres, cryoprobes and coagulation devices are separately scoped.
- Stent or implant
- Silicone or covered metal stent model, diameter, length and delivery system can dominate consumable cost.
Medical travel through Chennai
Send thin-section ct chest images defining central-airway calibre and distal patency, prior bronchoscopy images, operative notes, stent model and pathology and current oxygen or respiratory-support details where applicable.
Obtain written acceptance from a named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy and verify the campus, anaesthesia, ICU backup, device availability and pathology pathway.
Throat or jaw soreness, hoarseness, cough and fatigue are expected possibilities after general anaesthesia. Breathing, voice, bleeding and chest imaging are reassessed as indicated. Return travel is deferred until the airway is stable, any device plan is documented and anaesthesia and pulmonology teams clear it. Heat and humidity increase fluid loss and fatigue; patients using oxygen should follow their prescribed flow and equipment-safety plan rather than changing it themselves. Carry the procedure, pathology and oxygen or device plan for local follow-up.
Hospitals and units listed in Chennai
Doctor and hospital cards in Chennai resolve only from exact live CMS relationships for Rigid Bronchoscopy. If that exact relationship is absent, cards must remain empty; a generic Pulmonology or hospital label cannot verify current acceptance. This is a catalog gap, not an availability or quality claim.
General accreditation does not establish current rigid bronchoscopy acceptance or equipment. Name the theatre campus with rigid ventilating bronchoscopes in appropriate sizes, interventional tools, an anaesthetist experienced in shared-airway ventilation, respiratory critical care and a defined pathway to embolization or thoracic surgery when clinically required.
Rigid Bronchoscopy doctors in Chennai · Rigid Bronchoscopy hospitals in Chennai · Rigid Bronchoscopy cost in India
What Is Rigid Bronchoscopy?
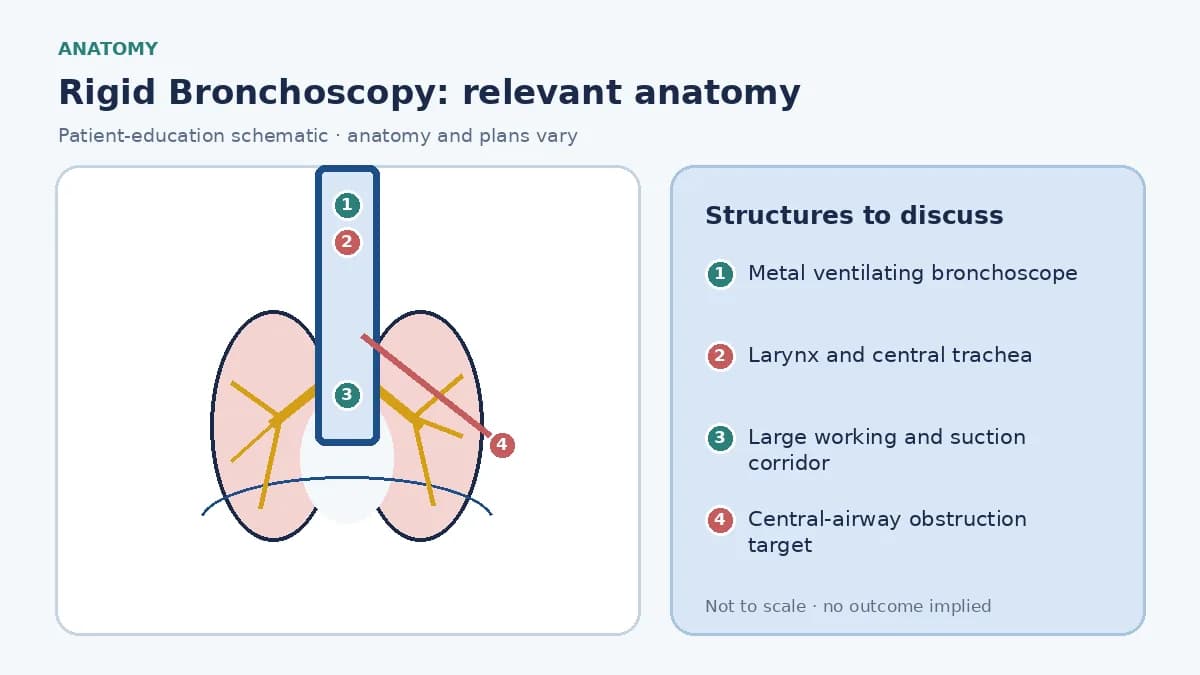
Rigid bronchoscopy places a straight, hollow metal ventilating barrel through the mouth and larynx into the trachea or main bronchi under general anaesthesia. Its wide lumen secures a central-airway corridor for high-volume suction, optical instruments, forceps, stents and bleeding-control or tumour-debulking tools.
When Might Rigid Bronchoscopy Be Considered?
Rigid bronchoscopy may be considered for critical central-airway obstruction, a large or sharp foreign body, major airway bleeding, silicone-stent placement or removal, mechanical tumour coring, dilation, or when a secure large-bore corridor is needed. CT anatomy, urgency, anaesthetic risk and availability of safer alternatives guide selection.
How the operation is performed, recovery and variations →
Rigid Bronchoscopy cost in India
$1,200–$3,500 is the stored India planning range for rigid bronchoscopy, per theatre procedure, and $5,000–$15,000 the stored self-pay comparison. Neither is a guaranteed package; changed technique, extra pathology, ICU support or a longer stay alters the amount.
A usable estimate names the clinician, campus, approach, rigid ventilating barrel and stated intervention, sedation or anaesthesia, oxygen, ward nights, specimen studies and follow-up, with professional, facility, device, imaging and laboratory lines separated.
Budget separately for flights, visa, insurance, transfers, companion, lodging, meals, home oxygen or equipment and local follow-up unless included.
Planning Range ≠ Final Hospital Quotation. Current imaging, respiratory reserve, oxygen needs and assessment by a named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy come before technique, risks and a final offer are meaningful.
Planning range or quotation?
The $1,200–$3,500 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Rigid Bronchoscopy package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Named respiratory consultation
Records and imaging review by the operating pulmonologist when explicitly listed.
Usually included
Pre-procedure assessment
Stated blood tests, ECG, oxygen assessment, urine tests and anaesthesia review; unlisted work-up is extra.
Usually included
Procedure suite and sedation
Bronchoscopy or procedure-room time, standard monitoring, sedation or anaesthesia and recovery care within scope.
Usually included
Quoted hospital stay
The stated day-care or ward category, routine oxygen, nursing and medicines for the listed nights.
Usually included
Standard specimen processing
Histopathology, cytology or microbiology only when itemized; molecular panels and special stains may be separate.
Usually included
Rigid ventilating barrel and stated intervention
Theatre, rigid scopes, standard telescopes and suction plus only the named extraction, dilation, haemostasis or device work.
May be charged separately
May be separate
Changed procedural scope
A diagnostic scope becoming therapeutic, rigid-bronchoscopy conversion or an additional biopsy or drainage procedure.
May be separate
Complications and escalation
Unplanned ICU, ventilation, transfusion, chest drain, re-intervention, readmission or extra nights unless covered.
May be separate
Premium devices and consumables
Airway stents, valves, cryoprobes, catheters and single-use scopes beyond the written specification.
May be separate
Advanced diagnostics
PET-CT, molecular or biomarker testing, special microbiology, expert pathology review and repeat imaging unless listed.
May be separate
Travel and ongoing care
Flights, visa, insurance, lodging, companion, home oxygen, rehabilitation and treatment after return.
May be separate
Stents, ablation devices and rescue escalation
Implants, premium single-use tools, repeat bronchoscopy, embolization, surgery, transfusion and ICU are excluded unless itemized.
Catalog inclusions listed for this pathway: pulmonology consultation and records review; named consultant on camera before travel; scope, anaesthesia and overnight stay as quoted; histology, drain or icu step-down as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Airway urgency and obstruction severity
- Near-complete obstruction requires larger teams, rapid theatre access and intensive respiratory rescue planning.
- General anaesthesia and ventilation mode
- Complex jet or controlled ventilation and prolonged theatre time alter anaesthesia resources.
- Therapeutic instruments
- Forceps, balloons, suction catheters, laser fibres, cryoprobes and coagulation devices are separately scoped.
- Stent or implant
- Silicone or covered metal stent model, diameter, length and delivery system can dominate consumable cost.
- Bleeding preparedness
- Cross-matched blood, blockers, embolization or surgical backup depends on vascular risk.
- Postoperative acuity
- Extubation, ward observation, high-dependency or ICU care varies with reserve and intervention.
- Imaging and physiological testing
- Chest CT or HRCT, PET-CT, spirometry, DLCO, arterial blood gas and echocardiography add lines only when clinically relevant.
- Respiratory reserve and anaesthesia
- Low oxygen, severe airflow limitation, pulmonary hypertension and comorbidity change sedation, monitoring and ICU probability.
- Hospital category and room
- Campus tier, room class, bronchoscopy-suite resources and city shift facility and nursing charges.
- Pathology and follow-up
- Tissue adequacy, microbiology, molecular testing, repeat procedures and review after results alter the complete diagnostic cost.
Rigid Bronchoscopy: approaches and where they differ
The approach follows the clinical question, imaging target, airway or pleural anatomy, respiratory reserve and available equipment. Each option has different consumables, monitoring and follow-up, so the quotation must name it.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Rigid diagnostic and airway-control examination | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | The barrel secures ventilation and suction while central anatomy is assessed, with flexible inspection or biopsy added if agreed. |
| Foreign-body or clot extraction corridor | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | Large optical forceps, baskets and suction remove an obstruction while limiting loss of the object into the opposite bronchus. |
| Dilation and stent platform | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | Mechanical or balloon dilation precedes placement, repositioning or removal of an airway stent, with sizing based on CT and bronchoscopy. |
| Debulking and haemostasis platform | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | Mechanical coring, electrocautery, argon plasma coagulation, laser or cryotherapy may restore central patency and control bleeding. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
Interventional pulmonology: the subspecialty behind Rigid Bronchoscopy
Interventional pulmonology uses flexible and rigid bronchoscopes, ultrasound, thermal or cryotherapy tools, balloons and stents to diagnose and treat central-airway disease. The service requires an equipped bronchoscopy suite, anaesthesia and a plan for bleeding or respiratory deterioration.
The metal barrel is an airway-control platform
Unlike a flexible scope, the rigid bronchoscope is a straight open tube that can ventilate while blood, clot, tumour or secretions are suctioned through a broad lumen. The operator can pass optical forceps and other instruments without repeatedly occupying the patient's natural airway.
That control comes with general anaesthesia and limited reach. Neck, jaw, teeth and larynx must accommodate insertion, and distal segmental disease still needs a flexible scope. The benefit-risk decision is therefore about central-airway control, not image quality alone.
Airway and bleeding rescue must be planned before induction
Muscle relaxation and positive-pressure ventilation can worsen a precarious obstruction. CT review identifies the narrowest point, patent distal lung and vessel relationships; the team agrees how oxygenation will be maintained and what happens if the barrel cannot cross the lesion.
Major haemorrhage can rapidly fill both bronchi. Large suction, bronchial blockers, positioning, coagulation, blood products and access to interventional radiology or surgery may be required. Listing equipment is not enough: roles and escalation location should be explicit.
Risks and side effects of Rigid Bronchoscopy
Risks include dental, lip or laryngeal injury, swelling, bronchospasm, low oxygen, high carbon dioxide, arrhythmia, anaesthetic complications, bleeding, airway tear or perforation, pneumothorax, infection and incomplete relief. Severe haemorrhage, airway loss, ventilation failure or need for emergency surgery are uncommon but central to consent.
Ask before travel who pays for unplanned ventilation, ICU, chest drainage, transfusion, repeat biopsy, readmission or a second procedure.
Rigid Bronchoscopy cost: India vs other medical tourism destinations
India and US values use stored GAF planning ranges; other countries require direct quotations. Compare the same intent, technique, devices, sedation, pathology, ward category and complication terms for rigid bronchoscopy.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $1,200–$3,500 | Baseline | GAF catalog planning range. The stored figure covers the named procedure only as written. Diagnostic versus therapeutic scope, anaesthesia, devices, pathology and ICU assumptions must be itemized. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Direct quotation required. Compare scope type, biopsy or intervention, anaesthesia, pathology, molecular testing and complication terms rather than a headline package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Direct quotation required. International coordination does not establish tissue adequacy, pathology turnaround, oxygen needs or continuity after return. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Direct quotation required. Pulmonologist, facility, anaesthesia, device, imaging, pathology and follow-up charges may be separate. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Request an estimate tied to the imaging target, technique, device, tissue studies and expected admission. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Private billing varies. Professional billing, eligibility, device scope and postoperative respiratory follow-up require provider confirmation. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, urgent respiratory access, pathology delivery and home handover. |
| United States | $5,000–$15,000 | ≈4.3× India | Stored self-pay reference. Pulmonologist, anaesthesia, facility, pathology and device charges may be separate; $5,000–$15,000 is a comparison range, not a quotation. |
International comparisons are indicative. Currency, changed findings, an added device or biopsy, pathology scope and respiratory monitoring alter the final amount.
Why do international patients consider India for rigid bronchoscopy?
Some patients consider India for rigid bronchoscopy because tertiary respiratory teams, interventional bronchoscopy, pleural services, pathology and respiratory critical care can be coordinated with a national planning range. Price alone is not a clinical reason to travel.
Evaluate clinician, licensure, campus, equipment, anaesthesia, ICU backup, pathology quality, urgent access and home handover. No provider is ranked and no outcome is promised; unstable breathing or suitable local care can make travel inappropriate.
Rigid Bronchoscopy hospitals in Chennai
Cards follow exact live relationships for Rigid Bronchoscopy. A general Pulmonology or accreditation label does not establish current acceptance, equipment or outcomes.
Campuses for this pathway are being confirmed. Ask the desk which houses currently quote it.
Rigid Bronchoscopy specialists in Chennai
Profiles appear only when Rigid Bronchoscopy is an exact current CMS relationship. Verify respiratory subspecialty, availability and campus; placement is not a ranking or outcome claim.
Named consultants for this pathway are being matched. Request a dossier and we will advise which campuses can quote it.
Rigid Bronchoscopy cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad use $1,200–$3,500 because no verified city tariff is stored. City overlays add campus geography, transfers, climate, oxygen logistics and follow-up without inventing prices. Cards require an exact current Rigid Bronchoscopy CMS relationship.
Swipe to compare Indian cities →
Delhi NCR
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–3 nights
No verified Delhi NCR-only tariff for rigid bronchoscopy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 2 doctors
Mumbai
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–3 nights
No verified Mumbai-only tariff for rigid bronchoscopy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 1 doctor
Bengaluru
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–3 nights
No verified Bengaluru-only tariff for rigid bronchoscopy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Chennai
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–3 nights
No verified Chennai-only tariff for rigid bronchoscopy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Hyderabad
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–3 nights
No verified Hyderabad-only tariff for rigid bronchoscopy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 1 doctor
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for rigid bronchoscopy
What should international patients budget beyond the pulmonology procedure?
International planning starts with records and a named respiratory question. A remote opinion is provisional until examination, image review and anaesthesia assessment confirm the plan.
- Send records
- Provide thin-section ct chest images defining central-airway calibre and distal patency and recent imaging files.
- Remote review
- A named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy reviews whether rigid bronchoscopy answers the clinical question.
- Define scope
- Name diagnostic or therapeutic intent, technique, samples, devices and likely stay.
- Itemize quotation
- Clinician, suite, anaesthesia, consumables, pathology, ward and exclusions.
- Plan travel
- Flexible flights, accessible lodging, companion and oxygen or equipment logistics.
- Arrive and reassess
- Examination, oxygen assessment, imaging and pre-anaesthetic review.
- Confirm consent
- Purpose, alternatives, risks, possible escalation and sample limitations.
- Complete procedure
- The consented rigid bronchoscopy with respiratory monitoring.
- Early recovery
- Airway, oxygen level, bleeding, pain and sedation recovery.
- Review results
- Imaging, cytology, histopathology or microbiology and any next step.
- Clear travel
- Written travel fitness, medicines, oxygen and urgent-contact plan.
- Handover home
- Procedure note, images, pathology and follow-up schedule for the home team.
- Treatment episode$1,200–$3,500
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay1–3 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for rigid bronchoscopy in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Define the question
Symptoms, diagnosis, imaging target and prior treatment.
Collect records
CT or HRCT, physiology, pathology and admission history.
Identify specialist
Named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy and exact campus.
Assess reserve
Oxygen, lung function, comorbidity and anaesthesia fitness.
Choose technique
Diagnostic or therapeutic method for the findings.
Compare quotes
Same scope, devices, samples, nights and follow-up.
Plan travel
Flexible travel, accessible lodging, companion and oxygen.
Confirm consent
Purpose, alternatives, risks and possible escalation.
Complete care
Procedure and monitored recovery.
Process samples
Cytology, histopathology, microbiology or molecular tests.
Attend review
Results, oxygen or device plan and next treatment.
Handover home
Procedure record and respiratory follow-up schedule.
Documents to prepare
- Thin-section CT chest images defining central-airway calibre and distal patency
- Prior bronchoscopy images, operative notes, stent model and pathology
- Oxygen, ventilation, arterial blood gas and pulmonary-function information
- Medication, anticoagulant, anaesthesia, dentition and cervical-spine history
- Recent pulmonology consultation and medication list
- Chest X-ray, CT chest or HRCT reports and image files where available
- Pulmonary function tests including spirometry and DLCO where performed
- Oxygen prescription, CPAP/BiPAP settings and recent admission summaries where relevant
Clinical detail
How the procedure is performed
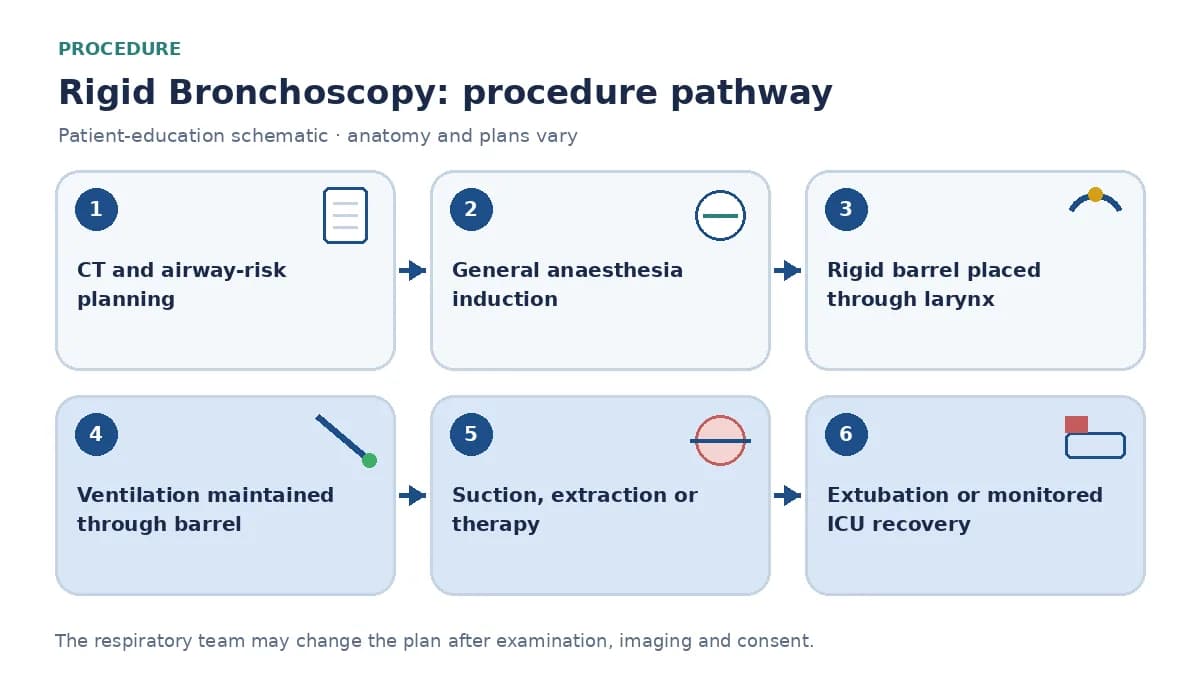
Under general anaesthesia the jaw, teeth and larynx are protected while the ventilating bronchoscope is advanced under direct vision through the vocal cords. Ventilation may be conventional, jet or another anaesthetist-directed mode. Telescopes and flexible scopes define anatomy; suction, forceps, balloons, stents or thermal and cryotherapy devices are used only as consented, followed by haemostasis and a distal-airway check.
The anaesthesia team continuously monitors oxygenation, ventilation, rhythm, pressure, temperature and airway pressures. Post-procedure care watches for laryngeal swelling, bronchospasm, bleeding, pneumothorax, airway perforation, residual obstruction and need for ventilation; some patients require high-dependency or ICU observation.
Main variations
- Rigid diagnostic and airway-control examination
- The barrel secures ventilation and suction while central anatomy is assessed, with flexible inspection or biopsy added if agreed.
- Foreign-body or clot extraction corridor
- Large optical forceps, baskets and suction remove an obstruction while limiting loss of the object into the opposite bronchus.
- Dilation and stent platform
- Mechanical or balloon dilation precedes placement, repositioning or removal of an airway stent, with sizing based on CT and bronchoscopy.
- Debulking and haemostasis platform
- Mechanical coring, electrocautery, argon plasma coagulation, laser or cryotherapy may restore central patency and control bleeding.
Preparation
Planning includes thin-section CT with airway diameter and obstruction length, distal-airway patency, vascular proximity, neck mobility and dentition, oxygen and ventilation status, blood count and coagulation, anticoagulants, cross-match when bleeding is plausible and formal anaesthesia review. Rescue plans may include ICU, thoracic surgery, embolization or extracorporeal support in exceptional high-risk obstruction.
Clinicians direct fasting, inhalers, anticoagulants, diabetes medicines, antibiotics and oxygen. Active infection or unstable breathing may postpone an elective procedure.
Hospital stay and recovery
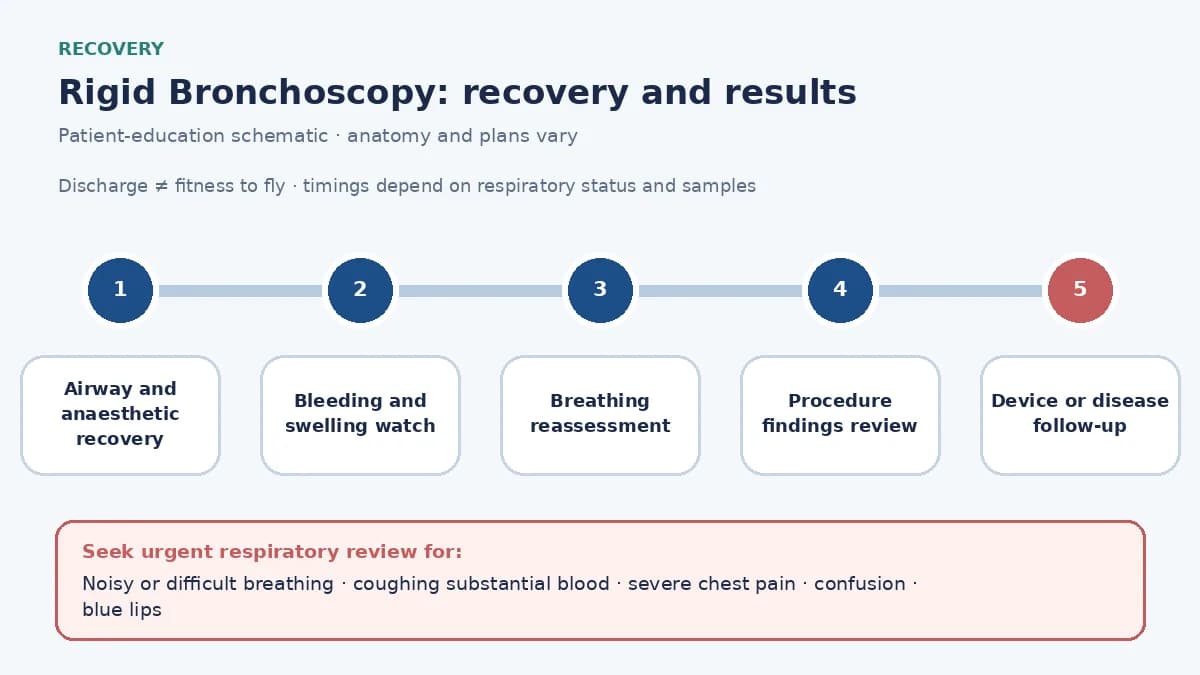
At least monitored recovery and often an overnight stay are used; severe obstruction, prolonged anaesthesia, bleeding, ventilation difficulty or major intervention can require ICU care. Throat or jaw soreness, hoarseness, cough and fatigue are expected possibilities after general anaesthesia. Breathing, voice, bleeding and chest imaging are reassessed as indicated. Return travel is deferred until the airway is stable, any device plan is documented and anaesthesia and pulmonology teams clear it.
Follow the oxygen, activity and equipment plan. Seek urgent respiratory help for new noisy breathing, rapidly worsening breathlessness, coughing substantial blood, severe chest pain, neck swelling, confusion or blue lips.
How to compare Rigid Bronchoscopy quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Who is the named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy, and at which campus?
- What clinical question will rigid bronchoscopy answer or treat?
- Is the scope diagnostic, therapeutic or both?
- Which approach is planned, and what might change it?
- Are pulmonologist, anaesthesia and procedure-suite fees included?
- Which imaging and respiratory tests are needed before the procedure?
- Which scopes, needles, probes, stents, valves, drains or catheters are assumed?
- Which cytology, histopathology and microbiology studies are included?
- Is molecular or biomarker testing included when tissue is obtained?
- How many day-care or ward nights are quoted?
- Are oxygen, non-invasive ventilation and ICU escalation covered?
- What is charged if another procedure or repeat sample is needed?
- How are pneumothorax, bleeding, ventilation and readmission billed?
- When will results be ready, and is the results consultation included?
- Which symptoms require urgent review and where?
- When may I work, exercise and fly?
- Who coordinates respiratory follow-up after I return home?
- Which rigid barrel, ventilation method and therapeutic tools are planned?
- Are stent, laser, APC, cryotherapy or extraction consumables included?
- What ICU, embolization and thoracic-surgery backup exists for airway loss or major bleeding?
- Does the estimate include planned surveillance or device removal?
Frequently asked questions
How much does Rigid Bronchoscopy cost in Chennai?
$1,200–$3,500 is the stored national planning range per theatre procedure. No verified Chennai-only tariff is stored; request an itemized quotation from a named campus.
Which Chennai clinician should assess me for rigid bronchoscopy?
A named interventional pulmonologist or thoracic surgeon trained in rigid bronchoscopy should review your records and imaging. Dynamic cards require an exact CMS relationship and are not rankings.
Where should I stay in Chennai after rigid bronchoscopy?
Use air-conditioned, flexible lodging near the respiratory campus with reliable electricity for any oxygen concentrator or PAP device. Some hospital corridors have direct airport access, but imaging, bronchoscopy, pathology and transplant follow-up may occur in different buildings. Confirm the complete pathway.
How much does Rigid Bronchoscopy cost in India?
Rigid Bronchoscopy is typically planned at $1,200–$3,500 per theatre procedure. This national range is not a quotation; technique, sedation, devices, pathology, ward nights and written terms determine the amount.
What is Rigid Bronchoscopy?
Rigid bronchoscopy places a straight, hollow metal ventilating barrel through the mouth and larynx into the trachea or main bronchi under general anaesthesia. Its wide lumen secures a central-airway corridor for high-volume suction, optical instruments, forceps, stents and bleeding-control or tumour-debulking tools.
When is rigid bronchoscopy considered?
Rigid bronchoscopy may be considered for critical central-airway obstruction, a large or sharp foreign body, major airway bleeding, silicone-stent placement or removal, mechanical tumour coring, dilation, or when a secure large-bore corridor is needed. CT anatomy, urgency, anaesthetic risk and availability of safer alternatives guide selection.
What does the rigid bronchoscopy planning range usually include?
It commonly includes the named respiratory specialist, procedure suite, routine monitoring, sedation or anaesthesia, standard consumables and quoted stay. Imaging, advanced devices, pathology panels and treatment after results may be separate.
What assessment is needed before rigid bronchoscopy?
Planning includes thin-section CT with airway diameter and obstruction length, distal-airway patency, vascular proximity, neck mobility and dentition, oxygen and ventilation status, blood count and coagulation, anticoagulants, cross-match when bleeding is plausible and formal anaesthesia review. Rescue plans may include ICU, thoracic surgery, embolization or extracorporeal support in exceptional high-risk obstruction.
How long does rigid bronchoscopy take?
Often 45 minutes to several hours, depending on obstruction complexity, ventilation, devices and bleeding control. Preparation and monitored recovery add time, and pathology or microbiology can extend the overall diagnostic journey.
Is hospitalization needed after rigid bronchoscopy?
At least monitored recovery and often an overnight stay are used; severe obstruction, prolonged anaesthesia, bleeding, ventilation difficulty or major intervention can require ICU care. Discharge follows respiratory and clinical criteria, not a package calendar.
What are the important risks of rigid bronchoscopy?
Risks include dental, lip or laryngeal injury, swelling, bronchospasm, low oxygen, high carbon dioxide, arrhythmia, anaesthetic complications, bleeding, airway tear or perforation, pneumothorax, infection and incomplete relief. Severe haemorrhage, airway loss, ventilation failure or need for emergency surgery are uncommon but central to consent.
When can an international patient fly after rigid bronchoscopy?
There is no universal flight day. Return travel is deferred until the airway is stable, any device plan is documented and anaesthesia and pulmonology teams clear it. The treating team must document travel fitness.
Is rigid bronchoscopy the same as flexible bronchoscopy?
No. It uses a straight metal ventilating tube under general anaesthesia for central-airway control and large tools; a flexible scope is often used through it for visualization.
Does rigid bronchoscopy always require ICU?
No. Some stable patients recover on a ward, while severe obstruction, bleeding, ventilation difficulty or prolonged intervention may require high-dependency or ICU care.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Airway Stenting cost in India
$2,000–$6,500 · stay 1–3 nights
Bronchoscopic Tumor Debulking cost in India
$2,000–$6,000 · stay 1–3 nights
Foreign Body Removal by Bronchoscopy cost in India
$800–$2,500 · stay Outpatient or 1 night
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 13 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Rigid Bronchoscopy cost sheet · All treatment costs in India · Pulmonology costs



