
Last updated: 12 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Gastric Sleeve Revision Surgery in Chennai is planned against $7,000–$14,000, with 3–7 nights stored only for broad trip planning. Neither token is a city tariff, admission promise or medical recommendation.
The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it. Inpatient monitoring follows the actual revision and may be longer because adhesiolysis, leak, bleeding and altered anatomy require close observation.
- India cost range
- $7,000–$14,000
- Typical starting point
- $7,000
- Typical hospital stay
- 3–7 nights
- Procedure time
- often longer than a primary sleeve, commonly two to five hours depending on adhesions and reconstruction
- Recovery
- Recovery depends on adhesiolysis and reconstruction rather than the old sleeve scar; travel waits for stable intake, wounds, bowel function and complication review.
Major cost factors: reason for revision, adhesions and prior staple-line anatomy, repair versus re-sleeve versus bypass, endoscopy and contrast assessment. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: unexpected extensive adhesiolysis or organ repair; different conversion after intraoperative findings; leak, fistula or bleeding treatment; extended admission or critical care; lifelong bypass supplements and monitoring.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
Gastric Sleeve Revision Surgery in Chennai
It may be considered only when symptoms, anatomy, nutrition and prior treatment identify a correctable problem and the expected trade-offs fit the individual's goals and follow-up capacity. Complete prior operative reports and stapling details, contrast imaging, endoscopy, reflux testing when indicated, nutrition laboratories, symptom and eating assessment and anaesthetic review are central.
Several hospital districts have comparatively direct airport access, but heat, humidity and travel after anaesthesia still require a planned vehicle, a companion and nearby recovery. Prior operative notes and imaging must be reviewed because adhesions and altered anatomy can change the plan after arrival.
Use air-conditioned, flexible accommodation near the named campus with safe water and dependable access to the prescribed high-protein liquids and soft foods. Heat can make hydration planning especially important. Fluid targets and electrolyte advice must come from the treating team rather than from a generic travel schedule.
Doctor and hospital cards in Chennai must resolve only from live catalog relationships that exactly tag Gastric Sleeve Revision Surgery. If that exact CMS entity relationship is absent, cards must remain empty; do not borrow a generic bariatric, surgical or endoscopy entity. This is a catalog gap, not a ranking, capability or outcome statement.
Send complete records before non-refundable travel. Remote acceptance can change after examination, repeat tests, endoscopy or imaging.
What gastric sleeve revision surgery typically costs in Chennai
The estimate can change with reason for revision, adhesions and prior staple-line anatomy, repair versus re-sleeve versus bypass, endoscopy and contrast assessment. These are clinical differences, not premium upgrades.
Ask the provider to identify the named Revisional bariatric surgeon, exact campus, anatomy, anaesthesia, devices or stapling, ward allowance, exclusions, emergency terms and follow-up.
Budget separately for travel through Chennai International Airport, use air-conditioned, flexible accommodation near the named campus with safe water and dependable access to the prescribed high-protein liquids and soft foods. Keep flights flexible until intake, mobility and fitness to travel are reviewed.
What moves the quote in Chennai
- Reason for revision
- Reflux, stenosis, fistula and anatomical dilation require different work.
- Adhesions and prior staple-line anatomy
- Operative reports and current imaging shape theatre time.
- Repair versus re-sleeve versus bypass
- These are materially different reconstructions.
- Endoscopy and contrast assessment
- Often essential before a reliable estimate.
Medical travel through Chennai
Send weight history, comorbidity records, prior treatment and relevant imaging or endoscopy before travel to Chennai.
Obtain written acceptance from a named Revisional bariatric surgeon. Prior operative notes and imaging must be reviewed because adhesions and altered anatomy can change the plan after arrival.
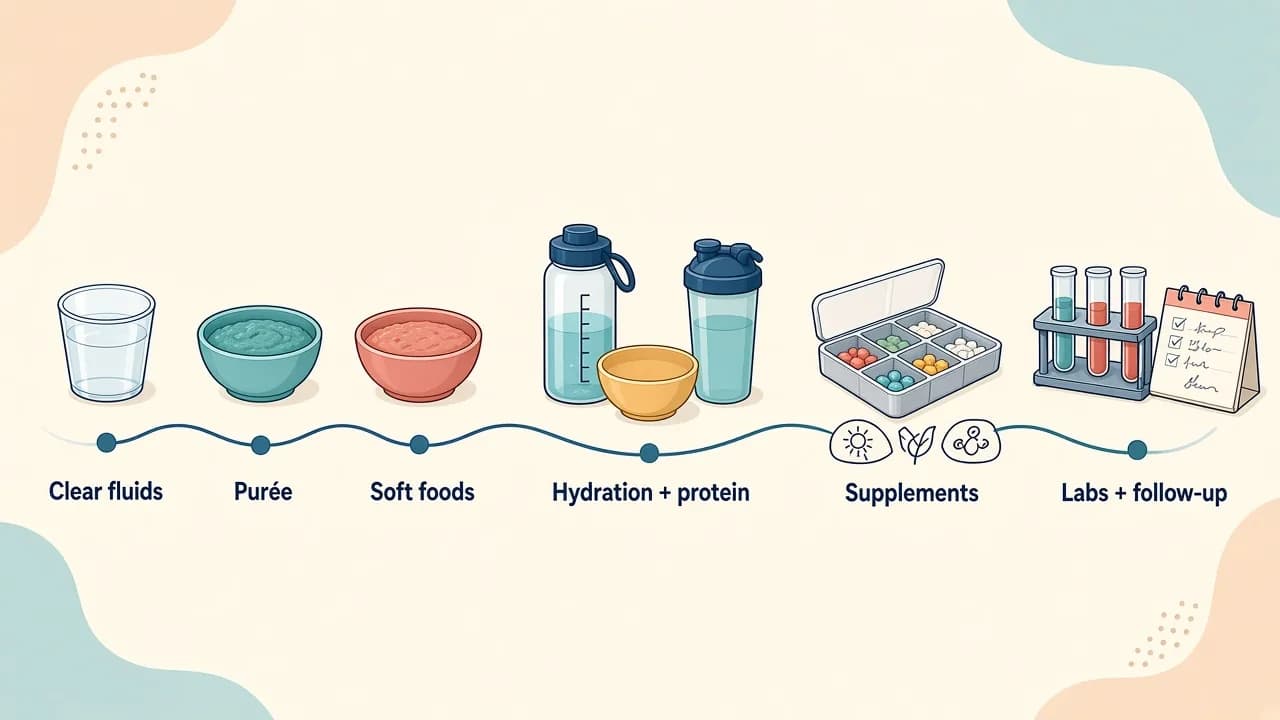
Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages. Heat can make hydration planning especially important. Fluid targets and electrolyte advice must come from the treating team rather than from a generic travel schedule. Travel home only after the team reviews oral intake, warning signs and follow-up access.
Hospitals and units listed in Chennai
Doctor and hospital cards in Chennai must resolve only from live catalog relationships that exactly tag Gastric Sleeve Revision Surgery. If that exact CMS entity relationship is absent, cards must remain empty; do not borrow a generic bariatric, surgical or endoscopy entity. This is a catalog gap, not a ranking, capability or outcome statement.
Confirm the exact campus, lead clinician, anaesthesia and emergency support, procedure-specific consumables, dietetic pathway and handover in writing. General accreditation does not establish current availability or results.
Gastric Sleeve Revision Surgery doctors in Chennai · Gastric Sleeve Revision Surgery hospitals in Chennai · Gastric Sleeve Revision Surgery cost in India
What Is Gastric Sleeve Revision Surgery?
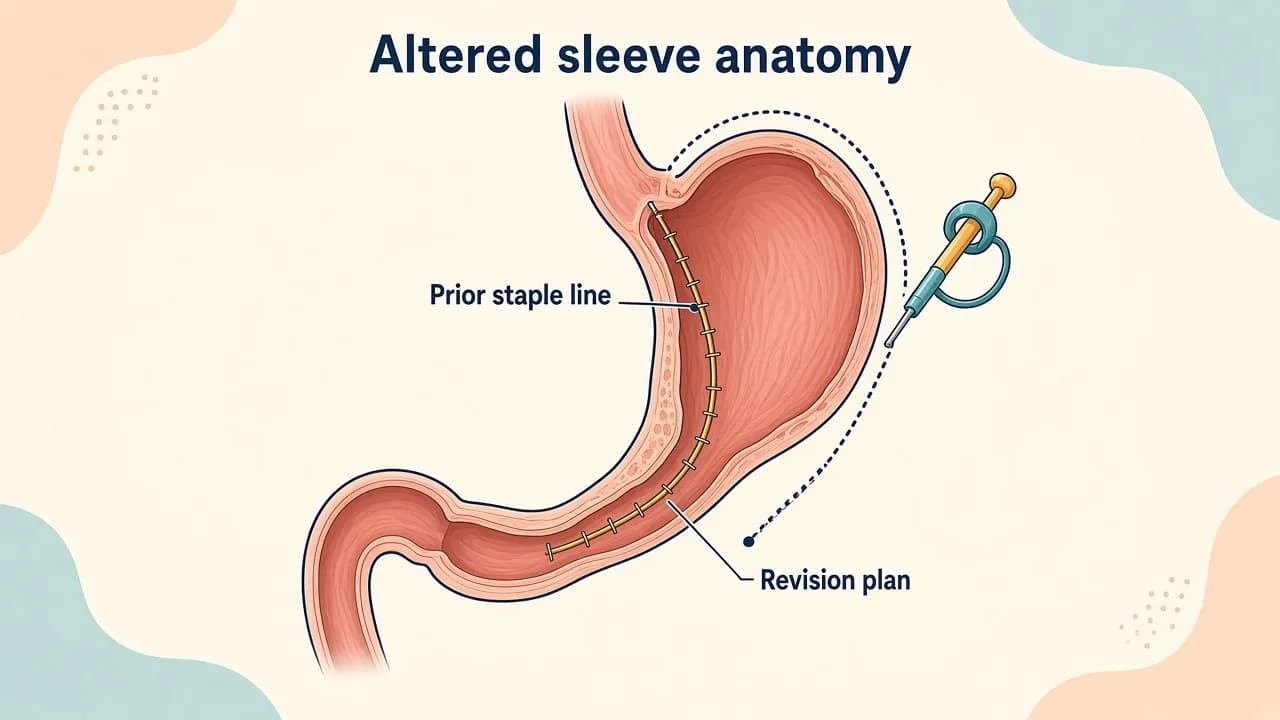
Gastric sleeve revision re-operates on a prior sleeve to address a defined problem such as severe reflux, stenosis, twisting, dilation, fistula or clinically important recurrence after reassessment.
The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it.
This is an altered-anatomy case. Adhesions, prior staple lines or implants and incomplete operative records can change access, risk, duration and whether conversion is appropriate.
When Is Gastric Sleeve Revision Surgery Considered?
It may be considered only when symptoms, anatomy, nutrition and prior treatment identify a correctable problem and the expected trade-offs fit the individual's goals and follow-up capacity.
Weight change alone does not select an operation or universal BMI cutoff. Unclear anatomy, untreated eating or medical drivers, active inflammation, major deficiency or unsafe operative risk may require investigation or non-surgical care first.
How treatment is given, monitored and adapted →
Gastric Sleeve Revision Surgery cost in India
The $7,000–$14,000 value is the national catalog planning range for gastric sleeve revision surgery. It applies only to the procedure and assumptions written in a provider letter; it is not a guaranteed package or tariff for any city or centre.
Important drivers include reason for revision, adhesions and prior staple-line anatomy, repair versus re-sleeve versus bypass, endoscopy and contrast assessment, leak or complication contingency. A changed device, reconstruction, admission or complication may describe a materially different episode.
Compare itemized estimates with the same clinical scope. Do not derive separate Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad prices from this national range, and keep travel, lodging, supplements and long-term monitoring visible.
Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages. Hydration and adequate protein need an individualized plan. Before travel, confirm written acceptance, quote scope, warning signs and follow-up at home.
Gastric Sleeve Revision Surgery cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a treatment estimate, not a dollar amount for each row.
- Revisional anatomy assessment
- Prior records, imaging, endoscopy and nutrition review as listed.
- Named revision procedure
- Repair, re-sleeve or conversion must be explicit.
- Adhesiolysis and stated consumables
- Only the anticipated scope and devices written.
- Quoted inpatient monitoring
- Defined ward or higher-acuity allowance.
- New diet and supplement plan
- Instructions matched to final anatomy and included follow-up.
Planning range or quotation?
The $7,000–$14,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Gastric Sleeve Revision Surgery package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a bariatric procedure estimate for this treatment. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Revisional anatomy assessment
Prior records, imaging, endoscopy and nutrition review as listed.
Usually included
Named revision procedure
Repair, re-sleeve or conversion must be explicit.
Usually included
Adhesiolysis and stated consumables
Only the anticipated scope and devices written.
Usually included
Quoted inpatient monitoring
Defined ward or higher-acuity allowance.
Usually included
New diet and supplement plan
Instructions matched to final anatomy and included follow-up.
May be charged separately
May be separate
Unexpected extensive adhesiolysis or organ repair
Additional work beyond documented assumptions.
May be separate
Different conversion after intraoperative findings
A changed reconstruction may alter the estimate.
May be separate
Leak, fistula or bleeding treatment
Imaging, stent, drainage, transfusion or reoperation.
May be separate
Extended admission or critical care
Care beyond stated limits.
May be separate
Lifelong bypass supplements and monitoring
Ongoing costs when final anatomy includes bypass.
Catalog inclusions listed for this pathway: bariatric consultation and records review; named surgeon on camera before travel; theatre, staplers or endoscopic kit, and overnight stay as quoted; dietetic plan and leak protocol as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this procedure, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Reason for revision
- Reflux, stenosis, fistula and anatomical dilation require different work.
- Adhesions and prior staple-line anatomy
- Operative reports and current imaging shape theatre time.
- Repair versus re-sleeve versus bypass
- These are materially different reconstructions.
- Endoscopy and contrast assessment
- Often essential before a reliable estimate.
- Leak or complication contingency
- Drainage, stenting or prolonged admission may be needed.
Approaches related to Gastric Sleeve Revision Surgery
The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it. The approaches below are clinical strategies, not consumer upgrades.
A named Revisional bariatric surgeon should explain why the proposed route fits the individual's anatomy and needs, and what finding could change or cancel it.
Swipe to compare treatment approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Conversion to Roux-en-Y bypass | Selected from anatomy, health, prior treatment and follow-up needs | No separate GAF sheetRelative complexity only | Commonly discussed for severe reflux or selected sleeve problems, with new bowel joins and lifelong bypass monitoring. |
| Targeted repair or endoscopic treatment | Selected from anatomy, health, prior treatment and follow-up needs | No separate GAF sheetRelative complexity only | Selected stenosis, fistula or leak-related problems may need dilation, stenting or repair rather than a new bariatric operation. |
| Re-sleeve in selected anatomy | Selected from anatomy, health, prior treatment and follow-up needs | No separate GAF sheetRelative complexity only | Requires evidence of a dilated segment and careful reflux and leak-risk discussion. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that procedure. Other rows describe relative clinical complexity and should not be read as prices.
Nutrition and follow-up after Gastric Sleeve Revision Surgery
Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages.
Hydration and protein require close attention. Supplements and lifelong laboratory monitoring follow the final anatomy, especially when revision creates an intestinal bypass.
The individual team sets fluid, protein, supplement and laboratory targets. Generic internet schedules should not replace instructions adapted to kidney, liver, diabetes or other medical needs.
Risks and recovery after Gastric Sleeve Revision Surgery
Revision-specific risks include injury during adhesiolysis, leak from a new or old staple line, bleeding, stricture, fistula, reflux persistence, bowel obstruction, nutritional deficiency and another intervention.
This is not an exhaustive consent list and assigns no probability. Risk depends on anatomy, prior treatment, current health and the actual technique.
Recovery depends on adhesiolysis and reconstruction rather than the old sleeve scar; travel waits for stable intake, wounds, bowel function and complication review. No article can promise a particular weight, metabolic response, symptom change or complication-free course.
Gastric Sleeve Revision Surgery cost: India vs other medical tourism destinations
India and United States values use stored GAF catalog ranges. Other rows are modelled relative private-care bands, not official tariffs, provider quotes or evidence of availability.
A meaningful comparison holds procedure, anatomy, device or stapling scope, admission, complication terms and long-term nutrition support constant.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $7,000–$14,000 | Baseline | GAF catalog planning range. The stored India value is a national planning band. Individual candidacy, anatomy, the exact procedure and follow-up obligations must be reviewed before an itemized estimate. |
| Turkey | $11,500–$19,000Indicative planning estimate* | ≈1.4× India | Private international-care market. Compare the exact procedure, devices or stapling, admission allowance, nutrition support, complication terms and follow-up rather than a headline package. |
| Thailand | $13,500–$23,000Indicative planning estimate* | ≈1.8× India | Private international hospitals. International coordination does not establish candidacy, procedure availability or continuity of dietetic and laboratory care after return. |
| United Arab Emirates | $23,000–$38,000Indicative planning estimate* | ≈2.9× India | Regional premium private care. Travel may be shorter for some families, while professional, facility, device, pharmacy and follow-up charges may remain separate. |
| Singapore | $29,500–$50,500Indicative planning estimate* | ≈3.8× India | High-cost specialist private care. Request an international self-pay estimate tied to the actual anatomy and procedure rather than a general weight-management package. |
| Germany | $26,500–$47,500Indicative planning estimate* | ≈3.5× India | European elective specialist care. Eligibility, professional billing, device scope and post-treatment nutritional follow-up vary and should be confirmed before travel. |
| United Kingdom | $23,000–$42,000Indicative planning estimate* | ≈3.1× India | Private self-pay for many visitors. Overseas patients should verify acceptance, quote boundaries, emergency access and who provides laboratory and dietetic care after discharge. |
| United States | $22,000–$45,000 | ≈3.2× India | Stored self-pay reference. Facility, specialist, anaesthesia, device and follow-up charges may be billed separately; $22,000–$45,000 is a comparison range, not one bundled quotation. |
*Figures other than India and the United States are modelled planning estimates scaled from the India catalog band, not hospital quotations. All values are planning information. Candidacy, anatomy, technique, devices, clinical course, complications, currency and length of stay can change the final amount; no row predicts availability or outcomes.
Why do international patients consider India for gastric sleeve revision surgery?
Some international patients evaluate India for access to a named Revisional bariatric surgeon and a national self-pay planning range below typical United States figures. Price alone is not a clinical reason to travel.
The relevant questions are individualized acceptance, exact procedure scope, anaesthesia and emergency arrangements, transparent follow-up, and whether nutrition and laboratory monitoring can continue after return.
No provider is ranked. Acute illness, uncontrolled medical or psychological risk, inability to maintain hydration or follow-up, or suitable established care near home may make travel inappropriate.
Centres for Gastric Sleeve Revision Surgery in Chennai
Cards must follow exact live entity relationships for Gastric Sleeve Revision Surgery. A general bariatric, surgery, endoscopy or accreditation label does not establish current case acceptance, emergency support, device scope, dietetic continuity or outcomes.
Campuses for this pathway are being confirmed. Ask the desk which houses currently quote it.
Gastric Sleeve Revision Surgery Revisional bariatric surgeons in Chennai
Profiles must be drawn dynamically only when Gastric Sleeve Revision Surgery appears in an exact current CMS procedure relationship. Missing mappings must leave cards empty. Verify the clinician's role, availability and campus; placement is not a ranking, volume, capability or outcome claim.
Named consultants for this pathway are being matched. Request a dossier and we will advise which campuses can quote it.
Gastric Sleeve Revision Surgery cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad retain $7,000–$14,000 because no verified city tariffs are stored. Their overlays address different airport, geography, climate, lodging, hydration and follow-up logistics without inventing local prices.
Doctor and hospital cards must resolve from live CMS entities that exactly carry the Gastric Sleeve Revision Surgery relationship. Missing exact mappings must leave cards empty. An empty card area is an explicit catalog gap, not a ranking, hidden recommendation, capability claim or evidence that care is unavailable.
Swipe to compare Indian cities →
Delhi NCR
$7,000–$14,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Delhi NCR-only tariff is stored for gastric sleeve revision surgery. Use $7,000–$14,000 as the national planning range until a named provider issues an itemized estimate; this is not a city price or guaranteed package.
2 hospitals · 5 doctors
Mumbai
$7,000–$14,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Mumbai-only tariff is stored for gastric sleeve revision surgery. Use $7,000–$14,000 as the national planning range until a named provider issues an itemized estimate; this is not a city price or guaranteed package.
1 hospital · 1 doctor
Bengaluru
$7,000–$14,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Bengaluru-only tariff is stored for gastric sleeve revision surgery. Use $7,000–$14,000 as the national planning range until a named provider issues an itemized estimate; this is not a city price or guaranteed package.
0 hospitals · consultant match on request
Chennai
$7,000–$14,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Chennai-only tariff is stored for gastric sleeve revision surgery. Use $7,000–$14,000 as the national planning range until a named provider issues an itemized estimate; this is not a city price or guaranteed package.
0 hospitals · consultant match on request
Hyderabad
$7,000–$14,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Hyderabad-only tariff is stored for gastric sleeve revision surgery. Use $7,000–$14,000 as the national planning range until a named provider issues an itemized estimate; this is not a city price or guaranteed package.
0 hospitals · consultant match on request
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for gastric sleeve revision surgery
What should international patients budget beyond the surgery?
A complete gastric sleeve revision surgery budget extends beyond $7,000–$14,000. Include remote review, tests outside the estimate, companion travel, nearby lodging, supplements, dietetic care, complication contingency and monitoring at home.
Travel follows written clinical acceptance and an itemized estimate. A visa invitation, directory profile or appointment is not medical clearance.
- Records and goals review
- Complete prior operative reports and stapling details, contrast imaging, endoscopy, reflux testing when indicated, nutrition laboratories, symptom and eating assessment and anaesthetic review are central.
- Individualized candidacy discussion
- It may be considered only when symptoms, anatomy, nutrition and prior treatment identify a correctable problem and the expected trade-offs fit the individual's goals and follow-up capacity. Weight change alone does not select an operation or universal BMI cutoff. Unclear anatomy, untreated eating or medical drivers, active inflammation, major deficiency or unsafe operative risk may require investigation or non-surgical care first.
- Procedure and alternative selection
- Discuss Conversion to Roux-en-Y bypass, Targeted repair or endoscopic treatment, Re-sleeve in selected anatomy, non-procedural care and what could alter the plan.
- Itemized estimate
- Match clinician, campus, technique, devices, anaesthesia, admission, nutrition, exclusions and complication terms.
- Arrival and reassessment
- Repeat examination, laboratory, imaging, endoscopy or anaesthetic assessment when clinically indicated before final consent.
- Treatment and monitored recovery
- The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it. Inpatient monitoring follows the actual revision and may be longer because adhesiolysis, leak, bleeding and altered anatomy require close observation.
- Diet progression and discharge
- Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages. Confirm medicines, warning signs and emergency contacts.
- Long-term handover
- Hydration and protein require close attention. Supplements and lifelong laboratory monitoring follow the final anatomy, especially when revision creates an intestinal bypass. Follow-up tracks the problem that prompted revision, the new anatomy, reflux, intake and deficiencies, with lifelong monitoring if conversion adds intestinal bypass.
- Treatment episode$7,000–$14,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay3–7 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for gastric sleeve revision surgery in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Assemble complete records
All prior sleeve operative notes and discharge summaries; Current endoscopy, contrast study and reflux testing; Weight trajectory, symptoms, nutrition and prior complication records.
Obtain specialist review
A named Revisional bariatric surgeon assesses indication, alternatives, anatomy and travel suitability.
Clarify goals and uncertainty
Discuss health goals, eating pattern, reflux or metabolic issues and what treatment cannot promise.
Confirm individualized candidacy
It may be considered only when symptoms, anatomy, nutrition and prior treatment identify a correctable problem and the expected trade-offs fit the individual's goals and follow-up capacity. Avoid using one universal BMI cutoff without the wider clinical assessment.
Compare itemized estimates
Use the same procedure assumptions and compare professional, facility, device, admission and follow-up scope.
Plan flexible travel
Arrange documents, refundable travel, a capable companion and suitable lodging near the exact campus.
Repeat assessment after arrival
Complete prior operative reports and stapling details, contrast imaging, endoscopy, reflux testing when indicated, nutrition laboratories, symptom and eating assessment and anaesthetic review are central.
Complete informed consent
Review alternatives, revision-specific risks include injury during adhesiolysis, leak from a new or old staple line, bleeding, stricture, fistula, reflux persistence, bowel obstruction, nutritional deficiency and another intervention. and the possibility that the plan changes.
Undergo the planned treatment
The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it.
Establish oral intake
Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages. Hydration and protein tolerance matter before discharge.
Complete nearby review
Review symptoms, intake, medicines and travel fitness; recovery depends on adhesiolysis and reconstruction rather than the old sleeve scar; travel waits for stable intake, wounds, bowel function and complication review.
Transfer care home
Follow-up tracks the problem that prompted revision, the new anatomy, reflux, intake and deficiencies, with lifelong monitoring if conversion adds intestinal bypass. Carry the procedure report, discharge summary, diet plan and laboratory schedule.
Documents to prepare
- All prior sleeve operative notes and discharge summaries
- Current endoscopy, contrast study and reflux testing
- Weight trajectory, symptoms, nutrition and prior complication records
- Current medicines, allergies and recent laboratory results
- Weight trajectory, prior structured weight-management treatment and relevant dietetic notes
- Diabetes, sleep-apnoea, cardiovascular, liver, kidney and reflux records where applicable
- Passport and companion documentation needed for travel and consent
Clinical detail
How the procedure is performed
The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it.
The procedural forms discussed here include Conversion to Roux-en-Y bypass, Targeted repair or endoscopic treatment, Re-sleeve in selected anatomy; they are not interchangeable package labels.
Inpatient monitoring follows the actual revision and may be longer because adhesiolysis, leak, bleeding and altered anatomy require close observation. often longer than a primary sleeve, commonly two to five hours depending on adhesions and reconstruction.

Main variations
- Conversion to Roux-en-Y bypass
- Commonly discussed for severe reflux or selected sleeve problems, with new bowel joins and lifelong bypass monitoring.
- Targeted repair or endoscopic treatment
- Selected stenosis, fistula or leak-related problems may need dilation, stenting or repair rather than a new bariatric operation.
- Re-sleeve in selected anatomy
- Requires evidence of a dilated segment and careful reflux and leak-risk discussion.
Preparation
Complete prior operative reports and stapling details, contrast imaging, endoscopy, reflux testing when indicated, nutrition laboratories, symptom and eating assessment and anaesthetic review are central.
The receiving team should reconcile medicines, screen for tobacco, alcohol or substance risks, assess eating behaviour and mental health without stigma, and discuss contraception or pregnancy timing where relevant.
Follow the treating team's fasting and diabetes-medicine instructions. Report fever, new abdominal symptoms, uncontrolled glucose or another material health change before travel or treatment.
Hospital stay and recovery
Inpatient monitoring follows the actual revision and may be longer because adhesiolysis, leak, bleeding and altered anatomy require close observation. Recovery depends on adhesiolysis and reconstruction rather than the old sleeve scar; travel waits for stable intake, wounds, bowel function and complication review.
Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages. Small frequent sips, the prescribed protein plan and avoidance of dehydration are early priorities; inability to keep fluids down needs prompt advice.
Hydration and protein require close attention. Supplements and lifelong laboratory monitoring follow the final anatomy, especially when revision creates an intestinal bypass. Follow-up must not end with the return flight.
Revision-specific risks include injury during adhesiolysis, leak from a new or old staple line, bleeding, stricture, fistula, reflux persistence, bowel obstruction, nutritional deficiency and another intervention.
Follow-up tracks the problem that prompted revision, the new anatomy, reflux, intake and deficiencies, with lifelong monitoring if conversion adds intestinal bypass. Seek urgent clinical help for fever, rapid pulse, increasing abdominal or shoulder pain, repeated vomiting, black stools, breathing difficulty, wound drainage or inability to drink; use the treating team's own emergency thresholds.
How to compare Gastric Sleeve Revision Surgery quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is gastric sleeve revision surgery being considered now, and what non-procedural alternatives were discussed?
- How were my health goals, weight history, eating pattern and prior treatment considered?
- Which findings support candidacy, and what could postpone or cancel treatment?
- Who is the named Revisional bariatric surgeon, and at which exact campus will care occur?
- Does the quotation use the exact name Gastric Sleeve Revision Surgery?
- Which consultations, laboratory tests, imaging and endoscopy are included?
- Which anaesthesia assessment and anaesthesia fees are included?
- Which staplers, sutures, implants, balloons or other consumables are assumed?
- What change in anatomy could alter the procedure after arrival?
- How many ward or observation nights and which room category are included?
- How are extra nights, high-dependency care, readmission or another procedure billed?
- Which medicines, clot prevention and discharge prescriptions are included?
- What leak, bleeding or other complication assessment is planned when clinically indicated?
- What liquid, puréed, soft and regular-texture diet progression will I receive?
- Who sets my hydration and protein plan, and how is poor intake managed?
- Which vitamins, minerals or other supplements are recommended for my actual procedure?
- Which dietetic and clinical follow-up visits are included?
- Which lifelong laboratory monitoring is relevant, and who will arrange it at home?
- What symptoms require urgent local care or return to the treating centre?
- When and by whom will fitness to fly be assessed?
- What records and emergency contacts will I receive before departure?
- Who will coordinate care with my clinician and dietitian after I return home?
- Which prior operative details are still missing before the quote is reliable?
- Is the plan repair, re-sleeve or conversion to bypass, and what finding could change it?
- How are adhesiolysis and unexpected staple-line findings billed?
- What leak-management resources and follow-up are included?
Frequently asked questions
How much does gastric sleeve revision surgery cost in Chennai?
Use $7,000–$14,000 as the stored national planning range. No verified Chennai-only tariff is stored; the final amount follows record review and an itemized estimate.
Which Chennai clinician should assess gastric sleeve revision surgery?
A named Revisional bariatric surgeon should assess the case. Cards appear only for exact live CMS relationships; placement is not a ranking or experience claim.
Where should the patient stay in Chennai?
Use air-conditioned, flexible accommodation near the named campus with safe water and dependable access to the prescribed high-protein liquids and soft foods. Several hospital districts have comparatively direct airport access, but heat, humidity and travel after anaesthesia still require a planned vehicle, a companion and nearby recovery.
When can the patient fly home?
There is no universal date. Recovery depends on adhesiolysis and reconstruction rather than the old sleeve scar; travel waits for stable intake, wounds, bowel function and complication review. The treating team must review intake, mobility, complications and clot risk.
What should the written estimate identify?
It should name Gastric Sleeve Revision Surgery, the clinician and campus, procedural assumptions, included devices or stapling, admission, exclusions, complication terms and follow-up.
How much does gastric sleeve revision surgery cost in India?
Gastric Sleeve Revision Surgery is typically planned at $7,000–$14,000. This national stored range is not a quotation; anatomy, technique, admission and written terms determine the final amount.
What is gastric sleeve revision surgery?
Gastric sleeve revision re-operates on a prior sleeve to address a defined problem such as severe reflux, stenosis, twisting, dilation, fistula or clinically important recurrence after reassessment.
When is gastric sleeve revision surgery considered?
It may be considered only when symptoms, anatomy, nutrition and prior treatment identify a correctable problem and the expected trade-offs fit the individual's goals and follow-up capacity.
Is there one BMI threshold for every patient?
Weight change alone does not select an operation or universal BMI cutoff. Unclear anatomy, untreated eating or medical drivers, active inflammation, major deficiency or unsafe operative risk may require investigation or non-surgical care first.
What assessment is needed before treatment?
Complete prior operative reports and stapling details, contrast imaging, endoscopy, reflux testing when indicated, nutrition laboratories, symptom and eating assessment and anaesthetic review are central.
What happens during the procedure?
The surgeon enters an adhesed upper abdomen, defines the prior staple line and hiatus, then performs the planned repair, re-sleeve or conversion—often to Roux-en-Y—only if current findings support it. This is an altered-anatomy case. Adhesions, prior staple lines or implants and incomplete operative records can change access, risk, duration and whether conversion is appropriate.
How long does gastric sleeve revision surgery take?
often longer than a primary sleeve, commonly two to five hours depending on adhesions and reconstruction. Actual timing depends on anatomy and the clinical course.
What diet follows treatment?
Diet restarts with liquids and progresses according to the new repair or reconstruction; prior tolerance does not justify skipping stages.
How important are hydration and protein?
Hydration and protein require close attention. Supplements and lifelong laboratory monitoring follow the final anatomy, especially when revision creates an intestinal bypass. The treating team individualizes targets and advises on intolerance.
What are the important risks?
Revision-specific risks include injury during adhesiolysis, leak from a new or old staple line, bleeding, stricture, fistula, reflux persistence, bowel obstruction, nutritional deficiency and another intervention.
When can an international patient fly home?
There is no fixed flight day. Recovery depends on adhesiolysis and reconstruction rather than the old sleeve scar; travel waits for stable intake, wounds, bowel function and complication review. The treating team must document travel fitness.
What long-term follow-up is needed?
Follow-up tracks the problem that prompted revision, the new anatomy, reflux, intake and deficiencies, with lifelong monitoring if conversion adds intestinal bypass. Hydration and protein require close attention. Supplements and lifelong laboratory monitoring follow the final anatomy, especially when revision creates an intestinal bypass.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Sleeve Gastrectomy cost in India
$4,500–$8,500 · stay 2–5 nights
Gastric Bypass (Roux-en-Y) cost in India
$6,000–$11,000 · stay 3–6 nights
Endoscopic Sleeve Gastroplasty (ESG) cost in India
$4,500–$9,000 · stay 1–3 nights
Gastric Band Removal cost in India
$2,200–$5,500 · stay 1–3 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 12 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Gastric Sleeve Revision Surgery cost sheet · All treatment costs in India · Bariatric Surgery costs



