
Last updated: 12 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
ERCP in India is typically planned at $1,500–$4,200. The cost may cover the named specialist, endoscopy or procedure-room time, stated imaging, routine medicines and the listed hospital stay, while extra stents, clips, pathology or another procedure depend on the written scope. The stored stay is Day-care to 2 nights, but monitoring and travel timing are individualized.
Major price drivers are bile-duct versus pancreatic-duct work, stone burden and lithotripsy, stent type, altered anatomy or prior ercp. Emergency treatment, a therapeutic add-on or a different device can materially change the bill.
- India cost range
- $1,500–$4,200
- Typical starting point
- $1,500
- Typical hospital stay
- Day-care to 2 nights
- Procedure time
- Often 30–90 minutes depending on anatomy and interventions
- Recovery
- Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice.
Major cost factors: bile-duct versus pancreatic-duct work, stone burden and lithotripsy, stent type, altered anatomy or prior ercp. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed scope; complications; premium devices; extended aftercare; travel and living.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
ERCP combines endoscopy and X-ray imaging to diagnose and treat selected problems involving the bile ducts and pancreatic duct, including certain stones and blockages. It may be considered when imaging suggests bile-duct stones, a stricture, a leak or selected pancreatic-duct disease and a clinician judges that endoscopic access is appropriate.
Assessment includes liver tests, ultrasound, MRCP or CT, coagulation, and whether sphincterotomy, stone extraction or stenting is already expected. ERCP is not a first-line look at the stomach or colon. Diagnostic-only ERCP is uncommon once MRCP or EUS can answer the question. It is not a substitute for surgery when anatomy cannot be reached.
Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated. Selection among Therapeutic ERCP for stones, ERCP with biliary stenting, Pancreatic-duct ERCP depends on anatomy, disease extent and the treating team's assessment, not on a package label.
The catalog supplies $1,500–$4,200 for India, $8,000–$22,000 for a United States self-pay reference and Day-care to 2 nights for broad planning. These values are not city tariffs, medical acceptance, outcome forecasts or final bills.
What Is ERCP?
ERCP combines endoscopy and X-ray imaging to diagnose and treat selected problems involving the bile ducts and pancreatic duct, including certain stones and blockages.
Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated.
ERCP is not a first-line look at the stomach or colon. Diagnostic-only ERCP is uncommon once MRCP or EUS can answer the question. It is not a substitute for surgery when anatomy cannot be reached.
When Is ERCP Considered?
It may be considered when imaging suggests bile-duct stones, a stricture, a leak or selected pancreatic-duct disease and a clinician judges that endoscopic access is appropriate.
Suitability depends on individual assessment by a qualified gastroenterologist and, where relevant, hepatology, interventional radiology or a multidisciplinary team. This page cannot diagnose a reader or recommend a personal procedure.
How the procedure is performed, recovery and variations →
ERCP cost in India
The $1,500–$4,200 value is GAF's stored national planning range for ERCP. It should be replaced by an itemized quotation tied to a named interventional gastroenterologist or pancreaticobiliary endoscopist, campus, diagnostic versus therapeutic plan and monitoring assumption.
Cost can change with bile-duct versus pancreatic-duct work, stone burden and lithotripsy, stent type, altered anatomy or prior ercp, observation and pancreatitis care. A different stent, extra polyp or a combined procedure describes a different episode.
Compare estimates line by line. Do not derive separate Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad prices from this national range, and keep flights, lodging, companion costs, long-term medicines and nutrition support visible.
Planning Range ≠ Final Hospital Quotation. A qualified gastroenterology team must review records, anatomy and alternatives before an itemized offer is meaningful.
ERCP cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a gastroenterology procedure estimate, not a dollar amount for each row.
- Clinical assessment
- Named gastroenterology consultation, records review and procedure-focused examination when explicitly listed.
- Procedure episode
- Specialist, endoscopy or procedure-room time, standard equipment and recovery-room care within the written scope.
- Imaging and tests
- Stated blood tests and listed ultrasound, CT, MRI, MRCP or endoscopy only; unlisted advanced imaging is extra.
- Routine aftercare
- Standard medicines, observation and stated early follow-up only when itemized.
- Documentation
- Discharge summary, procedure report and pathology or device details where applicable.
- Listed ductal intervention
- Only the stated cannulation and named therapy.
Planning range or quotation?
The $1,500–$4,200 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a ERCP package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a gastroenterology estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Clinical assessment
Named gastroenterology consultation, records review and procedure-focused examination when explicitly listed.
Usually included
Procedure episode
Specialist, endoscopy or procedure-room time, standard equipment and recovery-room care within the written scope.
Usually included
Imaging and tests
Stated blood tests and listed ultrasound, CT, MRI, MRCP or endoscopy only; unlisted advanced imaging is extra.
Usually included
Routine aftercare
Standard medicines, observation and stated early follow-up only when itemized.
Usually included
Documentation
Discharge summary, procedure report and pathology or device details where applicable.
Usually included
Listed ductal intervention
Only the stated cannulation and named therapy.
May be charged separately
May be separate
Changed scope
An additional polyp, stone, stent, biopsy series or a different procedure found after arrival.
May be separate
Complications
Unplanned tests, emergency treatment, repeat endoscopy, prolonged stay or readmission unless expressly covered.
May be separate
Premium devices
A different stent, clip, balloon, suturing system or drainage device from the one written in the estimate.
May be separate
Extended aftercare
Long-term medicines, nutrition support, remote review or follow-up beyond the included period.
May be separate
Travel and living
Flights, visa, local transport, lodging, meals, companion costs and personal expenses.
Catalog inclusions listed for this pathway: gastroenterology consultation and records review; named consultant on camera before travel; endoscopy suite, sedation or anaesthesia, and overnight stay as quoted; histology, stent or drain follow-up as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this procedure, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Bile-duct versus pancreatic-duct work
- Different risk and device profiles.
- Stone burden and lithotripsy
- Large or multiple stones take more time.
- Stent type
- Plastic versus metal should be named.
- Altered anatomy or prior ERCP
- Revision or Roux anatomy is a different sitting.
- Observation and pancreatitis care
- Extra nights are often outside a day-care quote.
Approaches to ERCP
Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated. The options below are clinical strategies, not consumer upgrades.
A named interventional gastroenterologist or pancreaticobiliary endoscopist should explain which route fits the individual's anatomy and condition, and what finding could change or cancel it.
Swipe to compare procedural approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Therapeutic ERCP for stones | Selected from anatomy, diagnosis, risk and follow-up needs | No separate GAF sheetRelative complexity only | Sphincterotomy and extraction when choledocholithiasis is the indication. |
| ERCP with biliary stenting | Selected from anatomy, diagnosis, risk and follow-up needs | No separate GAF sheetRelative complexity only | Plastic or metal stents for obstruction; the stent itself may be a separate line. |
| Pancreatic-duct ERCP | Selected from anatomy, diagnosis, risk and follow-up needs | No separate GAF sheetRelative complexity only | Selected leaks or strictures; pancreatitis risk and device choice differ from biliary work. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that procedure. Other rows describe relative clinical complexity and should not be read as prices.
What ERCP can and cannot address
ERCP is not a first-line look at the stomach or colon. Diagnostic-only ERCP is uncommon once MRCP or EUS can answer the question. It is not a substitute for surgery when anatomy cannot be reached.
A consultation should separate the intended target — oesophagus, stomach, small bowel, colon, bile duct, pancreas, liver or another named structure — from other GI disease that may still need medicines, surgery or another endoscopic procedure.
No page can promise complete diagnosis, cure, weight change, stone clearance or a complication-free course.
Risks and Considerations after ERCP
Risks include pancreatitis, bleeding, infection or cholangitis, perforation, stent blockage or migration, failed cannulation and need for PTBD or surgery.
This is not an exhaustive consent list and assigns no probability. Risk depends on anatomy, prior endoscopy, anticoagulation, infection, emergency versus planned timing and the actual technique.
Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice. A lower price does not reduce the need for emergency access or structured follow-up.
Recovery and travel after ERCP
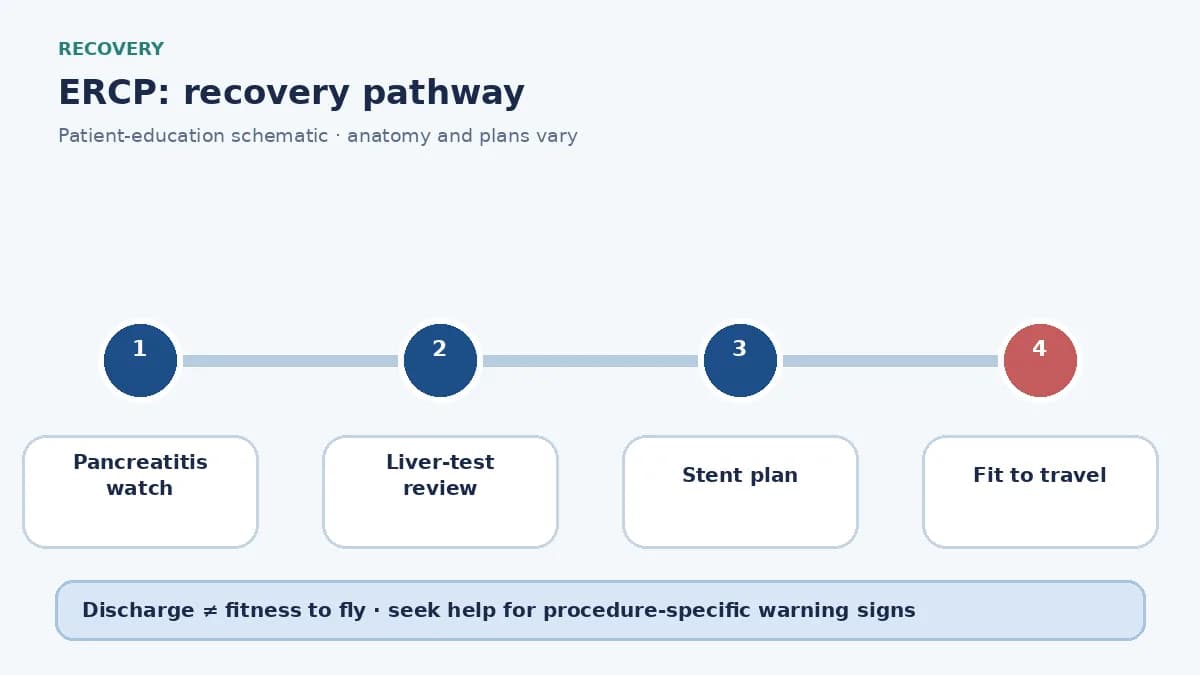
Day-care to 2 nights is stored; pancreatitis, cholangitis or incomplete drainage can extend stay. Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice.
International patients should distinguish procedure time, hospital stay, recommended days in India and longer-term recovery at home. Discharge is not the same as fitness to fly.
Follow-up reviews symptoms, liver tests, stent plan and whether another ERCP or PTBD is needed. Flights should remain flexible until the team confirms diet, bleeding risk, device stability and travel fitness.
ERCP cost: India vs other medical tourism destinations
India and United States values use stored GAF catalog ranges. Other countries require quotations because comparable, procedure-specific packages are not reliably available in the catalog.
A meaningful comparison holds clinician, licensed facility, diagnostic versus therapeutic scope, devices, imaging, monitoring, complication terms and follow-up constant.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $1,500–$4,200 | Baseline | GAF catalog planning range. The stored India figure is a national planning range. It does not establish candidacy, therapeutic add-ons, stent choice, observation nights or a final quotation. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Compare the exact GI procedure, diagnostic versus therapeutic work, stent or device, sedation, emergency backup and follow-up rather than a headline package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Depends on procedure and hospital. International coordination does not establish advanced-endoscopy capability, pathology turnaround or continuity after return. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Professional, facility, device, imaging, pharmacy and follow-up charges may be billed separately. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Request a self-pay estimate tied to the actual lesion, duct anatomy and observation plan rather than a general endoscopy package. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Eligibility, professional billing, device scope and post-travel GI follow-up require direct confirmation. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, quote boundaries, emergency access and who reviews pathology or a stent after return. |
| United States | $8,000–$22,000 | ≈5.3× India | Stored self-pay reference. Facility, specialist, device, imaging and follow-up charges may be billed separately; $8,000–$22,000 is a comparison range, not a bundled quotation. |
International comparisons are indicative and may not represent identical packages. Anatomy, devices, emergency timing, complications, currency and length of stay can change the final amount.
Why do international patients consider India for ERCP?
Some international patients evaluate India for access to a named interventional gastroenterologist or pancreaticobiliary endoscopist, hospital endoscopy units and a national self-pay planning range below the stored United States reference. Price alone is not a clinical reason to travel.
The relevant questions are individualized acceptance, licensed facility, emergency bleeding or pancreatitis backup, device traceability where relevant and continuity after return.
No provider is ranked and no outcome is promised. Unstable GI bleeding, untreated jaundice, inadequate records or safer established care near home may make travel inappropriate.
Hospitals and gastroenterology centres for ERCP in India
Cards follow exact live entity relationships for ERCP. A general gastroenterology or accreditation label does not establish current case acceptance, device stock, emergency backup or outcomes.
Indraprastha Apollo Hospital
 JCI Accredited
 NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
19 listed doctors for this pathway
Languages listed: English, Hindi
Apollo Hospital, Jubilee Hills, Hyderabad
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
3 listed doctors for this pathway
Languages listed: English, Telugu, Hindi
Apollo Hospitals, Bannerghatta Road
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
6 listed doctors for this pathway
Languages listed: English, Kannada, Hindi
Apollo Hospitals, Navi Mumbai
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
4 listed doctors for this pathway
Languages listed: English, Hindi, Marathi
Artemis Hospital
- JCI Accredited
- NABH Accredited
- DHADHA
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
7 listed doctors for this pathway
Languages listed: English, Hindi
BLK-Max Super Speciality Hospital
- JCI Accredited
- NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
5 listed doctors for this pathway
Languages listed: English, Hindi
Fortis Memorial Research Institute
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
5 listed doctors for this pathway
Languages listed: English, Hindi
Fortis Hospital, Noida
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
4 listed doctors for this pathway
Languages listed: English, Hindi
ERCP hospitals in India · Talk to a treatment coordinator
ERCP specialists in India
Profiles are drawn dynamically only when ERCP appears in an exact current CMS procedure relationship. Verify specialty scope, availability and campus; placement is not a ranking, volume or outcome claim.

Dr. Ajay Kumar
Gastroenterology
38+ years Experience
Upper GI Endoscopy (Gastroscopy) · Colonoscopy · ERCP
English, Hindi
Dr. Adi Rakesh Kumar
Gastroenterology
23+ years Experience
ERCP · Biliary Strictures · Chronic Pancreatitis
English, Telugu, Hindi
Dr. Ameet Mandot
Gastroenterology
24+ years Experience
Liver Cirrhosis · Chronic Liver Disease · Non-Alcoholic Fatty Liver Disease
English, Hindi, Marathi
Dr. D. Babu Vinish
Gastroenterology
20+ years Experience
Inflammatory Bowel Disease (IBD) · Crohn's Disease Management · Ulcerative Colitis Management
English, Tamil, Hindi
Dr. Dinesh Kini K
Gastroenterology
35+ years Experience
Upper GI Endoscopy (Gastroscopy) · Colonoscopy · ERCP
English, Kannada, Hindi
Dr. Amarender Singh Puri
Gastroenterology
34+ years Experience
Upper GI Endoscopy (Gastroscopy) · Colonoscopy · ERCP
English, Hindi
Dr. Anilkumar Mannava
Gastroenterology
16+ years Experience
ERCP · Biliary Strictures · Chronic Pancreatitis
English, Telugu, Hindi
Dr. Amit Gharat
Gastroenterology
18+ years Experience
Upper GI Endoscopy (Gastroscopy) · Colonoscopy · ERCP
English, Hindi, Marathi
ERCP doctors in India (152 listed) · Get a personalized cost estimate
ERCP cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad retain $1,500–$4,200 because no verified city tariffs are stored. Their pages address distinct airport, geography, climate, lodging and follow-up logistics without inventing local prices.
Doctor and hospital cards resolve only from CMS entities carrying the exact ERCP relationship. Missing mappings leave cards empty rather than borrowing generic gastroenterology entities.
Swipe to compare Indian cities →
Delhi NCR
$1,500–$4,200
India planning band — not a city quote
Typical stay Day-care to 2 nights
No verified Delhi NCR-only tariff is stored for ERCP. Use $1,500–$4,200 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
14 hospitals · 88 doctors
Mumbai
$1,500–$4,200
India planning band — not a city quote
Typical stay Day-care to 2 nights
No verified Mumbai-only tariff is stored for ERCP. Use $1,500–$4,200 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
5 hospitals · 17 doctors
Bengaluru
$1,500–$4,200
India planning band — not a city quote
Typical stay Day-care to 2 nights
No verified Bengaluru-only tariff is stored for ERCP. Use $1,500–$4,200 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
3 hospitals · 8 doctors
Chennai
$1,500–$4,200
India planning band — not a city quote
Typical stay Day-care to 2 nights
No verified Chennai-only tariff is stored for ERCP. Use $1,500–$4,200 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
3 hospitals · 10 doctors
Hyderabad
$1,500–$4,200
India planning band — not a city quote
Typical stay Day-care to 2 nights
No verified Hyderabad-only tariff is stored for ERCP. Use $1,500–$4,200 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
5 hospitals · 29 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for ERCP
What should international patients budget beyond the gastroenterology procedure?
A complete ERCP trip budget extends beyond $1,500–$4,200. Include remote review, tests outside the estimate, companion travel, nearby lodging, medicines, nutrition support and a complication contingency.
Travel should follow written clinical acceptance and an itemized estimate. A visa invitation or directory profile is not medical clearance.
- Records review
- Assessment includes liver tests, ultrasound, MRCP or CT, coagulation, and whether sphincterotomy, stone extraction or stenting is already expected.
- Specialist assessment
- It may be considered when imaging suggests bile-duct stones, a stricture, a leak or selected pancreatic-duct disease and a clinician judges that endoscopic access is appropriate. ERCP is not a first-line look at the stomach or colon. Diagnostic-only ERCP is uncommon once MRCP or EUS can answer the question. It is not a substitute for surgery when anatomy cannot be reached.
- Procedure and alternatives
- Discuss Therapeutic ERCP for stones, ERCP with biliary stenting, Pancreatic-duct ERCP, medicines and what could alter the plan.
- Itemized estimate
- Match clinician, campus, diagnostic versus therapeutic scope, devices, imaging, monitoring, exclusions and emergency terms.
- Arrival reassessment
- Repeat examination, blood tests, imaging or endoscopy only when clinically indicated before final consent.
- Procedure and monitored recovery
- Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated. Day-care to 2 nights is stored; pancreatitis, cholangitis or incomplete drainage can extend stay.
- Discharge and nearby review
- Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice. Confirm medicines, warning signs and emergency contacts.
- Handover home
- Follow-up reviews symptoms, liver tests, stent plan and whether another ERCP or PTBD is needed. Carry the procedure report, pathology and device details where relevant.
- Treatment episode$1,500–$4,200
- Pre-operative testsOften inside the estimate — confirm
- Hospital stayDay-care to 2 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for ERCP in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Submit relevant records
MRCP, CT or ultrasound; Liver-function tests; Prior ERCP reports; Stent cards if previously placed.
Obtain specialist review
A named interventional gastroenterologist or pancreaticobiliary endoscopist assesses indication, anatomy, alternatives and travel suitability.
Clarify goals and uncertainty
Discuss symptoms, prior treatment and what this procedure cannot promise.
Confirm individualized candidacy
It may be considered when imaging suggests bile-duct stones, a stricture, a leak or selected pancreatic-duct disease and a clinician judges that endoscopic access is appropriate.
Compare itemized estimates
Hold procedure, device, imaging, monitoring and emergency terms constant.
Plan flexible travel
Arrange documents, refundable travel, a capable companion and lodging near the exact campus.
Repeat assessment after arrival
Assessment includes liver tests, ultrasound, MRCP or CT, coagulation, and whether sphincterotomy, stone extraction or stenting is already expected.
Complete informed consent
Review alternatives, risks include pancreatitis, bleeding, infection or cholangitis, perforation, stent blockage or migration, failed cannulation and need for ptbd or surgery. and the possibility that the plan changes.
Undergo the planned procedure
Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated.
Complete monitored recovery
Day-care to 2 nights is stored; pancreatitis, cholangitis or incomplete drainage can extend stay. Establish safe oral intake, symptom control and device or diet instructions.
Attend nearby follow-up
Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice. Obtain explicit fitness-to-fly advice.
Transfer care home
Follow-up reviews symptoms, liver tests, stent plan and whether another ERCP or PTBD is needed. Share the report and emergency plan with the local clinician.
Documents to prepare
- MRCP, CT or ultrasound
- Liver-function tests
- Prior ERCP reports
- Stent cards if previously placed
- Current medicines, allergies and recent blood tests where relevant
- Gastroenterology notes and any available endoscopy, colonoscopy, ERCP, CT, MRI, MRCP or ultrasound reports
- Previous GI procedure notes, pathology and stent or device records
- Passport and companion information needed for travel and consent
Clinical detail
How the procedure is performed
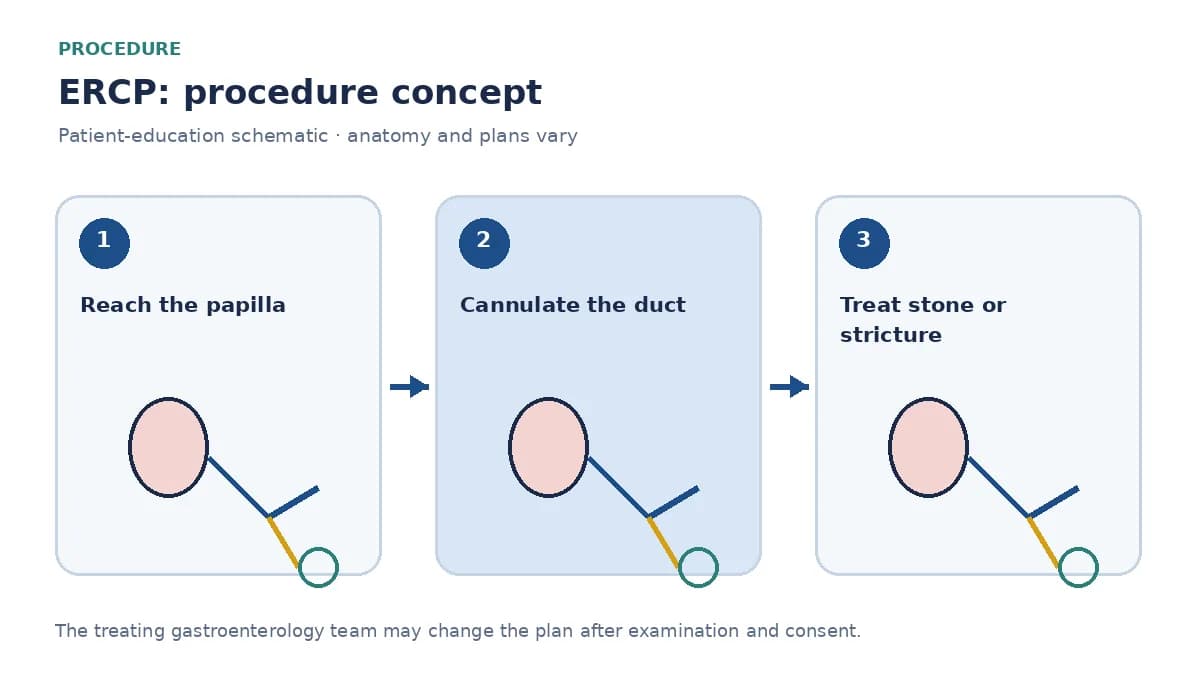
Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated.
Relevant options include Therapeutic ERCP for stones, ERCP with biliary stenting, Pancreatic-duct ERCP; they are not interchangeable package names.
Day-care to 2 nights is stored; pancreatitis, cholangitis or incomplete drainage can extend stay. Often 30–90 minutes depending on anatomy and interventions.
Main variations
- Therapeutic ERCP for stones
- Sphincterotomy and extraction when choledocholithiasis is the indication.
- ERCP with biliary stenting
- Plastic or metal stents for obstruction; the stent itself may be a separate line.
- Pancreatic-duct ERCP
- Selected leaks or strictures; pancreatitis risk and device choice differ from biliary work.
Preparation
Assessment includes liver tests, ultrasound, MRCP or CT, coagulation, and whether sphincterotomy, stone extraction or stenting is already expected.
The receiving team should reconcile anticoagulants, allergy, infection, airway or aspiration risk and any bowel-prep or fasting plan before a date is fixed.
Follow fasting and medicine-hold instructions from the treating team. Report fever, bleeding, jaundice, severe pain or another material change before travel.
Hospital stay and recovery
Day-care to 2 nights is stored; pancreatitis, cholangitis or incomplete drainage can extend stay. Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice.
Diet, hydration and activity limits are stated. Written instructions take priority over generic travel advice.
Risks include pancreatitis, bleeding, infection or cholangitis, perforation, stent blockage or migration, failed cannulation and need for PTBD or surgery.
Follow-up reviews symptoms, liver tests, stent plan and whether another ERCP or PTBD is needed. Seek urgent help for severe abdominal pain, vomiting, fever, jaundice, black stools or dizziness after ERCP; use the treating team's emergency thresholds.
How to compare ERCP quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is ERCP being considered, and what medical, endoscopic or surgical options were discussed?
- How were my symptoms, imaging, endoscopy reports and previous procedures assessed?
- Who is the named interventional gastroenterologist or pancreaticobiliary endoscopist, and at which exact campus will the procedure occur?
- Does the quotation use the exact name ERCP?
- Which consultations, blood tests, imaging and endoscopy are included?
- Are specialist, endoscopy-unit, sedation or anaesthesia and recovery-room fees included?
- Is this a diagnostic procedure only, or are therapeutic interventions assumed?
- Which stents, clips, balloons, sutures or other devices are assumed?
- Are manufacturer and model details provided where a device is used?
- Would an extra polyp, stone, stent or a different procedure change the quotation?
- How many ward or observation nights and which room category are included?
- How are extra nights, bleeding, pancreatitis, another procedure or a complication billed?
- Which discharge medicines and dietary instructions are included?
- Is pathology or biopsy charging included if tissue is taken?
- When can I fly, eat, work or resume other activity?
- Which follow-up visits, stent reviews or dietitian reviews are included?
- How are complications handled after I leave India?
- When and by whom will fitness to fly be assessed?
- What procedure report, images and emergency contacts will I receive?
- Which costs are explicitly excluded?
- Who will coordinate care with my clinician after I return home?
- Is sphincterotomy included?
- Which stent is assumed?
- How many observation nights are included?
Frequently asked questions
How much does ERCP cost in India?
ERCP is typically planned at $1,500–$4,200. This stored national range is not a quotation; anatomy, therapeutic add-ons, devices, monitoring and written terms determine the final amount.
What is ERCP?
ERCP combines endoscopy and X-ray imaging to diagnose and treat selected problems involving the bile ducts and pancreatic duct, including certain stones and blockages.
When is ERCP considered?
It may be considered when imaging suggests bile-duct stones, a stricture, a leak or selected pancreatic-duct disease and a clinician judges that endoscopic access is appropriate.
Is gastroenterology treatment in India automatically cheaper?
It may cost less than some self-pay markets, but quotations are not automatically comparable. Compare exact scope, clinician, facility, devices, imaging, monitoring and follow-up.
What assessment is needed before treatment?
Assessment includes liver tests, ultrasound, MRCP or CT, coagulation, and whether sphincterotomy, stone extraction or stenting is already expected.
What happens during the procedure?
Under sedation or anaesthesia, a side-viewing endoscope reaches the duodenal papilla. The duct is cannulated, contrast is injected and planned therapy — sphincterotomy, stone removal or stenting — is performed when indicated.
How long does ERCP take?
Often 30–90 minutes depending on anatomy and interventions. Actual timing depends on anatomy, findings during the case and the clinical course.
How long is the hospital stay?
Day-care to 2 nights is stored; pancreatitis, cholangitis or incomplete drainage can extend stay. Discharge is based on clinical criteria, not a package calendar.
What are the important risks?
Risks include pancreatitis, bleeding, infection or cholangitis, perforation, stent blockage or migration, failed cannulation and need for PTBD or surgery.
When can an international patient fly home?
There is no fixed flight day. Observation for pancreatitis, bleeding and infection is typical. Flying requires stable liver tests or a documented drainage plan and the team's advice. The treating team must document travel fitness.
Which Indian cities offer this procedure?
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad have relevant gastroenterology ecosystems, but actual availability requires an exact clinician and campus confirmation.
What follow-up is needed after returning home?
Follow-up reviews symptoms, liver tests, stent plan and whether another ERCP or PTBD is needed. The plan should name who reviews pathology, diet, stents or symptoms.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Bile Duct Stone Removal cost in India
$1,800–$5,000 · stay Day-care to 2 nights
Biliary Stenting cost in India
$2,000–$5,500 · stay 1–3 nights
Cholangioscopy cost in India
$2,500–$6,500 · stay Day-care to 2 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 12 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
ERCP cost sheet · All treatment costs in India · Gastroenterology costs



