
Last updated: 15 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Transoral Robotic Surgery (TORS) in India is typically planned at $9,000–$20,000. A useful estimate names the cancer treated, the exact resection and nodal scope, the operating surgeon, anaesthesia and facility fees, routine histopathology, ward nights and the early review. Which oropharyngeal site is resected, whether a neck dissection is combined, and whether a tracheostomy or feeding tube is added change the operation and the bill. Stored stay is 3–7 nights, though discharge and clearance to fly follow individual recovery.
The variables that move the figure most are oropharyngeal site and volume, combination with neck dissection, robot platform time, airway and feeding support. Changed findings, complications or a longer admission produce a different bill.
- India cost range
- $9,000–$20,000
- Typical starting point
- $9,000
- Typical hospital stay
- 3–7 nights
- Procedure time
- commonly 2–5 hours for the transoral component, longer when neck dissection is combined
- Recovery
- Three to seven nights typical
Major cost factors: oropharyngeal site and volume, combination with neck dissection, robot platform time, airway and feeding support. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed resection scope; complications and escalation; extended pathology; adjuvant treatment; rehabilitation and devices.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
It is generally considered for a well-visualised, resectable oropharyngeal tumour in a mouth that can be opened enough for the robot, often after HPV status and neck staging are known. Open resection or primary chemoradiotherapy remain alternatives.
Which oropharyngeal site is resected, whether a neck dissection is combined, and whether a tracheostomy or feeding tube is added change the operation and the bill. Two patients with the same diagnosis can therefore be quoted differently without either figure being wrong.
This page explains what the operation involves, what moves the estimate and which records a remote team needs. It cannot choose between surgery, systemic treatment, radiation or observation for an individual.
$9,000–$20,000, $35,000–$80,000 and 3–7 nights are planning tokens, not tariffs. Match any quotation to the planned resection, nodal scope, any reconstruction and the pathology performed.
What Is Transoral Robotic Surgery (TORS)?
The oropharynx includes the tonsil fossae, base of tongue, soft palate and lateral pharyngeal walls. Important nearby structures include the carotid artery, the nerves to the tongue and the swallowing sphincter. Neck nodes are usually addressed in the same treatment plan, often through a separate neck incision.
TORS is a route to the primary tumour, not a substitute for neck dissection and not a smaller cancer operation. A tumour that cannot be seen completely through the mouth, or that encases the carotid, is not a TORS case.

When Might Transoral Robotic Surgery (TORS) Be Considered?
A qualified head and neck surgical oncologist must assess suitability, normally with multidisciplinary review. A TORS-trained head and neck surgeon, a bedside assistant, a pathologist reading margins, a neck-dissection plan, and speech and swallow therapists are required.
A remote opinion can change after examination and repeat imaging.
How the operation is performed, recovery and variations →
Transoral Robotic Surgery (TORS) cost in India
The $9,000–$20,000 value is GAF's stored national planning range for TORS, not a fixed package. Replace it with an itemized quotation naming the head and neck surgical oncologist, the campus, the planned resection and nodal scope, the expected nights and the pathology plan.
Cost moves with oropharyngeal site and volume, combination with neck dissection, robot platform time, airway and feeding support, stage and local extent, previous cancer treatment, pathology depth, anaesthesia and medical risk, facility and admission scope, unplanned escalation. A limited resection is not comparable with radical surgery or with difficult anatomy after previous treatment.
Do not derive city tariffs from the national band. Keep $35,000–$80,000, flights, visas, transport, lodging, medicines, extra nights and a complication contingency in the same budget.
Costing the operation alone is the commonest budgeting error, because pathology, adjuvant treatment and rehabilitation are separate pathways with separate estimates.
Planning Range ≠ Final Hospital Quotation. Records review and qualified surgical, oncology and anaesthetic assessment come before any itemized offer.
Transoral Robotic Surgery (TORS) cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a surgical estimate, not a dollar amount for each row.
- Surgeon and assistant fees
- The named operating team.
- Theatre and anaesthesia
- Operating room time and anaesthesia.
- Consumables and devices
- Staplers, energy devices, drains, implants.
- Ward and critical care
- Room category and high-dependency nights.
- Histopathology
- Margin and nodal reporting.
- Imaging and laboratory
- Inpatient scans, tests, blood products.
- Medicines during admission
- Analgesia, antibiotics, thromboprophylaxis.
Planning range or quotation?
The $9,000–$20,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Transoral Robotic Surgery (TORS) package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Preoperative assessment
Surgeon and anaesthesia review where itemized.
Usually included
The consented operation
Surgeon, theatre, consented scope.
Usually included
Anaesthesia and routine medicines
Anaesthesia and stated monitoring.
Usually included
Hospital recovery as quoted
Stated ward nights and room category.
Usually included
Routine histopathology
Standard specimen and nodal reporting.
Usually included
Discharge documents
Operation note, summary, early review.
Usually included
Named operative plan
Only the stated TORS scope and approach are included.
May be charged separately
May be separate
Changed resection scope
Wider excision, extra nodal levels, unlisted reconstruction.
May be separate
Complications and escalation
Transfusion, intensive care, re-operation, longer stay.
May be separate
Extended pathology
Frozen section, immunohistochemistry, molecular panels.
May be separate
Adjuvant treatment
Chemotherapy, targeted therapy, radiotherapy, radioiodine.
May be separate
Rehabilitation and devices
Therapy, prostheses, dental work, medicines.
May be separate
Travel and living
Flights, visas, transport, lodging, companion.
Catalog inclusions listed for this pathway: surgical oncology consultation and records review; named surgeon on camera before travel; theatre, anaesthesia and inpatient stay as quoted; histopathology of the specimen; discharge summary to your home oncologist.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Oropharyngeal site and volume
- Tonsil and base-of-tongue resections differ in time, airway risk and swallow recovery.
- Combination with neck dissection
- Adding the neck is a second field with its own time and drain.
- Robot platform time
- Docking and single-use instruments are separate from the resection itself.
- Airway and feeding support
- Tracheostomy and feeding-tube placement add days and nursing intensity.
- Stage and local extent
- Invasive disease lengthens surgery and widens the resection.
- Previous cancer treatment
- Earlier chemotherapy or radiation alters tissue planes and risk.
- Pathology depth
- Frozen section and molecular testing are separate charges.
- Anaesthesia and medical risk
- Comorbidity changes monitoring and length of stay.
- Facility and admission scope
- Ward and intensive-care nights are different scopes.
- Unplanned escalation
- A complication or return to theatre changes the episode.
Cancer-specific surgical planning for Transoral Robotic Surgery (TORS)
Planning uses examination of the throat, biopsy with HPV testing where relevant, cross-sectional and often metabolic imaging of the neck and chest, and an anaesthetic assessment of mouth opening and airway.
Earlier chemotherapy, radiation or surgery alter tissue planes and operative risk, so those records matter as much as the current scan.
Margins, lymph nodes and what pathology decides
Margins in three dimensions, HPV status, depth and the neck-node yield drive whether postoperative radiation can be reduced, kept or omitted.
A cancer operation is judged on margin clearance and assessment of the nodes at risk, not on the size of the incision.
When the planned operation changes during surgery
Inadequate view, bleeding, or a tumour more extensive than expected can convert TORS to open resection, which may include dividing the jaw. Consent should cover tracheostomy, feeding tube and open conversion.
Multidisciplinary care and treatment sequencing
TORS may be used to de-intensify later radiation in selected HPV-related disease, or as the primary resection when the tumour is clearly resectable. Neck dissection timing and the radiation decision follow pathology.
Ask who owns each step and who decides the next one: treatment before surgery can change what operation is possible.
Function, rehabilitation and what may change permanently
Swallowing and speech are commonly affected for weeks and sometimes longer, especially after base-of-tongue resection. A feeding tube may be needed for a period, and taste change can persist.
Rehabilitation is part of the treatment, yet it is frequently excluded from surgical estimates. Confirm what is included and what continues at home.
Follow-up, surveillance and international travel
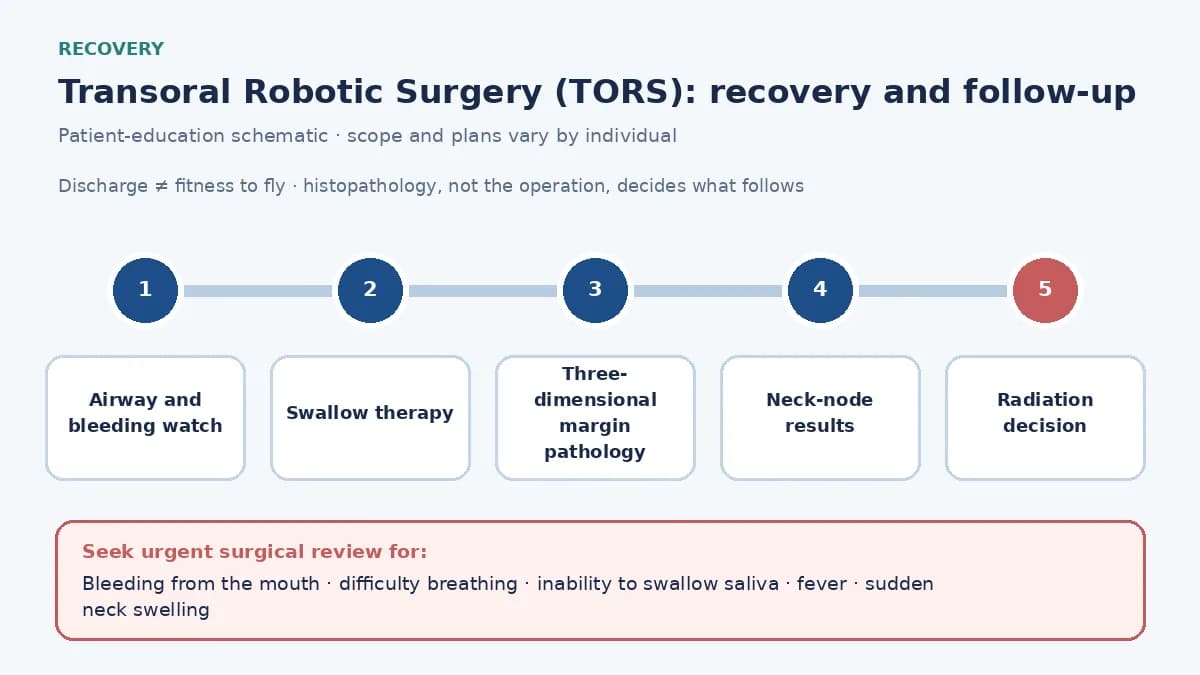
The home team should receive the operation note, margin and HPV pathology, neck-node results, and the swallow plan, then coordinate radiation where advised. Discharge from the ward is not the same as clearance to fly.
Transoral Robotic Surgery (TORS) cost: India vs other medical tourism destinations
India and United States values are stored GAF catalog ranges. Other countries need direct quotations, because comparable cancer-surgery packages are not held in the catalog.
A meaningful comparison holds diagnosis, resection and nodal scope, surgeon, facility, pathology depth and ward nights constant.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $9,000–$20,000 | Baseline | GAF catalog planning range. The stored India figure is a national planning range for the operation and its stated admission. It does not establish resectability, surgical scope, nodal plan, reconstruction, pathology depth or a final quotation. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Compare the exact resection, nodal dissection, reconstruction, frozen-section policy, intensive-care assumption, ward nights and complication terms rather than a headline cancer-surgery package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Depends on procedure and hospital. International coordination does not by itself establish case acceptance, multidisciplinary review, reconstructive cover or continuity of adjuvant treatment after the patient returns home. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Surgeon, facility, anaesthesia, consumable, histopathology and follow-up charges are frequently billed separately, so a single quoted figure may not be the comparable one. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Request a self-pay estimate tied to the specific cancer, the planned resection and nodal scope and the expected admission. Subsidised local billing and private international billing differ. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Eligibility, professional billing, pathology scope and post-travel oncology follow-up need direct confirmation. Inpatient norms after major cancer surgery are often longer than in self-pay markets. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, quotation boundaries, emergency access and who reviews final histology and decides adjuvant treatment once they have travelled home. |
| United States | $35,000–$80,000 | ≈4× India | Stored self-pay reference. Facility, surgeon, anaesthesia, pathology and follow-up charges are usually separate, and $35,000–$80,000 is a comparison range for the operation rather than a bundled cancer-treatment quotation. |
Comparisons are indicative and may not represent identical operations. Tumour extent, added resection, complications, currency and length of stay change the final amount.
The point of this table is not that one country is better. Cost level and treatment-market structure are different things. Compare the named hospital, multidisciplinary support, included care and follow-up pathway as carefully as the headline figure.
Which destination is right for you?
Use this only as a reading guide for the table above. It is not a medical recommendation, and it does not rank countries.
Looking for the lowest overall treatment cost?
IndiaLooking for premium private hospital infrastructure?
Singapore / UAELooking for proximity from the Middle East?
UAE / India / TurkeyLooking for established European oncology systems?
Germany / UK
Why do international patients consider India for TORS?
Patients evaluate India for access to a named head and neck surgical oncologist, multidisciplinary cancer services in one city, and a self-pay planning range below the stored United States reference. Cost alone is not a clinical reason to travel.
What matters is individual acceptance, procedure-specific experience, intensive-care support, histopathology quality, reconstructive cover where relevant, and who continues adjuvant treatment.
No provider is ranked here and no outcome is promised. Unstable illness, or treatment already under way locally, can make an elective trip inappropriate.
Hospitals for Transoral Robotic Surgery (TORS) in India
Cards follow exact CMS relationships for Transoral Robotic Surgery (TORS). Accreditation alone does not establish current case acceptance.
Campuses for this pathway are being confirmed. Ask the desk which houses currently quote it.
Surgical oncologists to consider for Transoral Robotic Surgery (TORS) in India
Profiles appear only where Transoral Robotic Surgery (TORS) is an exact current CMS relationship. Placement is not a ranking or an outcome claim.
Named consultants for this pathway are being matched. Request a dossier and we will advise which campuses can quote it.
Transoral Robotic Surgery (TORS) cost by city in India
The five listed cities retain $9,000–$20,000 because no verified city tariffs are stored. Their overlays add airport geography, climate, lodging and recovery logistics rather than local prices.
Cards resolve only from CMS entities carrying the exact Transoral Robotic Surgery (TORS) relationship, so missing mappings leave cards empty.
Swipe to compare Indian cities →
Delhi NCR
$9,000–$20,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Delhi NCR-only tariff is stored for TORS. Use $9,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Mumbai
$9,000–$20,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Mumbai-only tariff is stored for TORS. Use $9,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Bengaluru
$9,000–$20,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Bengaluru-only tariff is stored for TORS. Use $9,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Chennai
$9,000–$20,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Chennai-only tariff is stored for TORS. Use $9,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Hyderabad
$9,000–$20,000
India planning band — not a city quote
Typical stay 3–7 nights
No verified Hyderabad-only tariff is stored for TORS. Use $9,000–$20,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for TORS
Patients usually pick the treating team first and the city second. The city still affects daily travel, accommodation, companion arrangements and access to follow-up. Here is what genuinely differs between the five cities we list.
What should international patients budget beyond the surgery?
The surgical estimate is only one line in a medical-travel budget. The rows below separate hospital charges from living and travel costs so you can plan without treating a brochure package as a trip total.
- Treatment episode$9,000–$20,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay3–7 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for TORS in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Submit records
Biopsy, imaging files, treatment summaries, laboratory results.
Specialist review
A named head and neck surgical oncologist reads imaging and pathology.
Pathology verification
Local slide review can change diagnosis or grade.
Staging assessment
Remaining imaging or nodal sampling.
Multidisciplinary opinion
Surgery, oncology and pathology together.
Written treatment plan
Intent, resection scope, nodal plan, admission.
Itemized cost estimate
Surgery and stay quoted apart from adjuvant therapy.
Medical visa and travel
An invitation letter supports the visa.
Arrival and reassessment
Examination, repeat tests, anaesthetic clearance, consent.
Surgery
The consented TORS and planned monitoring.
Monitored recovery
Ward care, mobilisation, wound and drain review.
Pathology review
Margins, nodes and further testing discussed.
Return home and handover
Documents, medicines, a named clinician for follow-up.
Documents to prepare
- Biopsy of the oropharyngeal tumour with HPV testing where performed
- Imaging of the throat, neck and chest with image files
- Notes on mouth opening, dentition and swallow
- Imaging files on a disc or drive rather than screen photographs
- Paraffin blocks or slides where the home laboratory releases them
- Summaries of previous chemotherapy, immunotherapy, targeted therapy or radiation
- Operative notes from earlier cancer or regional surgery
- Current medicines, allergies and previous anaesthetic problems
- Recent blood count, kidney and liver results
- Passport, visa and companion details
Clinical detail
How the operation is performed
With the patient asleep and the mouth held open, the robot is docked transorally, the tumour is excised with a three-dimensional margin, frozen section may guide further excision, haemostasis is secured, and the neck is addressed as planned, sometimes at the same sitting.
The specimen goes to histopathology. Theatre time is commonly 2–5 hours for the transoral component, longer when neck dissection is combined.

Main variations
- TORS tonsillectomy for cancer
- Radical tonsil resection of a tonsil primary through the mouth.
- TORS base-of-tongue resection
- Removes a base-of-tongue tumour with a swallow-preserving margin where possible.
- TORS with ipsilateral neck dissection
- The primary is removed through the mouth; the neck is opened separately.
- Staged TORS then neck surgery
- Separates the two sittings when airway or pathology timing requires it.
- Open conversion
- Mandibulotomy or other open access if transoral resection cannot be completed.
Preparation
Assessment commonly includes mouth opening, dentition, airway, swallow baseline, neck imaging and a discussion of tracheostomy and feeding-tube likelihood.
Reconcile blood thinners, diabetes medicines, inhalers and allergies before travel. Consent should name the resection scope, the nodal plan and what findings could change either.
Hospital stay and recovery
Admission is frequently three to seven nights, watching the airway, bleeding from the mouth and the ability to swallow saliva. Recovery is led by airway safety, bleeding watch, pain that allows swallowing, and speech and swallow therapy rather than a fixed date.
Recognised risks include bleeding from the mouth that can threaten the airway, temporary or lasting swallow change, taste change, tooth or lip injury from the gag, airway swelling, and the usual risks of any neck dissection performed with it.
Seek urgent help for bleeding from the mouth, difficulty breathing, inability to swallow saliva, fever, or sudden neck swelling.
How to compare Transoral Robotic Surgery (TORS) quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is TORS recommended, and what alternatives remain?
- Is the intent curative or symptom control?
- Who is the named head and neck surgical oncologist, and at which campus?
- What will be removed, and what will be preserved?
- What function may change permanently?
- What findings could change the consented scope?
- Was this case discussed at a tumour board?
- Is any treatment recommended before surgery?
- Which existing tests are accepted rather than repeated?
- Which surgeon, anaesthesia and facility fees are included?
- Which implants or consumables are assumed?
- Will frozen section be used, and is it included?
- Which histopathology and molecular tests are included?
- Is reconstruction inside this estimate?
- How are transfusion, intensive care and extra nights billed?
- How many nights and which room category are assumed?
- Which rehabilitation follows discharge?
- What warning signs need urgent review before I fly?
- When is histopathology ready, and who explains it?
- Who delivers adjuvant treatment if advised?
- Which oropharyngeal site will be resected, and is neck dissection in the same estimate?
- Are robot platform charges itemized?
- Are tracheostomy and feeding-tube placement included if they become necessary?
Why your final Transoral Robotic Surgery (TORS) cost may be different
This page carries a planning range. A hospital letter is an estimate written against a named operation, surgeon, room category and stated nights, so the two are not expected to match.
If two hospitals quote differently, read the line items before assuming one is overcharging: one may include frozen section and immunohistochemistry while the other bills them later.
A total medical trip costs more than the operation. Flights, visas, transport, lodging, an attendant, medicines, pathology and extra nights sit outside the surgical estimate.
Frequently asked questions
How much does TORS cost in India?
$9,000–$20,000 is a national planning range rather than a quotation. Resection scope, nodal dissection, reconstruction, pathology depth and length of stay determine the final bill.
What is TORS?
Transoral robotic surgery removes selected tumours of the oropharynx — tonsil, base of tongue or adjacent throat — through the mouth using a surgeon-controlled robotic platform, avoiding an open incision through the jaw or neck for the primary tumour.
What decides how extensive the operation is?
TORS is a route to the primary tumour, not a substitute for neck dissection and not a smaller cancer operation.
Which staging is needed before surgery?
Planning uses examination of the throat, biopsy with HPV testing where relevant, cross-sectional and often metabolic imaging of the neck and chest, and an anaesthetic assessment of mouth opening and airway.
Who may be considered for this operation?
It is generally considered for a well-visualised, resectable oropharyngeal tumour in a mouth that can be opened enough for the robot, often after HPV status and neck staging are known.
How long does TORS take?
Theatre time is commonly 2–5 hours for the transoral component, longer when neck dissection is combined. Findings and any reconstruction can change it.
How long is the hospital stay?
Admission is frequently three to seven nights, watching the airway, bleeding from the mouth and the ability to swallow saliva. Clinical criteria, not a schedule, determine discharge.
What are the important risks?
Recognised risks include bleeding from the mouth that can threaten the airway, temporary or lasting swallow change, taste change, tooth or lip injury from the gag, airway swelling, and the usual risks of any neck dissection performed with it.
What may change permanently after this surgery?
Swallowing and speech are commonly affected for weeks and sometimes longer, especially after base-of-tongue resection.
Will treatment be needed after the operation?
TORS may be used to de-intensify later radiation in selected HPV-related disease, or as the primary resection when the tumour is clearly resectable. Final histopathology usually decides this.
When can an international patient fly home?
There is no fixed date. Recovery is led by airway safety, bleeding watch, pain that allows swallowing, and speech and swallow therapy rather than a fixed date. The team must confirm fitness to fly.
What follow-up is needed after returning home?
The home team should receive the operation note, margin and HPV pathology, neck-node results, and the swallow plan, then coordinate radiation where advised.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Oral Cancer Surgery cost in India
$6,000–$16,000 · stay 5–10 nights
Neck Dissection cost in India
$4,500–$12,000 · stay 3–6 nights
Intensity-Modulated Radiotherapy (IMRT) cost in India
$6,500–$14,500 · stay 4–7 weeks of fractions
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 15 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Transoral Robotic Surgery (TORS) cost sheet · All treatment costs in India · Surgical Oncology costs



