
Last updated: 10 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Esophagectomy in Mumbai is planned against $12,000–$28,000 and 10–18 nights in hospital — the India catalog band, not a Mumbai-only tariff. Named consultants for this exact procedure are matched after records review.
Budget extra for accommodation. A multi-week companion stay in Mumbai is typically the most expensive of the five listed cities, and Navi Mumbai hotels are not interchangeable with island-city hotels.
- India cost range
- $12,000–$28,000
- Typical starting point
- $12,000
- Typical hospital stay
- 10–18 nights
- Procedure time
- approximately 4–8 hours
- Recovery
- Inpatient 10–18 nights, then hotel step-down. Varies by patient.
Major cost factors: hospital category and campus tier, surgeon and team, city and companion logistics, open versus minimally invasive surgery. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: advanced staging; neoadjuvant and adjuvant oncology; extra icu, leak management and re-operation; nutrition after discharge; blood products.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
Esophagectomy in Mumbai
Mumbai is the city families choose when they want a high-volume private oncology week and are willing to pay for that in time stuck in traffic and in three weeks of hotel bills — not when they need a long, already-tagged esophagectomy name list on this site.
The catalog does not currently tag a Mumbai doctor to esophagectomy or esophageal cancer surgery. That is the site being precise, not a missing widget. A coordinator matches a listed surgical oncologist after endoscopy and staging are read, then asks whether Ivor Lewis, McKeown or MIE is actually offered that week.
Listed campuses — Wockhardt, Gleneagles Mumbai, Apollo Navi Mumbai, Medicover — run heavy cancer lists. Comprehensive infrastructure is not the same as a named upper-GI resection consultant in the database. Ask who would operate before you buy a ticket.
The harbour split is the planning fact that a 10-to-18-night ICU-to-ward admission punishes hardest. A Gleneagles letter and a Navi Mumbai step-down hotel are not 'Mumbai' in the way a taxi app suggests.
If the plan is neoadjuvant chemoradiation in Mumbai then resection in another city, you are writing two medical visas. Families who assume one invitation letter covers both stages discover the paperwork on week four.
Companion living costs over three weeks are typically the highest of the five listed cities. That does not change the surgical fee. It changes whether completing adjuvant treatment here is cheaper than flying home between stages.
Monsoon scheduling is a cost issue for leak-related readmission and for getting a companion to ICU at 2 a.m. If you can choose a date, avoid peak July unless the family is prepared to sit tight next to the hospital.
Mumbai rewards the family that rents next to the operating campus and ignores the airport hotel. It punishes the family that treats 'Mumbai hospitals' as interchangeable pins across the harbour.
Families still shortlist Mumbai when the flight map from East Africa or the Gulf is better, or when a comprehensive private oncology week is already under way here. That is a logistics choice. It is not evidence that a tagged esophagectomy name exists on this site. Ask the coordinator who would actually resect, and whether that person operates on the island or in Navi Mumbai, before you rent.
Wockhardt and Gleneagles sit in the island-city gravity. Apollo Hospitals Navi Mumbai and Medicover sit across the harbour. International desks at those houses are used to visa letters. They are not interchangeable ICUs. A leak at 2 a.m. does not respect a trans-harbour taxi quote you saved at booking.
After discharge, local trains are a poor plan for a companion carrying feeds. Pair a serviced flat to the ward entrance. If the letter is Navi Mumbai, do not keep the family in Bandra because the restaurants look familiar. The three-week hotel line is the Mumbai tax; paying it twice by commuting is how the trip overruns without the surgical fee moving.
If adjuvant radiation or chemotherapy will continue in Mumbai, say so on day one so the visa and the apartment are written for the longer stay. Completing drugs in another city after a Mumbai resection is two invitation letters and a second set of flights. That can still be the right plan. It should not be a surprise in week three.
What esophagectomy typically costs in Mumbai
Once a surgeon is matched, letters still split on approach, ICU nights, campus tier and reconstruction. What inflates the trip is living cost: serviced apartments near the ICU, and traffic that turns a five-kilometre map line into an hour.
Navi Mumbai quotes should be read as Navi Mumbai logistics. A cheaper letter from a harbour-side campus is not cheaper if every ICU visit requires a trans-harbour commute.
Monsoon slack is a real line for a leak week. Build it into the ticket.
CSMIA looks central on a map and is not central to an ICU stay. Families who keep a room in Andheri 'for the airport' spend the admission in traffic. Rent for the ward door. Count three weeks of food and a companion's lost work as Mumbai-specific lines, not as the surgical fee.
What moves the quote in Mumbai
- No named catalog consultant yet
- Matching is records-first. Delhi NCR, Chennai and Hyderabad currently have named esophageal-cancer surgery listings.
- Mumbai versus Navi Mumbai
- Different ICUs, different hotel markets. The estimate should name the operating address.
- Three-week hotel inflation
- Companion living costs here are typically the highest of the five cities over an esophagectomy recovery.
- Monsoon and leak readmission
- Humidity and traffic do not help a midnight return to ICU. Stay next to the campus.
- Neoadjuvant in one city, resection in another
- Two stages can mean two invitation letters. Say so on day one.
Medical travel through Mumbai
Most families land at CSMIA and transfer 45 to 90 minutes. Do not book same-week theatre after a long-haul flight into peak traffic.
Write the visa for 10–18 nights plus hotel recovery. Mention a possible leak week so duration is not undershot.
English works at the international counter. Marathi and Hindi are the ward languages.
Monsoon weeks punish midnight readmissions. If the diary is flexible, avoid peak July unless the attendant can live inside walking distance of the ICU. Harbour taxis at 2 a.m. are not a backup plan.
Hospitals and units listed in Mumbai
Listed Mumbai-region campuses on the surgical-oncology pathway include Wockhardt, Gleneagles Hospital Mumbai, Apollo Hospitals Navi Mumbai and Medicover Navi Mumbai. Named esophagectomy consultants are matched after records review. Check each profile for accreditation as published.
Ask where the ICU is, whether leaks are managed on that floor, and where you will sleep for three weeks.
Doctor cards on this city view are Mumbai-filtered. An empty grid for this exact procedure is the catalog being precise.
Esophagectomy doctors in Mumbai · Esophagectomy hospitals in Mumbai · Esophagectomy cost in India
What is an esophagectomy?
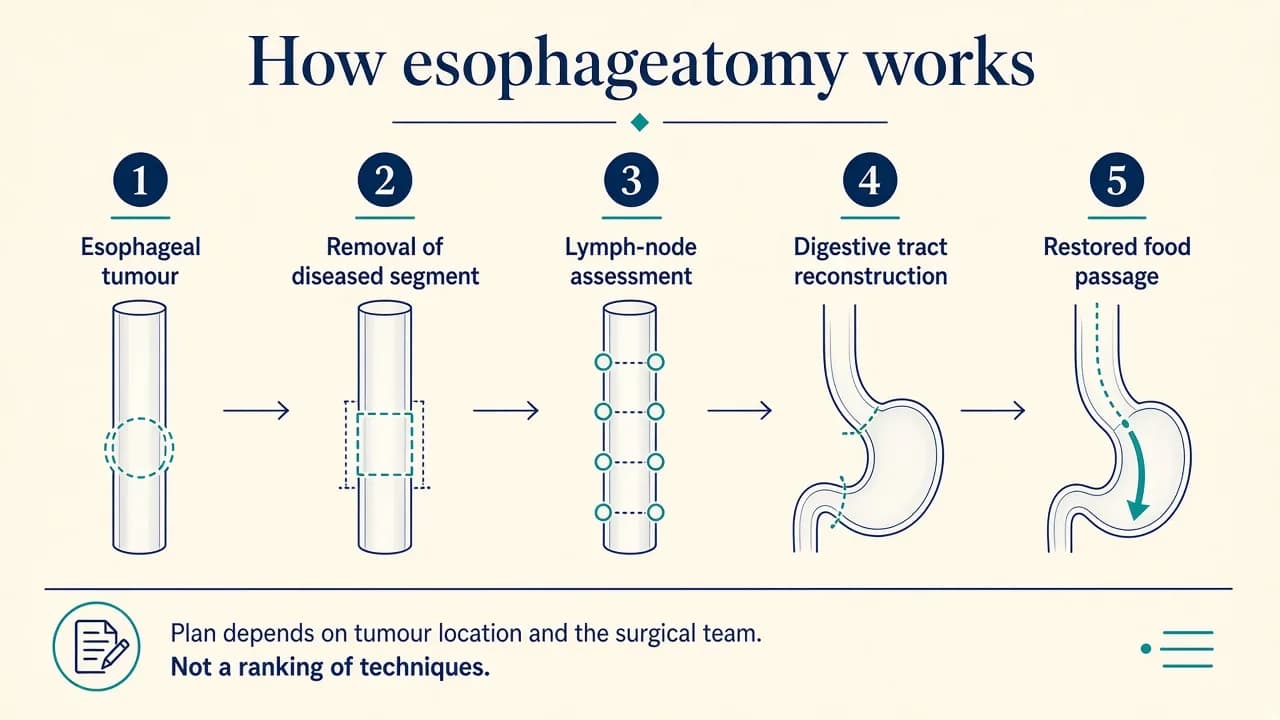
Esophagectomy is surgical removal of part or most of the oesophagus, the muscular tube that carries food from the throat to the stomach. In cancer care it is done to take out the tumour with a margin of oesophagus and, where indicated, regional lymph nodes, then restore a path for swallowing.
Reconstruction usually uses the stomach as a conduit pulled up to replace the resected segment. When the stomach cannot be used, colon or jejunum may be considered. The join — the anastomosis — sits in the chest or the neck depending on the approach. That join is why leak monitoring dominates the first postoperative week.
Lymph-node assessment is part of staging and local control when the protocol calls for it. Two-field and three-field dissections are different sittings. Multidisciplinary care — surgical oncology, medical oncology, radiation oncology, gastroenterology, radiology, pathology, nutrition and critical care — frames whether surgery is even the next step.
The exact operation depends on tumour location, stage, anatomy, treatment history including neoadjuvant chemotherapy or radiotherapy, and the surgeon's assessment. GAF Healthcare does not decide on this page whether resection is appropriate. Treatment plans are determined by qualified doctors after evaluation. Quotes may change if the surgical plan changes.
Who may be a candidate for esophagectomy?
Esophagectomy may be considered for selected oesophageal cancers and selected gastro-oesophageal junction cancers when staging suggests resection can be completed with acceptable risk, and for other conditions where the treating team judges oesophageal resection necessary. It is not the first or only treatment for every oesophageal cancer. Some patients are treated with chemoradiation, endoscopic therapy, or systemic therapy without resection.
Fitness matters as much as the scan. Heart and lung function, nutrition, prior radiation to the chest, and whether the patient can recover from a leak all feed the decision. Neoadjuvant treatment, when used, is sequenced before surgery and is a separate estimate.
This page does not diagnose and does not recommend esophagectomy, endoscopic therapy or non-operative care for an individual patient. Eligibility depends on cancer type, stage, previous treatment and clinical assessment.
How the operation is performed, recovery and variations →
Esophagectomy cost in India
There is no single esophagectomy price in India. The $12,000–$28,000 band is a planning range for a high-acuity oesophageal resection — theatre, anaesthesia, the named surgeon's fee, the quoted room, routine inpatient drugs, ICU as written into the estimate, and histopathology. The lower end typically reflects a straightforward transhiatal or Ivor Lewis case at a mid-tier NABH campus with an uncomplicated ICU course toward the shorter end of 10–18 nights. The upper end typically reflects a flagship JCI campus, a senior upper-GI or thoracic surgical oncologist, a three-field McKeown or a long minimally invasive sitting, a private room, and a stay toward 18 nights.
Treat that band as an order of magnitude until a surgeon who actually resects oesophagus has seen endoscopy, staging CT or PET-CT, biopsy, and whether neoadjuvant treatment has already been given. Same procedure name is not the same surgical plan. Ivor Lewis, McKeown, transhiatal, minimally invasive and robotic-assisted access are different theatres. A letter written for one is not a letter written for another.
City is a weaker driver than families expect. ICU policy, leak-management experience, campus tier and whether nutrition support is bundled move the bill more than the metro name. An itemised estimate can only be written once a surgeon has read the file. GAF Healthcare matches centres that already run this list, with ICU that has seen anastomotic leaks — that is a matching rule, not a ranking of hospitals.
What moves the number most is approach (Ivor Lewis, McKeown, transhiatal, minimally invasive), reconstruction, whether a leak or pneumonia extends ICU, campus tier, the named consultant, and whether chemotherapy or radiation sits in the same trip. International patients should budget the weeks around the knife — not only the theatre block.
Esophagectomy cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a surgical estimate, not a dollar amount for each row.
- Surgeon fee and surgical team
- Usually bundled for the named surgical oncologist or surgical gastroenterologist. Confirm who is in theatre, and whether a thoracic colleague is billed separately on a two-field or three-field case.
- Hospital and operating-room charges
- A long theatre block, staplers, conduits, drains and recovery. Minimally invasive or robotic access, when used, lengthens or reprices this block. Campus tier moves this line more than the city name.
- Anaesthesia
- Anaesthetist fee and drugs for a case lasting typically four to eight hours, often with one-lung ventilation if the chest is opened. Cardiopulmonary comorbidity may add a pre-operative clearance billed outside.
- ICU and critical-care monitoring
- Early ICU or high-dependency care is usual after oesophageal resection. Nights inside the quoted stay may be bundled; extra ICU days after a leak or pneumonia are typically extra. Ask how many ICU nights the letter actually prices.
- Diagnostic investigations
- Standard bloods and ECG are often inside the admission. Staging endoscopy, CT, PET-CT, pulmonary function tests and cardiac clearance are frequently extra if not already done at home.
- Pathology
- Processing of the specimen and lymph nodes. Immunohistochemistry and molecular tests, when ordered, are often billed later.
- Medicines, nutrition and feeding
- Inpatient analgesia, antibiotics, DVT prophylaxis and routine drugs during the quoted stay. Jejunostomy feeds, parenteral nutrition and discharge formula are frequently extra. This page does not set a diet.
- Room charges and nursing
- Written against a room category and a stated number of nights — typically 10–18 nights. Step-down from ICU to ward should be named. Companion beds change the nightly rate.
- Postoperative care and follow-up
- Inpatient leak checks, drain management and the first clinic review before you fly are commonly included. Later endoscopy, oncology visits and rehabilitation are typically separate.
Planning range or quotation?
The $12,000–$28,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Esophagectomy package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Consultation that leads into the admission
The in-person pre-operative review with the named surgeon, where bundled. Remote review before travel is arranged separately.
Usually included
Surgery by the named consultant
The resection and reconstruction as written on the estimate — not an unnamed robotic sitting or a colon interposition unless the letter says so.
Usually included
Anaesthesia and operating room
The anaesthesia team, theatre time, standard consumables and recovery for the scheduled case.
Usually included
Hospital stay as quoted
Bed charges, nursing and routine ward care for the room category and nights written into the estimate — typically 10–18 nights, including ICU nights if the letter names them.
Usually included
Routine tests
Standard bloods, ECG and anaesthetic fitness assessment, where bundled.
Usually included
Pathology of the specimen
Processing of the resected oesophagus and sampled nodes, where histopathology is bundled.
Usually included
Medicines during admission
Analgesia, antibiotics and routine drugs administered during the quoted stay.
May be charged separately
May be separate
Advanced staging
PET-CT, staging endoscopy, endoscopic ultrasound and pulmonary function tests are frequently extra when ordered in India.
May be separate
Neoadjuvant and adjuvant oncology
Chemotherapy, chemoradiation, radiotherapy and later systemic therapy are neighbouring quotes.
May be separate
Extra ICU, leak management and re-operation
Nights and theatre beyond the quoted stay, including treatment of anastomotic leak, are typically a new event.
May be separate
Nutrition after discharge
Jejunostomy formula, parenteral nutrition and dietitian follow-up after you leave the ward are often extra.
May be separate
Blood products
Transfusion, when required, is commonly billed per unit.
May be separate
Molecular pathology
HER2, PD-L1 and other assays, when ordered, are frequently extra.
May be separate
Rehabilitation and later endoscopy
Swallow therapy, physiotherapy after discharge and anastomotic dilatation if needed are typically separate visits.
May be separate
Travel, accommodation and visa-related expenses
Flights, medical visa fees, hotel after discharge, local transport and companion living costs sit outside every hospital estimate.
Catalog inclusions listed for this pathway: surgical oncology consultation and records review; named surgeon on camera before travel; theatre, anaesthesia and inpatient stay as quoted; icu nights named in the estimate; histopathology of the specimen; discharge summary to your home oncologist.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Hospital category and campus tier
- Flagship versus satellite units sit at different price levels. Ask which address, and which ICU, the letter is written against.
- Surgeon and team
- The estimate should name the consultant. Upper-GI surgical oncology and thoracic lists are billed differently. That is not a ranking.
- City and companion logistics
- Surgical fees cluster more tightly across the five metros than hotel bills for a two-to-three-week stay. City choice matters most after discharge.
- Open versus minimally invasive surgery
- Laparoscopic or thoracoscopic access, when offered, changes theatre time and consumables. No separate GAF sheet — ask whether MIE is actually available that week.
- Robotic assistance
- Robotic-assisted esophagectomy, where clinically offered, is a different resource envelope. There is no separate GAF robotic-esophagectomy tariff. Do not assume a thoracic-robotics brochure applies.
- Tumour location and disease complexity
- Mid-oesophageal tumours, junction tumours and prior chemoradiation change fields, anastomosis site and leak risk. Complexity is why two patients with the same diagnosis receive different letters.
- Reconstruction technique
- A gastric pull-up is the usual conduit when anatomy allows. Colon or jejunal reconstruction, when required, is a longer operation and a different letter.
- Lymph-node dissection
- Two-field and three-field lymphadenectomy are not the same sitting. Extent follows staging and the team's protocol, not a price list.
- Preoperative treatment
- Neoadjuvant chemotherapy or chemoradiation is a neighbouring cost sheet and can change fitness and timing. It is not inside $12,000–$28,000 unless named.
- ICU requirement and length of stay
- Packages are written for 10–18 nights, including some ICU. Extra nights after a leak, arrhythmia or pneumonia are usually billed fresh.
- Complications
- Anastomotic leak, chyle leak, recurrent-nerve injury and re-intubation are new events unless the contract says otherwise.
- Additional cancer treatment
- Adjuvant drugs, radiation and later endoscopy sit outside the surgical estimate.
Types of esophagectomy and how they can affect cost
Approach is chosen to clear the tumour and reconstruct a usable food passage, not to sell a named operation. GAF Healthcare publishes a planning range only where a cost sheet already exists. The rows below describe relative complexity. They are not a menu of add-on prices, and none is universally better.
Selection depends on tumour location, stage, prior treatment, anatomy and the reconstructive plan. This page does not recommend Ivor Lewis, McKeown, transhiatal, minimally invasive or robotic-assisted surgery for an individual patient.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
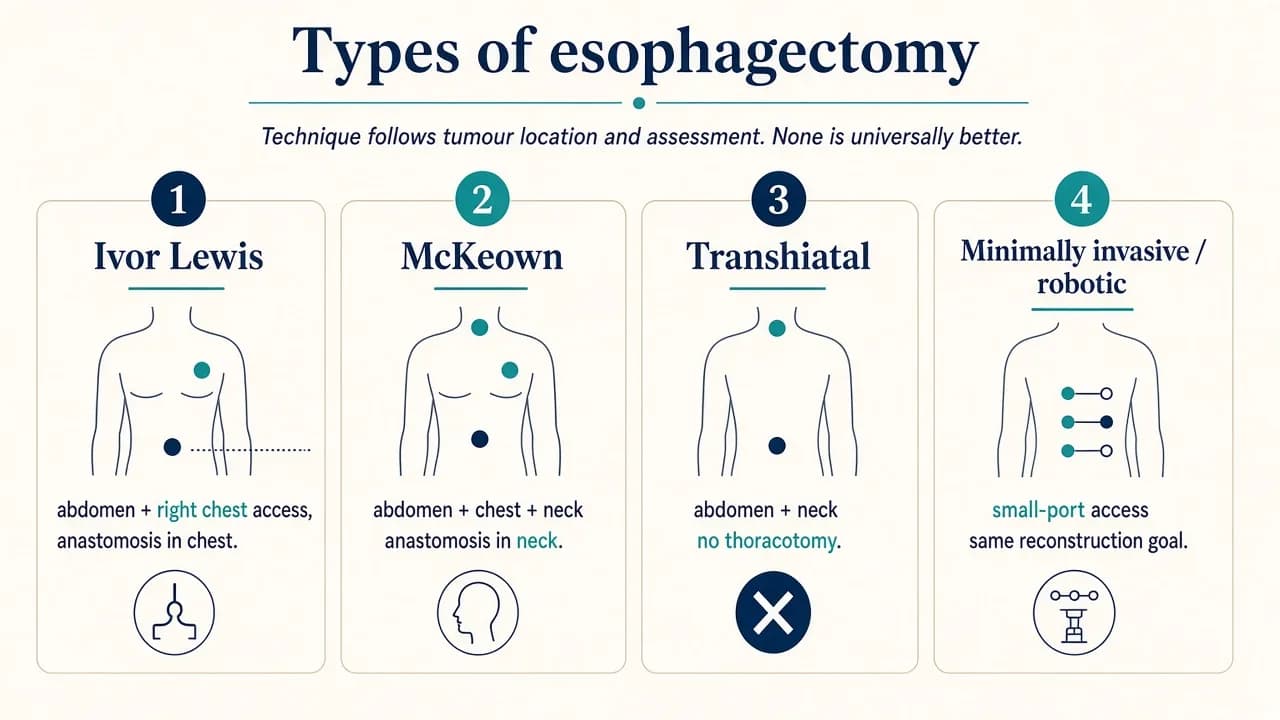
| Ivor Lewis esophagectomy | Two-field: abdomen and right chest | No separate GAF sheetRelative complexity only | Abdominal mobilisation of the conduit, thoracic resection, anastomosis usually in the chest. Common for mid and lower-third tumours when the team uses this sequence. No separate GAF sheet — relative complexity within $12,000–$28,000. |
| McKeown esophagectomy | Three-field: abdomen, chest and neck | No separate GAF sheetRelative complexity only | Anastomosis typically in the neck. Often discussed for more proximal tumours. Longer sitting and a neck wound as well as chest and abdomen. No separate GAF price. |
| Transhiatal esophagectomy | Abdomen and neck — no routine thoracotomy | No separate GAF sheetRelative complexity only | Resection through the hiatus with a neck anastomosis. Avoids a planned thoracotomy when the team judges it appropriate. Different mediastinal exposure, not a cheaper 'minor' version. No separate GAF sheet. |
| Minimally invasive esophagectomy (MIE) | Laparoscopic and/or thoracoscopic access | No separate GAF sheetRelative complexity only | Same oncological jobs through ports when anatomy and the team allow. Theatre and stapler costs can sit toward the upper part of the band. Availability is a diary question, not a brochure guarantee. |
| Robotic-assisted esophagectomy | Where offered — different resource envelope | No separate GAF sheetRelative complexity only | Robotic access is not universally available and is not priced as a separate GAF esophagectomy sheet. Ask whether it is actually offered for your tumour that week. Do not use a neighbouring thoracic-robotics tariff as a substitute. |
| Gastrectomy when the junction tumour is gastric-sided | Different operation — neighbouring sheet | $9,000–$22,000Catalog planning range | Some gastro-oesophageal junction cancers are treated as gastric resections rather than oesophageal ones. That is a different cost sheet, not an esophagectomy add-on. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
Esophagectomy cost: India vs other medical tourism destinations
The table below is a planning comparison for esophagectomy as a surgical episode, not a claim that every country uses the same approach or bundles ICU the same way. India and United States figures come from the GAF Healthcare catalog. Other markets are modelled from the India midpoint using relative private-care cost levels, and are labelled as modelled estimates — indicative market ranges, not hospital quotations.
India is often less expensive for a self-funding patient. That is not the same as 'always cheapest' or 'best'. Insurance coverage at home can reverse the arithmetic overnight. Hospital, surgeon, approach, reconstruction, tumour complexity, ICU, length of stay, oncology treatment and what the package includes still decide the real bill in every country.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $12,000–$28,000 | Baseline | Catalog planning range. Named esophageal-cancer surgery listings can be met on camera before travel. Listed consultants currently sit in Delhi NCR, Chennai and Hyderabad; Mumbai and Bengaluru are matched after records review. |
| Turkey | $20,000–$36,000Indicative planning estimate* | ≈1.4× India | Packaged medical-travel market. Verify whether ICU nights, leak management, PET-CT, neoadjuvant drugs and feeding support are inside the bundle. |
| Thailand | $24,000–$44,000Indicative planning estimate* | ≈1.7× India | Private-hospital tourism. Established international desks; ICU extras and oncology drugs can sit well above India. |
| United Arab Emirates | $40,000–$68,000Indicative planning estimate* | ≈2.7× India | Regional premium private care. Short flights from much of Africa and West Asia; private oncology pricing is closer to Western self-pay. |
| Singapore | $52,000–$88,000Indicative planning estimate* | ≈3.5× India | High-cost private hub. Mature multidisciplinary process at premium private tariffs. Local subsidised and international private bills differ. |
| Germany | $44,000–$84,000Indicative planning estimate* | ≈3.2× India | Certified European upper-GI units. Structured MDT process and longer inpatient norms; self-pay deposits are typical for visitors. |
| United Kingdom | $36,000–$68,000Indicative planning estimate* | ≈2.6× India | Private self-pay (NHS generally not for visitors). NHS care is not available to most overseas visitors. Private self-pay applies; neoadjuvant treatment is quoted separately. |
| United States | $50,000–$120,000 | ≈4.3× India | Highest self-pay outlier. Facility, surgeon, ICU, pathology and later oncology bills often arrive separately. Compare against actual insurance liability. |
*Figures other than India and the United States are modelled planning estimates scaled from the India catalog band, not hospital quotations. International treatment costs vary by hospital, surgeon, surgical approach, tumour complexity, reconstruction, length of stay, ICU requirements, oncology treatment and what is included in the package. These figures are intended for preliminary comparison only and are not final quotations. Figures other than India and the United States are modelled planning estimates. They are not GAF quotations and not competitor quotes reproduced as ours.
Why do international patients consider India for esophagectomy?
International patients consider India for esophagectomy when they are self-funding a high-acuity upper-GI resection, when they want a named surgical oncologist before they fly, and when they need ICU that already manages anastomotic leaks in the same city as staging and, if used, neoadjuvant treatment.
Cost is the most visible reason. The catalog range $12,000–$28,000 sits well below typical US cash-pay of $50,000–$120,000, because theatre, ICU, ward and consultant time are priced on a different cost base — not because the operation is a lesser product by definition. Several listed metros can hold an MDT conversation in one week. English is the working language of most international desks.
None of that means India is the right country for every patient, and none of it is a claim of 'best surgeons in the world', guaranteed leak-free recovery or 'cheapest in the world'. Someone whose insurance covers the pathway at home, who cannot stay for two to three weeks, or whose staging shows resection is not honest, may be better treated locally.
Hospitals to consider for Esophagectomy in Mumbai, India
Campuses on GAF Healthcare where this surgical-oncology pathway is listed, with accreditation as published by the hospital. Listing with the procedure family is not a claim of esophagectomy volume or a ranking. Choose on the surgeon you met on camera, whether ICU has managed anastomotic leaks, and whether staging and neoadjuvant treatment can stay in the same city — not on a brand slogan.
Campuses for this pathway are being confirmed. Ask the desk which houses currently quote it.
Doctors to consider for Esophagectomy in Mumbai, India
These are consultants listed on GAF Healthcare whose catalog procedures include esophagectomy or esophageal cancer surgery. Profiles show training, campus and procedures as held in the catalog. There are no rankings here, and no fee is paid for placement. Named listings currently sit in Delhi NCR, Chennai and Hyderabad; Mumbai and Bengaluru are matched after records review.
Named consultants for this pathway are being matched. Request a dossier and we will advise which campuses can quote it.
Esophagectomy cost by city in India
City names below are working filter URLs — the same destination, city, specialty and procedure keys the rest of the site already uses. Open Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad for the city overlay and the filtered doctor and hospital cards.
We do not invent a different surgical tariff for each metro. The approximate cost column uses the India planning band of $12,000–$28,000 unless a researched city figure exists. What does change is the named consultant list, ICU geography, airport access and how expensive a two-to-three-week companion stay actually feels.
Swipe to compare Indian cities →
Delhi NCR
$12,000–$28,000
India planning band — not a city quote
Typical stay 10–18 nights
Ask which NCR campus and which ICU the letter is written against, how many ICU nights are named, and whether MIE is actually offered that week. Campus tier inside NCR moves the letter more than the city label.
8 hospitals · 19 doctors
Mumbai
$12,000–$28,000
India planning band — not a city quote
Typical stay 10–18 nights
Surgical estimates sit on the national band once a surgeon is matched. The Mumbai-specific extra is usually the hotel for two to three weeks and the harbour commute — among the highest companion costs of the five cities.
0 hospitals · consultant match on request
Bengaluru
$12,000–$28,000
India planning band — not a city quote
Typical stay 10–18 nights
Serviced apartments near the southern campuses often undercut Mumbai or Gurugram hotel rates over a three-week recovery, which can change the total trip more than any small difference in surgical fee.
0 hospitals · consultant match on request
Chennai
$12,000–$28,000
India planning band — not a city quote
Typical stay 10–18 nights
Ask whether the international desk handles visa extensions in-house. Neoadjuvant chemoradiation plus resection plus a leak week often outlasts a short visa window.
2 hospitals · 3 doctors
Hyderabad
$12,000–$28,000
India planning band — not a city quote
Typical stay 10–18 nights
Extended-stay accommodation is generally more affordable than in Mumbai or NCR, which often changes the total trip more than any difference in surgical fee — especially across 10–18 nights plus hotel step-down.
3 hospitals · 5 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for esophagectomy
What should international patients budget beyond the surgery?
The surgical estimate is only one line in a medical-travel budget. Procedure cost is not total medical travel cost. Staging, neoadjuvant therapy, ICU extras, weeks of hotel after discharge, flights and a companion who can stay are the rest of the trip.
Ask the coordinator to quote each stage separately. Do not invent flight or hotel prices from this page. Add your own numbers: surgery + quoted stay including named ICU nights + staging tests + drugs/radiation if in India + flights + visa + hotel nights × rate + local transport + attendant costs + a contingency for extra ICU or leak days.
- Staging and cardiopulmonary work-up
- Endoscopy, CT, PET-CT where indicated, lung and heart tests, nutrition. Often extra if done in India.
- Neoadjuvant treatment, if used
- Chemotherapy or chemoradiation before surgery. Neighbouring cost sheets. Can add weeks in the city.
- The operation
- Resection, reconstruction, anaesthesia, ICU as quoted, 10–18 nights and pathology. This is the $12,000–$28,000 line when the letter matches that scope.
- Extra ICU, leak care, nutrition
- Beyond the quoted nights. Ask what happens if hospitalization is extended.
- Adjuvant oncology
- Further drugs or radiation if pathology and the MDT advise it.
- Flights and visa
- Patient and attendant. Medical visa duration should cover a possible leak week. Issuance is not guaranteed.
- Accommodation after discharge
- Hotel or apartment near the campus until the surgeon is content you can fly. Budget more nights than a lumpectomy trip.
- Local transport and attendant expenses
- Airport transfers, clinic runs, food, lost work. Pair the hotel to the hospital, not the airport.
- Treatment episode$12,000–$28,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay10–18 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for esophagectomy in India involve?
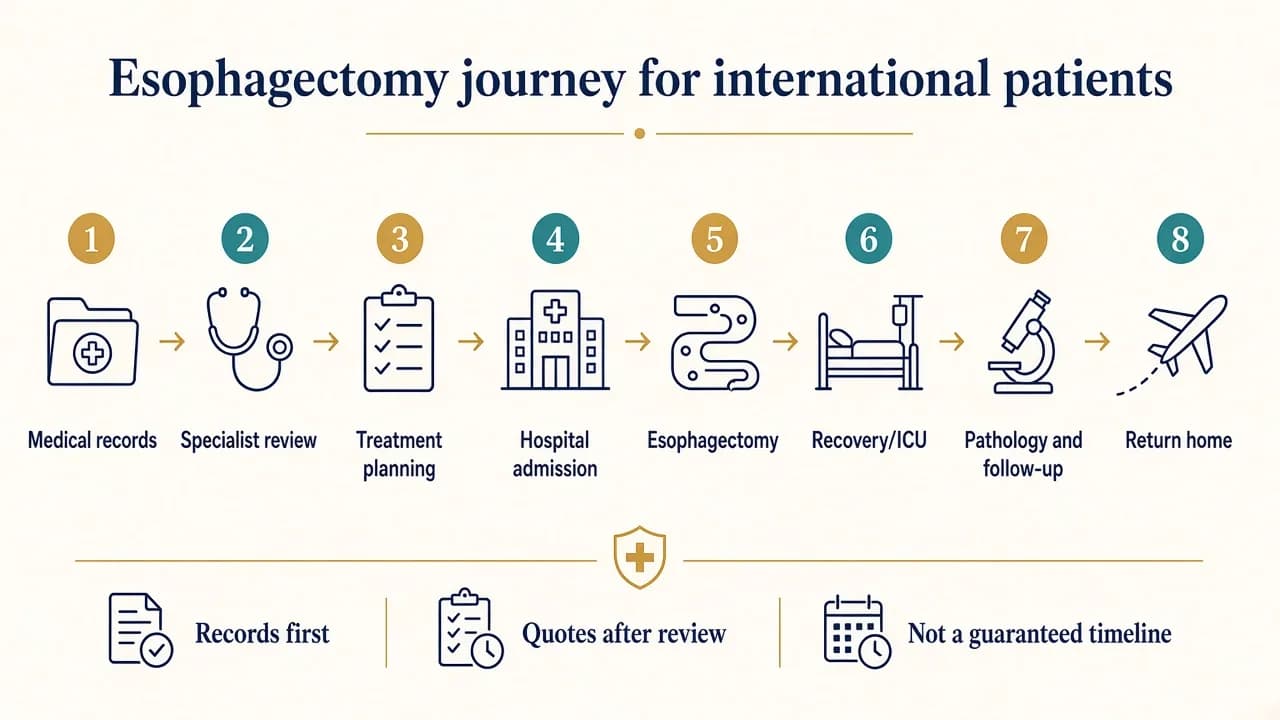
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Submit medical records
Endoscopy report, biopsy, CT/PET-CT, a note on swallowing and weight loss, and a medicine list.
Imaging and pathology review
A surgeon who resects oesophagus reads the actual films and histology, not a coordinator's paraphrase.
Specialist assessment
On camera: whether resection, neoadjuvant treatment first, or a non-operative path is the honest next step.
Multidisciplinary planning
Where appropriate, surgical, medical and radiation oncology agree sequence before a date is offered.
Preliminary treatment plan and cost estimate
An itemised surgical letter. ICU nights, approach, reconstruction, drugs and radiation quoted separately if in view.
Hospital selection
Compare the surgeon you met, whether ICU has managed leaks, and how long a companion can stay in that city.
Travel planning
A hospital invitation typically supports a medical visa. Write duration for 10–18 nights plus hotel recovery. Visa issuance is not guaranteed.
Hospital admission
Usually a day or two before theatre after in-person examination and any missing tests.
Surgery
Four to eight hours depending on approach. Combined gastric resection, if needed, lengthens the sitting.
Postoperative recovery
ICU then ward across 10–18 nights. Extra nights are a clinical decision, not a package failure.
Pathology and further treatment
Specimen results feed adjuvant planning. Do not fly before that conversation if further treatment in India is likely.
Follow-up and return-home planning
Operative note, pathology, feeding plan and a written handover. Fly when the named surgeon is content.
Documents to prepare
- Upper endoscopy report and images, plus the biopsy histopathology
- CT chest and abdomen, and PET-CT if already done
- Endoscopic ultrasound or staging laparoscopy notes if performed
- Neoadjuvant chemotherapy or radiation summary if treatment has started
- Weight trend, swallowing history, and current nutrition (including any feeding tube)
- Cardiac and pulmonary test results, if available
- Current medication list, allergies, and smoking/alcohol history
- Passport, and a hospital invitation letter for the medical visa application
Clinical detail
How the procedure is performed
Pre-operative assessment confirms staging, cardiopulmonary fitness, nutrition and the planned fields. Anaesthesia is general, often with one-lung ventilation if the chest is entered.
Surgical access follows the named approach: abdomen and right chest (Ivor Lewis), abdomen, chest and neck (McKeown), or abdomen and neck (transhiatal). The diseased oesophagus is removed. Lymph nodes are taken according to the protocol. A conduit is formed, usually from stomach, and joined to the remaining oesophagus.
You wake in ICU or high-dependency care. Drains, a feeding jejunostomy in many protocols, and swallow studies before oral intake are common. Pathology of the specimen arrives days later and feeds the next oncology conversation. Exact steps differ by approach; this page does not describe graphic operative detail.
Main variations
- Gastric conduit reconstruction
- The usual method when the stomach can be mobilised as a tube. Adds conduit ischaemia and leak risk to the conversation, which is why ICU monitoring is not optional branding.
- Colon or jejunal reconstruction
- Used in selected situations when stomach is not available. Longer theatre, additional anastomoses, different leak map. Should be named on the letter if planned.
- Chest versus neck anastomosis
- Ivor Lewis typically joins in the chest; McKeown and transhiatal typically join in the neck. Leak presentation and management differ. Neither is universally safer.
- Two-field versus three-field lymphadenectomy
- Extent of nodal surgery follows tumour location and protocol. Three-field work is a larger sitting, not a doubled brochure price.
- Minimally invasive or robotic access
- Ports instead of, or in addition to, open incisions when the team offers it. Oncological goals remain resection and reconstruction. Availability is not implied by a brand name.
Preparation
Expect endoscopy with biopsy, CT of chest and abdomen, and PET-CT when indicated. Cardiopulmonary tests, bloods and a nutrition review come next. Home investigations can often be reviewed rather than repeated.
If neoadjuvant chemotherapy or chemoradiation is already under way, bring the protocol, dates and the latest imaging. Smoking and alcohol history belong in the file — they change leak and pneumonia risk.
Arrive with enough days before theatre for anaesthetic review and, if needed, feeding optimisation. Do not book a same-week international flight after a long-haul landing into a four-to-eight-hour resection.
Hospital stay and recovery
Hospital stay is typically 10–18 nights. The first days are ICU or high-dependency: breathing, rhythm, drains and the anastomosis. Oral intake is delayed until the team is content; feeding often starts via jejunostomy. This page does not set a diet or a discharge date.
Respiratory physiotherapy starts early. Anastomotic leak, pneumonia, atrial fibrillation and swallowing difficulty are among the problems that extend stay. Complication risk varies with fitness, tumour, prior radiation and surgical complexity. Individual percentages are not published here.
Pathology review decides adjuvant treatment. International patients often need a further week in a nearby hotel after discharge before a long-haul flight. Ranges on this page are not promises of recovery time. Individual recovery varies.
How to compare Esophagectomy quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Is the surgeon's fee included, and is the person on this call the person in theatre?
- Which approach — Ivor Lewis, McKeown, transhiatal, MIE or robotic-assisted — and is that named on the letter?
- How is the conduit reconstructed, and is a colon or jejunal graft priced if stomach cannot be used?
- How many ICU nights are included, and what happens if I need more?
- Is lymph-node dissection included, and two-field or three-field?
- Are operating-room staplers and consumables included?
- Is anaesthesia included for a four-to-eight-hour case?
- Are staging PET-CT, endoscopy and cardiopulmonary tests included?
- Is pathology of the specimen included? Molecular tests?
- Are inpatient medicines and jejunostomy feeds included? What about discharge formula?
- How many hospital nights and which room category?
- What happens if an anastomotic leak or extra hospitalization occurs?
- Is neoadjuvant or adjuvant chemotherapy included? Radiation?
- Is follow-up before I fly included, including a swallow study?
Why your final Esophagectomy cost may be different
The figure on this page is a planning range. The figure on a hospital letter is an estimate written against a named approach, a named surgeon, a stated number of ICU and ward nights, and a reconstruction plan. Those two documents are not supposed to match to the dollar.
The procedure name alone does not define the surgical plan. Cost may change because of open versus minimally invasive or robotic access, tumour location, stage, reconstruction, lymph-node fields, neoadjuvant treatment, ICU, pathology, extra nights and complications.
If two hospitals quote different numbers, read the line items before you assume one is overcharging. One letter may include ten ICU-capable nights and a jejunostomy; the other may bill them later. One may be a flagship campus; the other a satellite. Higher cost is not a measure of better treatment.
Frequently asked questions
How much does esophagectomy cost in Mumbai?
Use $12,000–$28,000 as the planning range for resection, reconstruction and quoted stay. Mumbai does not have a separate verified tariff here. Hotel and transfer costs are usually the Mumbai-specific extra.
Are there named esophagectomy surgeons in Mumbai on this site?
Not currently as a procedure-tagged listing. Coordinators match a listed surgical oncologist after records review.
Should we stay in Mumbai or Navi Mumbai?
Stay on the same side of the harbour as the operating ICU. Treat Navi Mumbai as a separate commute for a 10-to-18-night admission.
Is monsoon a problem after esophagectomy?
The operation is performed year-round. The problem is getting a companion to ICU and managing a leak readmission in flooded traffic. Stay next to the hospital.
Can neoadjuvant treatment and surgery both happen in Mumbai?
Often discussed on comprehensive campuses. Quote each stage separately and write the visa for both.
Why would a family still choose Mumbai without a tagged esophagectomy surgeon?
Flight connections and existing private-oncology relationships. Matching still happens after endoscopy and staging are read. Do not treat a comprehensive campus as a named upper-GI resection consultant.
Is a Navi Mumbai quote comparable with an island-city quote?
Only after you add three weeks of attendant logistics. A cheaper harbour-side letter can cost more once every ICU visit crosses the water. The operating address belongs on the estimate.
What is the cost of esophagectomy in India?
Plan against $12,000–$28,000 for the resection, reconstruction, anaesthesia, quoted ICU/ward stay of 10–18 nights and specimen pathology. Typical US self-pay is $50,000–$120,000. The final figure is an itemised hospital estimate after a surgeon reviews endoscopy and staging. Neoadjuvant drugs and extra leak days are usually separate.
What is the cost of esophagectomy in Delhi NCR?
Delhi NCR inherits the India planning range of $12,000–$28,000. There is no separate verified NCR tariff on this site. Campus tier, approach and ICU course move the letter more than the city name.
Is esophagectomy covered in the cost of esophageal cancer treatment?
Usually not as a single all-in cancer price. Staging, neoadjuvant chemotherapy or chemoradiation, the resection, adjuvant treatment and surveillance are neighbouring quotes unless a letter explicitly combines them.
What affects the cost of esophagectomy?
Approach, open versus minimally invasive or robotic access, reconstruction, lymph-node fields, campus tier, the named surgeon, ICU nights, complications and whether oncology treatment shares the trip. Higher price is not a measure of better care.
What is included in an esophagectomy package?
A typical surgical estimate covers the named surgeon, anaesthesia, theatre, quoted ICU and ward nights, routine inpatient medicines and specimen pathology. Confirm staplers, jejunostomy feeds, extra ICU, PET-CT and drugs.
Is ICU included in the quoted cost?
Only the nights the letter names. Early ICU is usual after esophagectomy. Extra days after a leak or pneumonia are typically extra. Ask for the number in writing.
Does minimally invasive esophagectomy cost more?
It can, because of theatre time and consumables, but GAF Healthcare does not publish a separate MIE tariff. Ask whether MIE is actually offered for your tumour and how that changes the itemised letter.
Does robotic esophagectomy cost more?
Robotic assistance, where offered, is a different resource envelope. There is no separate GAF robotic-esophagectomy price. Do not treat a neighbouring thoracic-robotics sheet as this operation's quote.
What is an Ivor Lewis esophagectomy?
A two-phase resection through the abdomen and right chest, with the anastomosis typically in the chest. It is one established approach for selected mid and lower-third tumours. It is not universally better than McKeown or transhiatal.
What is a McKeown esophagectomy?
A three-phase resection through abdomen, chest and neck, with the anastomosis typically in the neck. Often discussed for more proximal tumours. It is a longer sitting, not a product upgrade.
How long is hospital stay after esophagectomy?
Typically 10–18 nights on this sheet, including early ICU. Leaks, pneumonia or feeding problems extend that. This page does not promise a discharge date.
How long should an international patient stay in India?
Plan the inpatient 10–18 nights plus further hotel days until the named surgeon is content you can fly — often around three weeks in country for an uncomplicated course, longer if neoadjuvant treatment or a leak occurs.
What tests are required before esophagectomy?
The actual work-up depends on the patient and plan. Commonly: endoscopy with biopsy, CT, PET-CT where indicated, bloods, and cardiopulmonary and nutrition assessment. Home tests can often be reviewed rather than repeated.
Does esophagectomy require chemotherapy or radiation?
Sometimes, before or after surgery, depending on type, stage and MDT assessment. Those treatments are separate estimates. This page does not prescribe a sequence.
How do I choose an esophagectomy surgeon?
Use listed consultants whose catalog procedures include esophageal cancer surgery or esophagectomy, compare training and campus on the profile, and insist on speaking to the person who would operate. Placement is not a league table.
How do I compare esophagectomy hospital quotations?
Line by line: surgeon, approach, reconstruction, ICU nights, staplers, pathology, feeds, extra-night and leak policy, PET-CT, chemotherapy and radiation. Same procedure name is not the same surgical plan.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Gastrectomy cost in India
$9,000–$22,000 · stay 7–14 nights
Whipple Procedure cost in India
$14,000–$32,000 · stay 10–18 nights
Chemotherapy cost in India
$1,500–$8,000+ · stay Outpatient cycles · 3–6 months typical
Neoadjuvant Chemotherapy cost in India
$2,500–$10,000 · stay Cycles before surgery · 2–4 months
Intensity-Modulated Radiotherapy (IMRT) cost in India
$6,500–$14,500 · stay 4–7 weeks of fractions
Further reading: surgical oncology costs in India · medical oncology costs in India · radiation oncology costs in India · gastroenterology costs in India · surgical gastroenterology costs in India · esophagectomy surgeons in India · esophagectomy hospitals in India
Planning your esophagectomy treatment in India
Esophagectomy in India is typically planned in the $12,000–$28,000 band for the resection, reconstruction and quoted inpatient stay, against $50,000–$120,000 self-pay in the United States. The variables that actually move that band are approach, reconstruction, ICU course, campus tier, the named surgeon and whether chemotherapy or radiation is completed in the same trip.
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad each have listed campuses for this surgical-oncology pathway. Named catalog consultants for esophageal cancer surgery currently sit in Delhi NCR, Chennai and Hyderabad; Mumbai and Bengaluru are matched after records review. Doctor and hospital cards on this page link only to profiles that already exist in the catalog.
A personalized quotation, written after records review, is the document you should travel on. Cost ranges on this page are intended for preliminary planning and comparison only. Final treatment costs vary according to the patient's clinical condition, treatment plan, hospital, surgeon, surgical approach, length of stay and other factors. A personalized quotation should be obtained before making treatment or travel decisions.
Get a Personalized Cost EstimateTalk to a Treatment Coordinator
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 10 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Esophagectomy cost sheet · All treatment costs in India · Surgical Gastroenterology costs



